
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
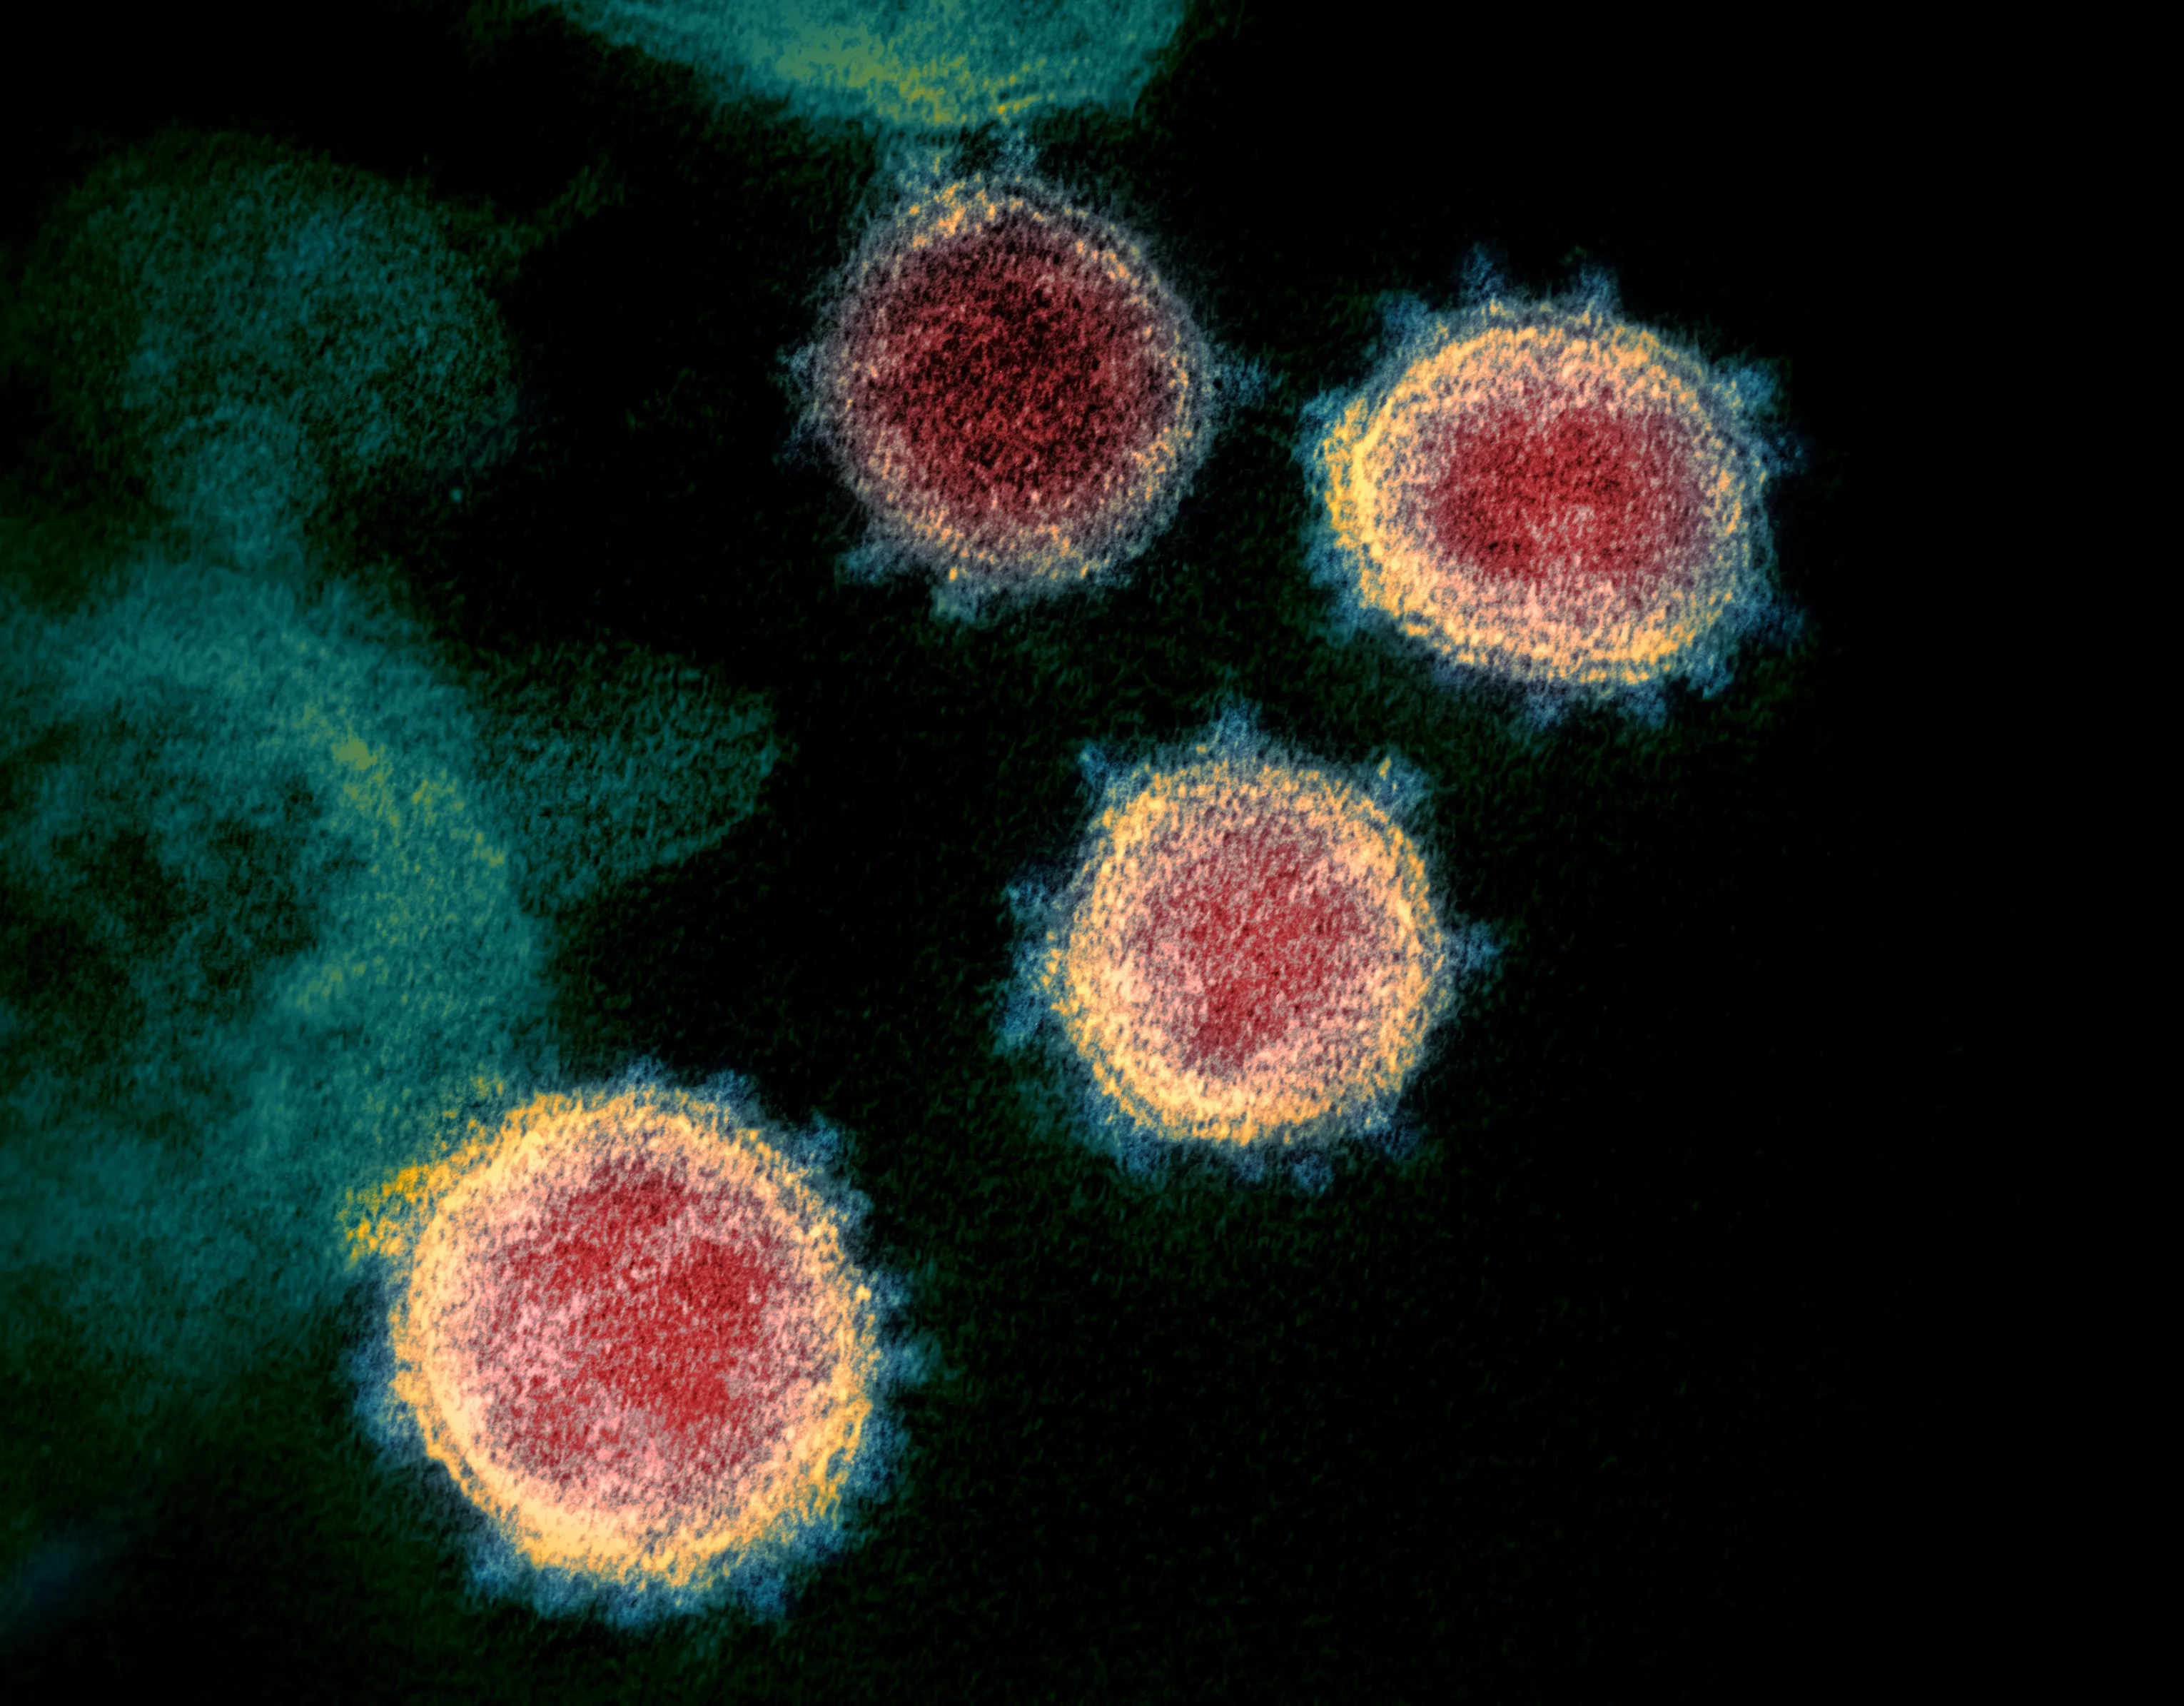

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreEuropean health authorities are reporting a sharp summer increase in COVID-19 hospital admissions, with a newly identified BA.5 lineage of Omicron emerging as a leading concern. Sequencing and hospital data point to widening transmission, although the pressure is also being amplified by seasonal viruses, delayed treatment and gaps in population immunity.
A rise in cases does not automatically produce an immediate rise in severe illness. Hospital admissions usually follow infections by one or several weeks, while pressure on beds depends on discharge rates, staff availability and the number of patients requiring oxygen or intensive care. Reports from several parts of Europe nevertheless show that infections among older people, unvaccinated adults and those with chronic conditions are translating into greater demand for acute care.
Australia cannot treat the European pattern as a precise forecast, but it offers an important warning during the southern winter. As colder weather keeps people indoors and respiratory illnesses circulate, a highly transmissible variant could place additional pressure on hospitals, pharmacies and aged-care services in cities including Sydney, Melbourne and Brisbane. Early surveillance and targeted protection would be more useful than broad panic.
Health systems across western, northern and southern Europe have recorded increases in respiratory admissions linked to the BA.5 descendant. The pattern is not uniform: some countries are seeing more emergency department visits without a proportional rise in ward admissions, while others report growing numbers of patients needing longer hospital stays. This variation reflects differences in prior immunity, vaccination uptake and the timing of the wave.
Understanding the lineage requires more than examining daily case counts. Technical background on sequencing, severity and the limits of forecasting is available through the clinical evidence review at the Apollo Medical Journal. Such material also shows why a label such as BA.5 cannot, by itself, indicate how many hospital beds a population will require.
Hospitals can experience a surge even when case growth appears stable. Admissions lag behind diagnoses, and some people who test positive at home eventually deteriorate. Co-infections, postponed medical care and reduced bed availability may add pressure at the same time. Consequently, authorities are monitoring emergency referrals, oxygen use, intensive-care demand and the age profile of admitted patients rather than relying on case notifications alone.
BA.5 first became widely recognised in 2022, so the “new” BA.5 subvariant now circulating refers to a more recent descendant or closely related lineage rather than an unchanged 2022 virus. Changes in its spike protein may help it evade antibodies produced by vaccination or earlier infection, allowing it to spread through populations where substantial immunity already exists.
Immune escape does not necessarily mean each infection is more severe. The main danger is that a virus which avoids existing protection can reach more people, including vulnerable groups, at a faster rate. If a large share of those infections occurs among older adults or people with heart, lung, kidney or immune-system conditions, hospital admissions can rise sharply.
Seasonal behaviour also matters. European travel, crowded hospitality venues and time spent in air-conditioned indoor spaces support transmission during warm months. A lineage that can evade immunity and spread efficiently may become dominant without possessing dramatically different symptoms. People who feel well enough to travel, socialise or work can still transmit it, delaying the point at which the effect becomes visible in hospitals.
Australia’s first concern would be timing. European summer transmission overlaps with the Australian winter, when schools resume, workplaces remain active and people gather indoors more often. Sydney residents regularly move between air-conditioned offices, trains and crowded venues, while Melbourne’s cooler and damp conditions encourage close indoor mixing. In Brisbane, warm humid weather can also drive activity into enclosed shopping centres, restaurants and entertainment venues.
International travellers pass through Sydney and Melbourne, making genomic surveillance and clear advice for symptomatic arrivals important. The risk is greatest in aged-care facilities, where a small number of infections can lead to hospital transfers among medically frail residents. Local outbreaks would therefore need rapid clinical assessment, not merely a general increase in community testing.
Reporting in a recent WHO pandemic update highlights how declining case totals can coexist with continuing pandemic risk. That matters in Australia because the population includes groups that can become seriously ill after infection, while routine surveillance may not capture mild or unreported cases.
Preparedness is divided across Australia’s federal and state systems. State and territory public-health legislation provides authorities with powers to respond to outbreaks, while Commonwealth responsibilities include national vaccination programs, aged-care regulation and medicine assessment through the Therapeutic Goods Administration. Exact rules vary across jurisdictions, so travellers should check current advice rather than assume one national standard applies everywhere.
Australia’s consumer market also shapes practical access. Chemists, independent pharmacies, supermarkets such as Woolworths and Coles, pathology providers and online sellers affect the availability of home tests, protective products and eligible antiviral treatments. Maintaining diverse supply routes would reduce the risk that a sudden increase in demand creates shortages, particularly in regional and rural communities.
Australian households and health services can reduce the impact of another wave without disrupting everyday life. The focus should be on early detection, protection of high-risk people and rapid treatment for eligible patients.
For households:
For pharmacies and clinics:
These measures fit established Australian routines rather than requiring a return to the strict restrictions seen in earlier phases of the pandemic. Commuters can adjust their behaviour when they are infectious, families can test before visiting vulnerable relatives, and pharmacists can identify patients who may benefit from early treatment. If cases remain low, the additional burden should be small and proportionate.
COVID-19 continues to affect more than acute respiratory illness. A tuberculosis resurgence warning describes how disrupted routine diagnosis, reduced access to preventive treatment and pressure on health services can allow tuberculosis to spread unnoticed. Similar disruptions occurred during earlier waves and could recur if respiratory infections again divert staff and resources.
Long COVID, delayed cancer diagnosis and postponed routine care remain important social and economic effects. Governments therefore have an interest in avoiding the opposite extreme: withdrawing surveillance and prevention support as soon as hospital numbers improve. Maintaining testing, genomic sequencing and vaccine access for high-risk groups can protect the wider health system without imposing broad restrictions on the public.
The most defensible interpretation is that a BA.5 descendant is adding to Europe’s summer hospital burden, while seasonal illness and depleted healthcare capacity amplify the effect. Australia has time to use that evidence, but the response should be regional and targeted. The clearest planning assumption is that a variant capable of widespread infection can still create severe outcomes when it reaches older and medically vulnerable populations.
| Planning factor | Europe’s summer experience | Australia’s winter response |
|---|---|---|
| Transmission | BA.5 descendants spread during travel, hospitality and crowded indoor venues | Monitor growth as colder weather increases indoor activity |
| Hospital pressure | Admissions lag infections and can strain emergency, oxygen and intensive-care capacity | Protect hospital reserves and maintain rapid referral pathways |
| Higher-risk groups | Older adults, unvaccinated people and those with chronic illness account for much of the severe burden | Prioritise aged care, remote communities and people with significant medical conditions |
| Prevention | Uneven immunity allows new lineages to replace earlier variants | Maintain surveillance, vaccination access and antiviral assessment |
| Overall judgement | One lineage contributes to the surge but is not its sole cause | Treat the European pattern as a warning signal rather than a precise prediction |