
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
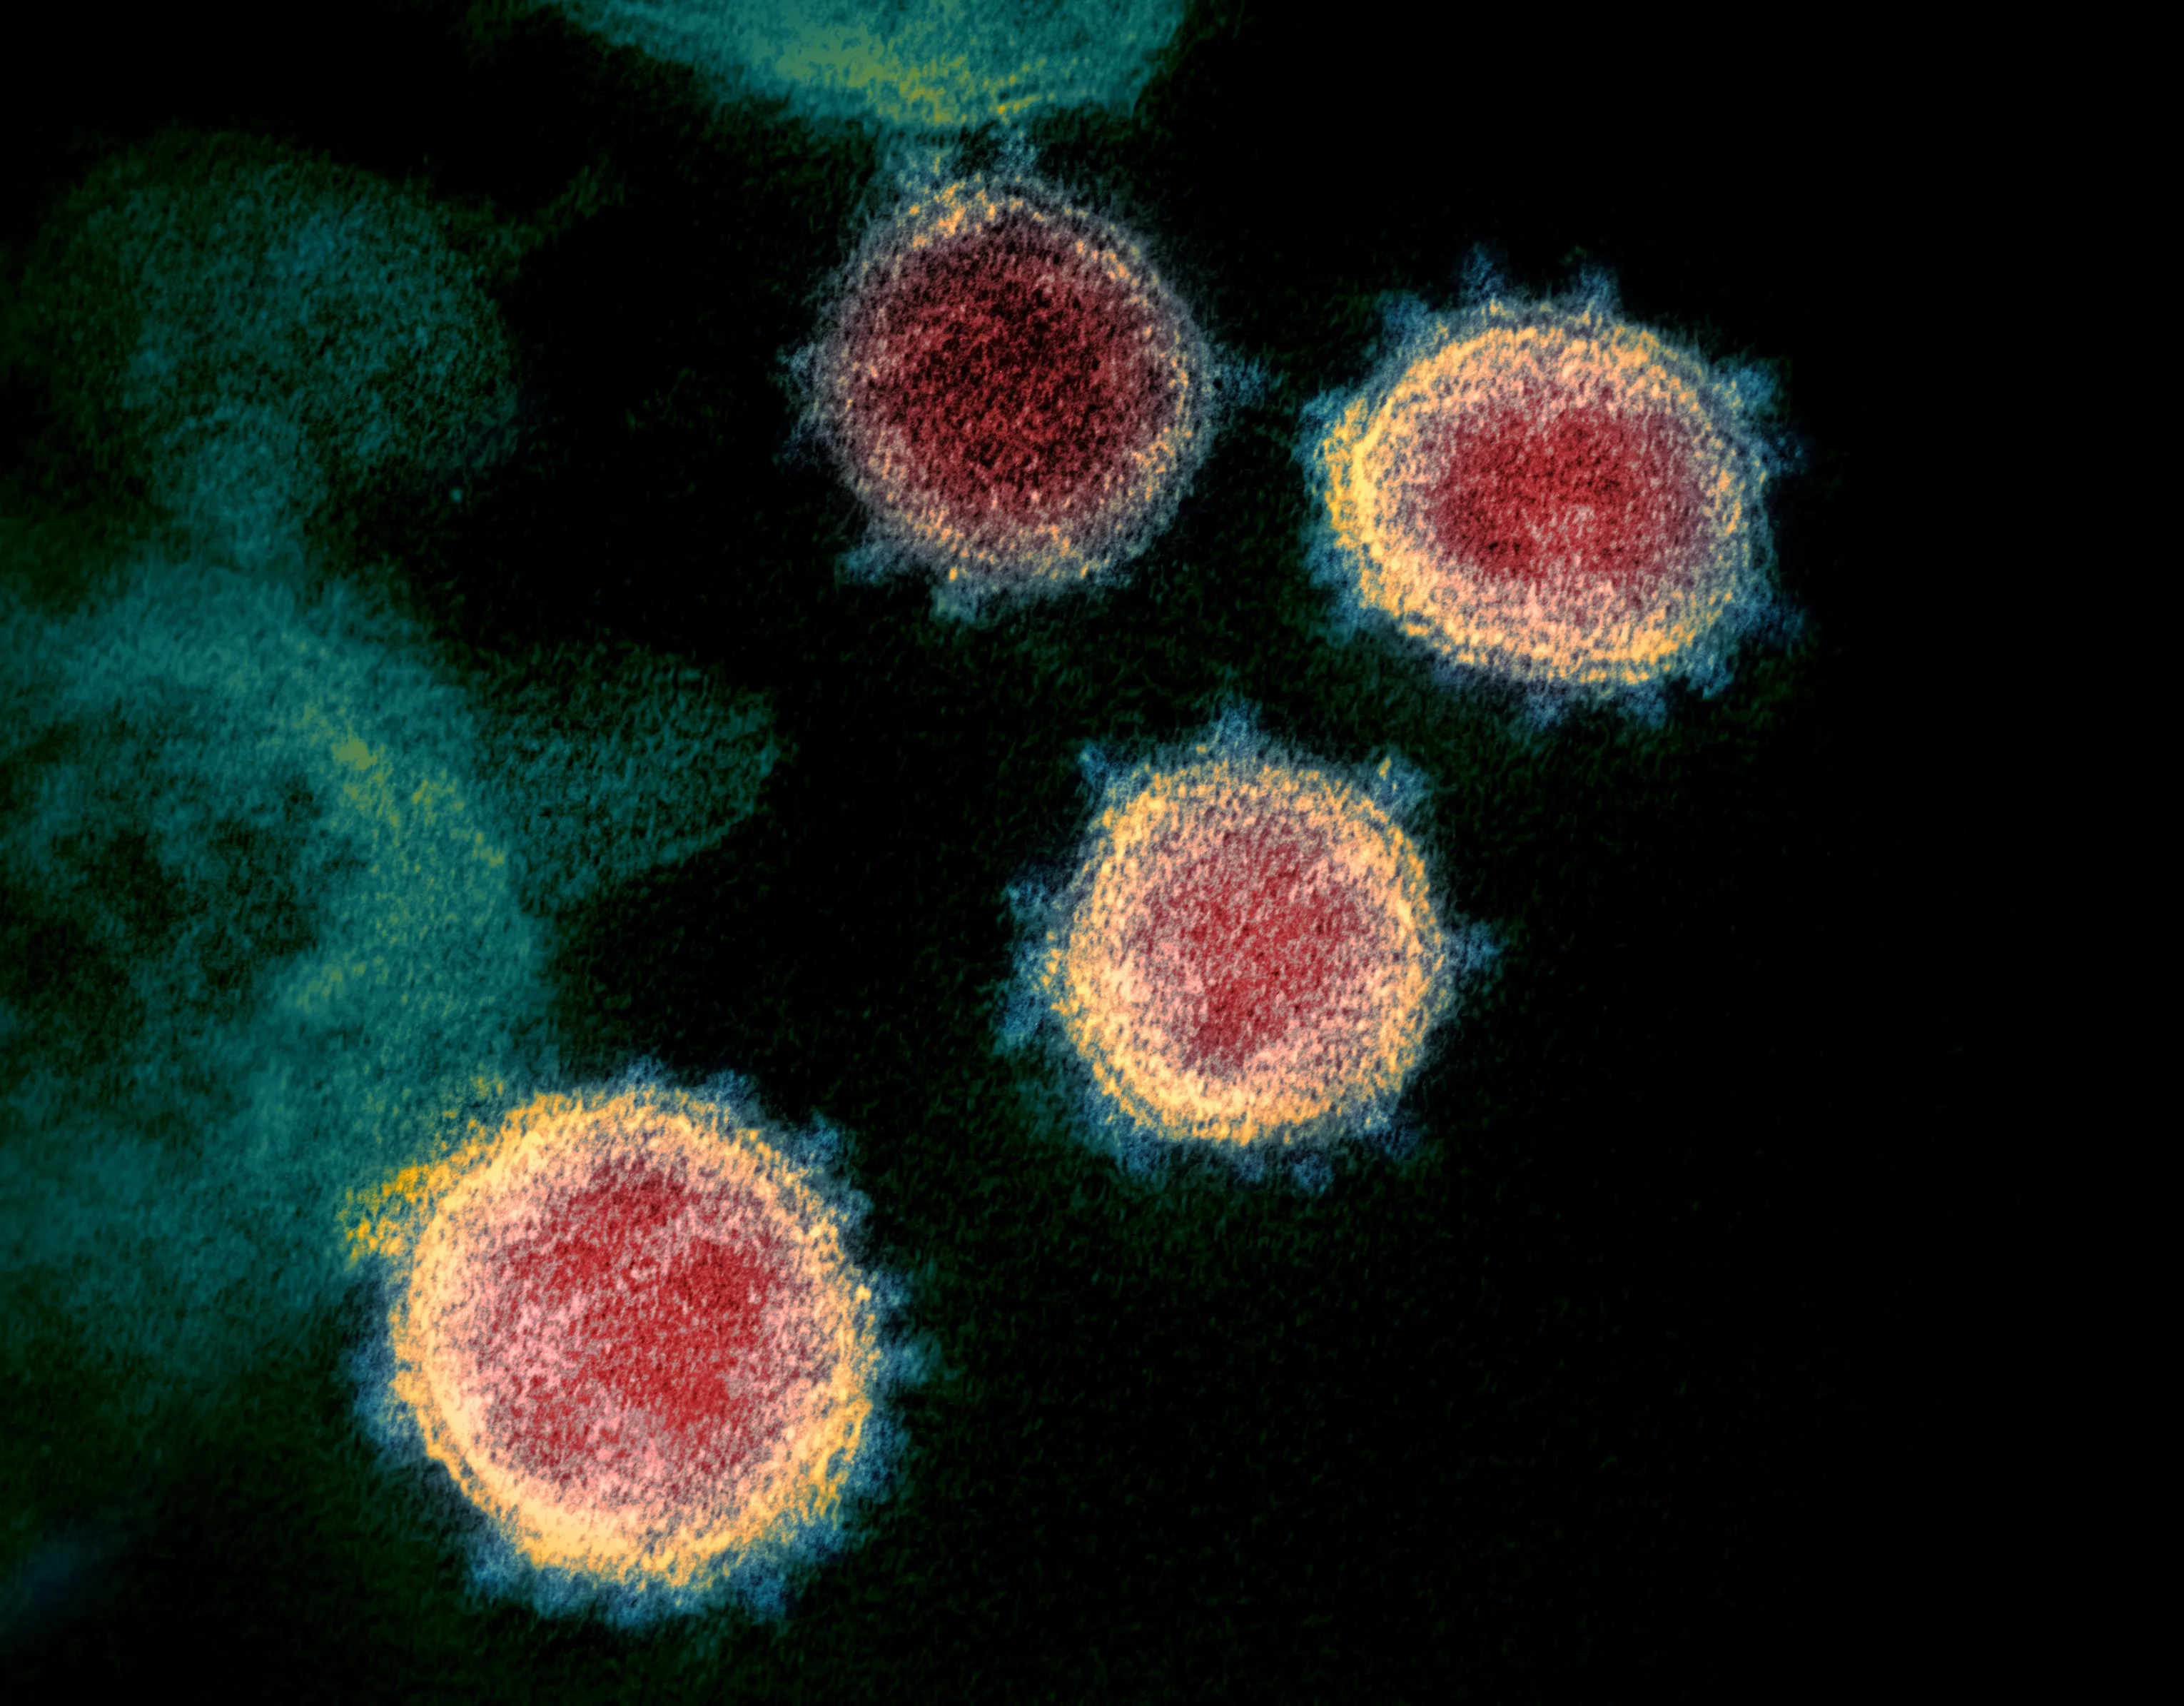

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreThe World Health Organization says the COVID-19 pandemic is far from over despite declining case counts in several countries. Its assessment is not a claim that every outbreak is escalating. It is a warning against treating a short-term reduction in infections as the end of the virus’s impact. Hospitals remain exposed to sudden rises in severe illness, while the pathogen continues to circulate widely and change. WHO officials argue that preparedness must therefore survive periods when headlines appear calmer.
For Australians, the meaning is practical rather than dramatic. A decline in national infections can hide local differences between Sydney, Melbourne, Brisbane and regional areas. It can also reflect fewer tests, a temporary variant shift or changes in how people seek care. The sensible response is to keep testing, vaccination and ventilation habits available without assuming every state follows the same schedule. Local health guidance and current case data remain more useful than a single global label.
Reported case totals are an imperfect measure of infection. Rapid antigen testing can reduce the number of positive results sent to laboratories, and many countries now publish testing less often than during the emergency phase. A falling curve may therefore describe testing behaviour as much as changing transmission. The WHO places case reports beside hospital admissions, deaths, excess mortality and signals from wastewater surveillance. Each measure captures a different part of the outbreak and can move in a different direction.
Seasonality adds another layer of uncertainty. Behaviour changes with weather, school calendars, travel and holidays, making it difficult to separate a lasting reduction from a temporary lull. A new variant that spreads easily may lift infections even when the rate of severe disease initially remains low. That gap matters because a high number of mild infections can still fill emergency departments, interrupt work and place pressure on aged care when staff are absent.
The warning also concerns the uneven geography of risk. Countries with limited access to vaccines, oxygen, medicines or intensive care can face much greater harm from the same infection level. Even well-resourced systems can experience rapid pressure if an outbreak reaches older residents or medically vulnerable groups. WHO therefore frames the task as sustained pandemic control, with surveillance and rapid response, rather than a switch between total neglect and emergency restrictions.
The organisation relies on data supplied by countries as well as modelling, genomic surveillance and reports from health workers. Coverage is not equal everywhere, so an apparent global improvement can conceal serious pockets of transmission. Reviewers at CoronavirusNewsLive track those shifts through live case statistics, while WHO updates remain the benchmark for assessing worldwide transmission, severe disease and programme performance.
Variant monitoring is a crucial part of that work. Researchers compare the genetic changes in samples with indicators of hospitalisation and death, looking for changes in immune escape, diagnostic accuracy or treatment effectiveness. This does not predict the next variant with certainty, but it can reveal when a lineage is gaining ground. The practical question is whether a change produces more infections, more severe outcomes, or both.
Wastewater measurements offer another view because they can detect community transmission without relying on individual tests. Their usefulness depends on population coverage, sampling methods and how quickly results are reported. WHO also pays attention to vaccination coverage, outbreaks in hospitals and care homes, and disruptions caused by illness among health workers. Taken together, these signals give a more reliable picture than a headline case count alone.
Australia’s response has become less uniform as emergency-era rules have been wound back. In Sydney and Melbourne, crowded train platforms, shared offices and busy hospitality districts make ventilation and flexible working arrangements relevant to daily risk. In Brisbane, summer heat can push social gatherings indoors and encourage longer periods of air-conditioned ventilation with closed windows. Residents who notice symptoms are now more likely to rely on a rapid test available through a pharmacy or supermarket than on a routine clinical appointment.
Everyday prevention is consequently becoming a matter of judgement. Keeping a mask for crowded indoor travel, improving airflow at home and avoiding work or school when acutely unwell can reduce exposure without shutting down normal life. The Australian market for rapid antigen tests has made home screening routine, although availability and price can vary. Pharmacies and general practitioners also remain important access points for advice, particularly for older people, pregnant patients, people with disability and those whose immune systems are weakened.
The same habit of checking conditions before acting applies to travel. For example, route and season advice for climbing Hoverla in Ukraine illustrates how a destination’s profile can change with weather and access. Australians weighing overseas travel should combine entry requirements with current health advice, including whether a destination is experiencing a rising outbreak. That approach is less about fear than about using the best available evidence before sharing plans with family or arranging a group trip.
Vaccination remains the main protection against severe illness, hospital admission and death, although protection against infection is less durable and can be affected by circulating variants. The Therapeutic Goods Administration assesses vaccines for Australian use, while federal purchasing, state programmes and private pharmacy sales shape availability. Current Australian COVID-19 vaccine advice is increasingly focused on people at higher risk, including older adults, immunocompromised residents, Aboriginal and Torres Strait Islander communities, people with chronic conditions and workers with high exposure.
Product decisions matter because a vaccine authorised in one country may not be authorised, supplied or recommended in another. A report on AstraZeneca variant concerns describes South Africa pausing use of a specific vaccine over issues linked to a variant, illustrating how product-specific evidence can change quickly. Australians should therefore rely on Australian clinical guidance and regulator updates, not assume every vaccine listed overseas is interchangeable or available locally. Pharmacists can confirm which products are currently approved and suitable for a particular risk group.
Antiviral medicines can also reduce the chance that a vulnerable person becomes seriously ill, but they work best when started early and after a positive test or clinical assessment. This makes rapid testing and access to medical advice closely connected. A positive result should not trigger panic, yet it should prompt eligible patients to contact a clinician or pharmacist promptly. Regular reviews of eligibility, interactions and local prescribing pathways are essential as medicines, variants and clinical evidence change.
Australia’s legal framework still provides a way to act if transmission causes serious harm. Legislation such as Victoria’s Public Health and Wellbeing Act 2008 and the NSW Public Health Act 2010 allows relevant public-health officials to manage notifiable diseases under state powers. Most broad COVID-era restrictions have been removed, so new measures would normally depend on local evidence rather than a single national trigger. That arrangement requires coordination between Commonwealth, state and territory authorities, hospitals, aged-care providers and the community.
Residents can prepare by checking their state health department’s advice, keeping a few rapid tests at home and knowing when medical help should be sought. Households can improve airflow in shared rooms, workplaces can avoid crowding during respiratory illness peaks, and aged-care managers can maintain outbreak plans that work even when agency staffing is limited. People at higher risk can ask their doctor or pharmacist about vaccination and antiviral treatment before a period of travel or community activity.
Good communication is itself a protective measure. Announcements should distinguish a rise in infections from a rise in hospital pressure, identify the area and age group affected, and explain what action is proportionate. Alarm can reduce public cooperation, while excessive certainty can discourage preparation. WHO’s central point is that uncertainty calls for monitoring and adaptable plans, not a return to the restrictions of 2020. Australia’s experience shows that readiness can coexist with ordinary daily life when the public, health services and governments know which signals to watch.
| Measure | A reassuring signal | Why caution remains | Practical response |
|---|---|---|---|
| Reported cases | A sustained fall in positive tests | Testing and reporting behaviour may also have changed | Compare cases with hospital data and local alerts |
| Hospital admissions | Fewer severe cases and lower bed use | Admissions lag infections and can rise suddenly | Watch occupancy alongside new outbreaks |
| Wastewater | Lower viral levels in tested catchments | Coverage and reporting vary between areas | Treat it as one indicator, not a verdict |
| Variant surveillance | No clear rise in a highly severe strain | Sampling is uneven and new lineages emerge | Monitor WHO and Australian genomic updates |
| Outbreak reports | Few active clusters in care settings | Small outbreaks can be missed or appear late | Maintain testing and infection-control plans |
| Vaccine uptake | More high-risk residents protected | Access, fatigue and misinformation can limit uptake | Target outreach and support informed choices |