
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
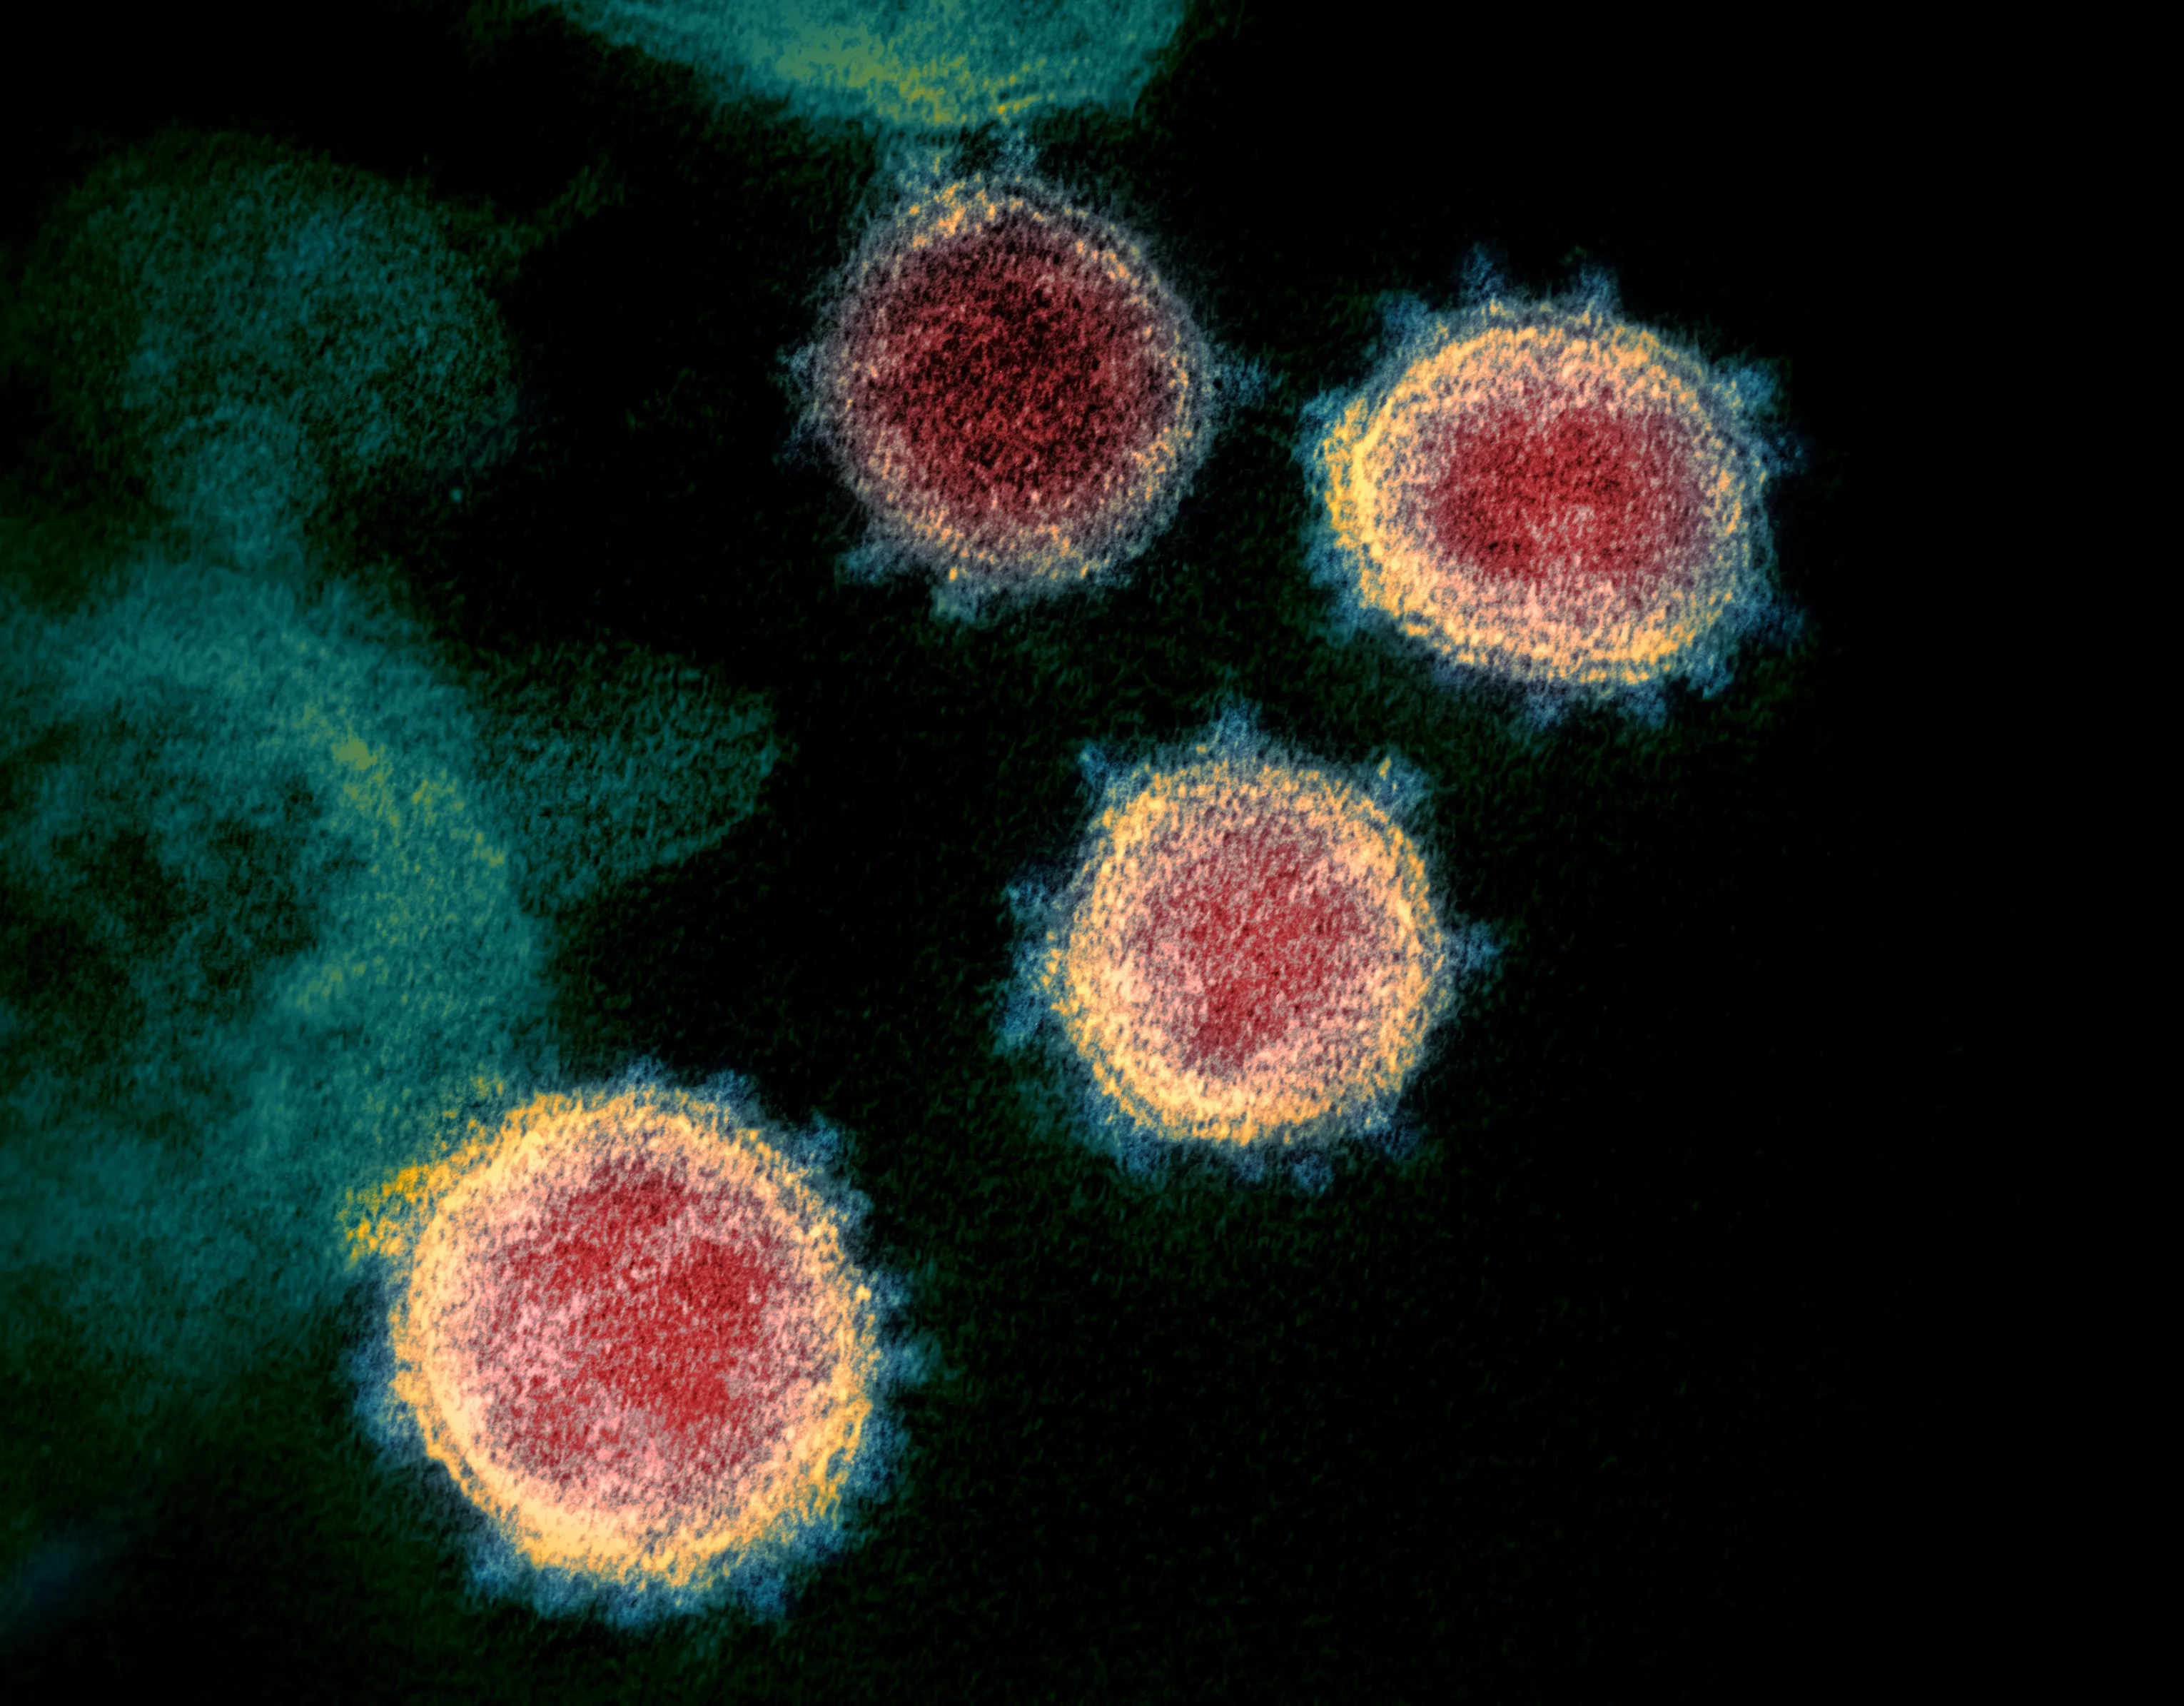

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreThe COVID-19 pandemic has increased the risk of tuberculosis returning with greater force, the World Health Organization has warned, after years of interrupted diagnosis, treatment and prevention. TB remains one of the world’s deadliest infectious diseases, and the strain placed on hospitals, laboratories and community health services allowed undetected infections to accumulate in many countries.
For Australia, the warning is a reminder that infectious disease threats do not stop at national borders. Local transmission is relatively low, but people travel frequently between Australia and high-burden countries, while remote communities can face long distances to specialist care. The effects of delayed testing overseas can therefore appear in Australian clinics months or years later.
Tuberculosis is caused by bacteria that most often affect the lungs and spread through the air when a person with active pulmonary TB coughs, speaks or sings. Some people carry latent TB infection without symptoms. They can remain well for years, although the infection may become active if their immune system is weakened.
COVID-19 created conditions that favoured a resurgence. Lockdowns and fear of infection reduced visits to doctors, while hospitals redirected staff, beds and laboratory capacity towards coronavirus testing and treatment. Contact tracing teams that might normally investigate TB cases were reassigned, and public health budgets were placed under extraordinary pressure.
The result was a fall in the number of people diagnosed in many settings, but that did not necessarily mean fewer infections. In some countries, people with persistent coughs stayed home, missed appointments or could not access transport. Untreated cases continued to transmit bacteria within households and communities, creating a hidden backlog.
WHO has also highlighted interruptions to preventive treatment, drug-resistant TB programmes and childhood vaccination. When routine services are disrupted, the damage can take years to appear in official statistics because tuberculosis develops slowly and diagnosis often follows a long period of symptoms.
A central concern is the gap between reported cases and actual cases. If fewer people are screened, a country may record a temporary decline while infectious disease spreads quietly. Once clinics reopen and testing resumes, notifications can rise sharply, giving the impression of a sudden outbreak even though transmission occurred earlier.
Treatment interruptions carry serious consequences. Standard TB therapy requires several medicines taken over months. Stopping early can leave bacteria alive and encourage drug resistance, making future treatment longer, more expensive and more difficult. Multidrug-resistant tuberculosis is especially concerning because it limits the medicines clinicians can rely on.
The same public health infrastructure used for coronavirus control can help repair this damage. Community nurses, laboratories, contact investigators and data systems already developed during COVID-19 can be directed towards finding people with symptoms and supporting them through treatment. The challenge is maintaining those services after public attention shifts away from pandemic news.
Digital tools can assist, but they cannot replace clinical care. Telehealth may help with follow-up appointments for people in rural areas, while electronic reminders can support medication adherence. A patient still needs access to diagnostic testing, a reliable medicine supply and a trained health worker who can respond when side effects occur.
Australia has one of the lowest TB notification rates in the world, yet the national picture is uneven. New South Wales and Victoria report many cases linked to overseas birth or travel, while the Northern Territory continues to manage a higher rate among Aboriginal and Torres Strait Islander people, particularly in remote communities.
In practical terms, Australians are more likely to encounter TB through international travel, migration or close household contact than through widespread community transmission. Sydney and Melbourne have large, diverse populations with strong connections to Southeast Asia, South Asia, the Pacific and Africa, regions where TB rates are generally higher. That makes accessible screening and culturally safe primary care important parts of prevention.
Remote Australia faces different barriers. A patient in the Top End or a distant Western Australian community may need transport, outreach services or an appointment with a visiting specialist. Seasonal work, overcrowded housing, limited internet access and the cost of taking time away from employment can make a long treatment course harder to complete.
The Australian way of discussing illness also matters. People may describe a lingering cough as “just a chest infection” or wait until they are “really crook” before seeking help. A cough lasting three weeks, unexplained weight loss, night sweats, fever or coughing blood should prompt medical attention, especially after close contact with a confirmed case or travel to a high-incidence country.
TB risk is shaped by living conditions, immune status, access to healthcare and exposure history. It is not a judgement about nationality or personal behaviour. A fair response focuses on practical barriers, avoids stigma and ensures that testing is confidential and linked to treatment.
| Risk area | Why it matters | Useful public health response |
|---|---|---|
| Interrupted diagnosis | Infectious cases can remain untreated and spread bacteria | Restore screening, contact tracing and laboratory capacity |
| Treatment disruption | Missed doses can lead to relapse or drug resistance | Provide follow-up, transport support and medication monitoring |
| Remote communities | Distance and workforce shortages delay specialist care | Fund outreach teams, local testing and culturally safe services |
| Overseas travel and migration | Infection may be acquired in higher-burden settings | Offer risk-based assessment and timely clinical review |
| Vulnerable health | HIV, diabetes, malnutrition and some medicines raise the risk of active TB | Integrate TB screening with broader primary care |
Australia’s public health system has strong foundations, including state and territory TB services, laboratory networks and contact investigation. The pressure lies in ensuring that these services reach people early rather than waiting for severe disease or a cluster to attract attention.
The economic calculation is straightforward. Detecting and treating one infectious case costs less than managing a chain of household infections, hospital admissions and drug-resistant disease. Prevention also protects health workers and reduces disruption in schools, workplaces and aged-care settings.
A chest X-ray, sputum testing and molecular diagnostic tools help clinicians distinguish active TB from other causes of respiratory symptoms. Tests for latent infection, including tuberculin skin testing and interferon-gamma release assays, can identify people who may benefit from preventive treatment.
These tools are most effective when people can reach a doctor without fear of cost, immigration consequences or embarrassment. Australia’s Medicare system provides broad access, but eligibility, language barriers and uncertainty about where to go can still delay care for some communities. Aboriginal Community Controlled Health Services are particularly important because they combine clinical care with local knowledge and trust.
Public messaging should be precise. TB is preventable and treatable, and it is not spread by sharing a cup, shaking hands or sitting briefly beside someone. Infection usually requires prolonged or repeated exposure to airborne bacteria, generally indoors and in poorly ventilated spaces. Accurate information reduces panic while encouraging people with genuine symptoms to seek assessment.
Respiratory precautions remain relevant in clinics and hospitals. Ventilation, masks during assessment, rapid isolation when appropriate and protection for healthcare workers can reduce exposure. These measures should be applied according to clinical guidance rather than used to create alarm or blame.
COVID-19 demonstrated the value of rapid data, but it also showed why people need confidence about how information is collected and used. Health departments need timely reporting on testing, treatment completion, drug resistance and geographic patterns. Communities need assurance that data will support care rather than expose individuals to discrimination.
Earlier pandemic debates about technology illustrated this tension. Proposals for companies to share location or mobility information with health authorities, such as those discussed in smartphone data sharing, raised questions about consent, anonymity and the limits of emergency surveillance. Similar principles apply to TB: data should be necessary, protected and governed transparently.
Online communication can help people find reliable symptoms information and local services, though health agencies must compete with rumours and sensational claims. The public may move from pandemic updates to entertainment and financial content in the same browsing session; a reel slots leaderboard challenge belongs to a different category from verified medical reporting, and readers need clear signals about that difference.
News outlets can support public health by explaining trends without presenting every increase as an emergency. Reporting should distinguish latent infection from active disease, imported cases from local transmission, and a rise in notifications from a rise in underlying incidence. Those distinctions help Australians understand risk without dismissing the problem.
The recovery requires sustained funding rather than a short campaign. TB programmes need laboratories, nurses, respiratory physicians, pharmacists, interpreters, social workers and community outreach staff. They also need stable supplies of first-line medicines and access to specialist drugs when resistance is detected.
Treatment support can be practical and respectful. Flexible appointments, transport vouchers, translated instructions, directly observed therapy when clinically appropriate and help with housing or nutrition can all improve completion rates. A patient who misses a dose may need assistance, not punishment, particularly when work, family responsibilities or distance are involved.
Australia also has a role beyond its borders. Regional partnerships with Pacific neighbours and Southeast Asian countries can strengthen laboratory capacity, infection control and access to effective medicines. Supporting TB control in nearby countries protects local populations and reduces the chance that untreated disease will travel through regular movement of people.
The pandemic showed that emergency response and routine healthcare are connected. When vaccination, antenatal care, diabetes management and infectious disease clinics are disrupted, several health problems worsen together. Restoring those services is part of preparing for future outbreaks, whether caused by coronavirus, influenza, TB or another pathogen.
The warning from WHO is less about a single dramatic outbreak than about accumulated neglect. Every missed diagnosis allows more time for transmission; every incomplete course of treatment increases the possibility of relapse or resistance. The figures may change gradually, but the public health consequences can become difficult to reverse.
Australians can expect most TB care to remain targeted through state and territory programmes, hospitals, general practices and Aboriginal Community Controlled Health Services. People with relevant symptoms or exposure should receive prompt medical assessment rather than relying on online self-diagnosis. Clinicians, in turn, need to keep TB in mind when symptoms persist, especially for patients with travel, migration or close-contact risk.
Reliable information is part of that response. Coronavirus coverage, public health updates and international statistics can help show how outbreaks develop across borders, while specialist financial content has its own place, including the site’s Buy Crypto section. Keeping these subjects clearly separated allows readers to assess health warnings on evidence rather than noise.
Tuberculosis is treatable, but control depends on early detection, uninterrupted therapy and public systems that remain accessible when attention moves elsewhere. The COVID-19 era exposed weaknesses in those systems; repairing them will determine whether the pandemic’s hidden TB burden fades or becomes a lasting resurgence.