
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
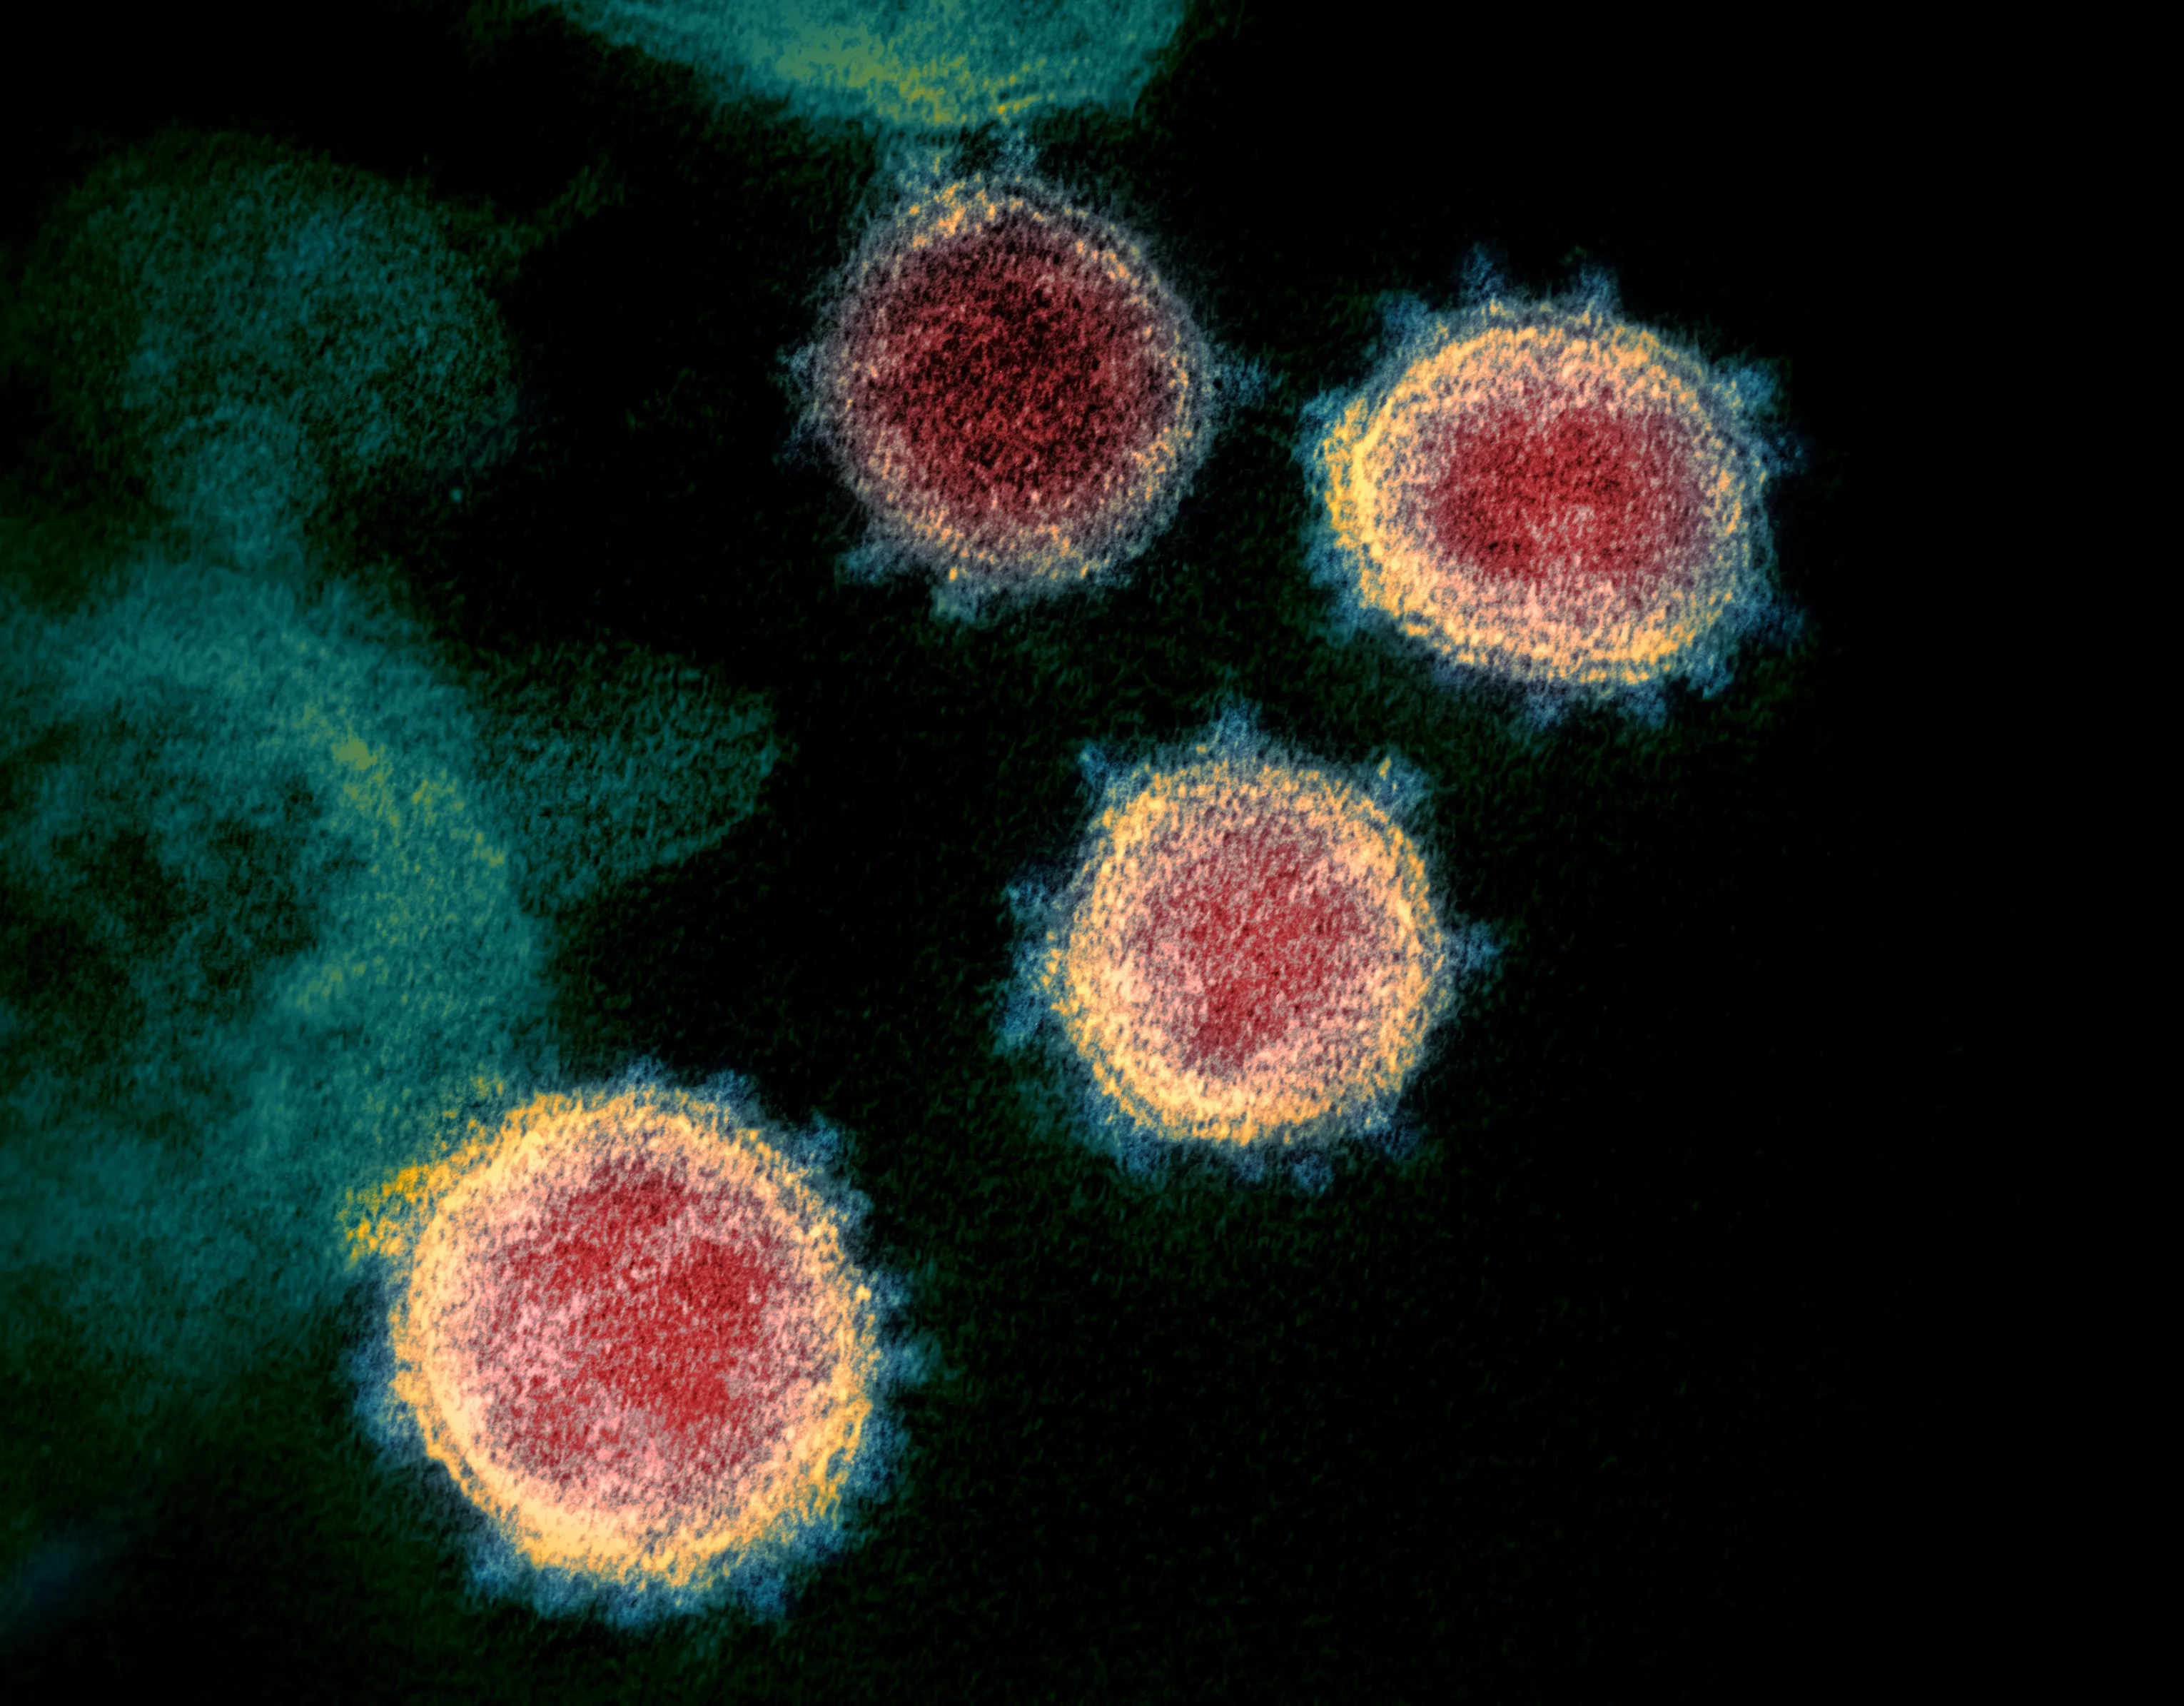

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreA new antiviral pill reduces COVID-19 hospitalization risk by 80 percent in a randomised phase 3 trial of ensitrelvir, known as Xocova in Japan. Researchers studied more than 1,200 adults with symptomatic, mild-to-moderate COVID-19, and the finding could be important for people more likely to become seriously ill.
For Australians, the headline is promising but not a guarantee that the medicine is available in every pharmacy. A positive overseas trial does not by itself authorise Australian supply, prescribing or public subsidy. Those decisions sit with Australian authorities and health professionals, who must also weigh local evidence, logistics and the needs of higher-risk communities.
The benefit also depends on when treatment begins and how high a person’s baseline risk is. It is a treatment for symptomatic infection, not a vaccine or a general immune booster. Understanding the percentages, the people studied and the Australian approval pathway is essential before deciding whether the pill changes everyday care.
The double-blind trial assigned participants with mild-to-moderate COVID-19 to ensitrelvir or a placebo. Participants had been vaccinated and had at least one risk factor, with many older than 65. The main outcome combined hospitalisation or death. Hospitalisation occurred in 4.8 per cent of the ensitrelvir group and 24.5 per cent of the placebo group, while the reported number of deaths was very low.
That gap is an 80 per cent relative reduction, not an 80 percentage-point guarantee for each person. In the trial population, it meant roughly 20 fewer hospitalisations per 100 similar high-risk patients, or about one prevented for every five people treated. Baseline risk still matters: the same percentage could save fewer lives among younger, otherwise healthy patients.
The study took place in Japan during the Omicron period, so it does not mirror every Australian infection. It did not test treatment for people already hospitalised with severe COVID-19, asymptomatic infection, children or pregnant people. Results can also vary with the variant, vaccination status, other medicines and the severity of illness at the point of treatment. The trial gives a strong signal, but its boundaries remain important.
In Australia, the Therapeutic Goods Administration assesses a medicine for use and quality before it can be listed on the Australian Register of Therapeutic Goods. Approval and supply are separate from subsidy: the Pharmaceutical Benefits Scheme determines whether eligible prescriptions receive government support, while the Commonwealth, states and private suppliers affect availability. Australians should check the current ARTG and PBS listings rather than order an overseas product based on a news headline.
Access is usually clinical. A person at higher risk may contact a GP, a telehealth service, a community pharmacy or a state-run COVID clinic after testing. Medicare can cover a GP or telehealth consultation, while an eligible PBS-listed medicine is subsidised for the patient. The familiar National Coronavirus Helpline on 1800 020 080 has directed people to local assessment and testing pathways. Public hospitals in Melbourne, Sydney, Brisbane, Adelaide and Perth, along with aged-care services from Hobart to Darwin, have handled different levels of demand.
That system still has uneven edges. Remote and regional patients may live hours from a dispensing pharmacy, and Aboriginal Community Controlled Health Services and local Aboriginal medical services play a crucial role in delivering culturally safe care. Language, disability, digital access and transport can also determine who reaches treatment quickly. Local phrases such as iso, lockdown and the Delta wave remain familiar, but practical access now depends heavily on timely testing and referral.
Antivirals are medicines, not wellness products, and safety depends on the individual. A prescriber needs to check kidney and liver function, pregnancy or breastfeeding, allergies and every regular medicine, including supplements. Interactions can be significant, particularly with drugs that affect the liver’s enzyme pathways. Treatment is also time-sensitive, so people should seek advice promptly rather than waiting to see whether symptoms worsen.
Supplement marketing can blur that distinction. An overview of niacin and cholesterol can explain why niacin is discussed for a separate lipid concern, but it does not make niacin an antiviral. High doses can cause flushing, abnormal liver tests, high blood glucose and other harm. Taking a supplement instead of assessment may also delay treatment during the window when a proven medicine could help.
The evidence hierarchy matters when headlines collapse several findings into one. The 80 per cent figure came from a controlled treatment trial, not from laboratory observations or a survey of satisfied patients. It did not establish that the pill prevents infection, protects household contacts or works after symptoms become severe. Vaccination, ventilation, staying home when unwell and early testing still have a broader role, including protection for people who cannot take an antiviral.
Even an effective oral drug depends on a functioning health system. Hospitals in Melbourne and Sydney have faced pressure from emergency admissions, staff absences and patients needing isolation, while aged-care outbreaks have affected regional areas as well as major cities. The pandemic also sharpened the phrase COVID flo: people could arrive for another illness but leave with COVID-19. Reducing hospital admissions matters because it protects beds, ambulance services and clinical teams.
Those workloads have carried a lasting human cost. Reporting on healthcare worker mental health describes the anxiety, moral injury and burnout affecting people who have repeatedly faced infection, death and disrupted care. Doctors, nurses, paramedics, cleaners, pharmacists and aged-care staff can all experience distress, even when individual cases are treated successfully.
Australian health leaders therefore have to balance outbreak control with staff support. Rostering, paid leave, confidential mental-health services and manageable workloads are not peripheral issues; they affect safe treatment and retention. Public messaging also needs to avoid blame. People who test positive after work or social contact should receive practical guidance, not stigma, because early support improves the chance they seek care when an antiviral window is open.
For an Australian who tests positive, the key question is whether they are eligible for an antiviral and whether it can be started safely and quickly. Age, chronic illness, vaccination status, symptoms and current medicines all influence the decision. A doctor can compare available oral treatments, check the latest local guidance and explain the expected benefit without overstating a population-level percentage.
| Option | What the evidence shows | Australian access position | Main limitation |
|---|---|---|---|
| Ensitrelvir in the reported trial | About 80 per cent lower relative risk of hospitalisation in vaccinated, higher-risk adults | Check current TGA and ARTG status, supply and prescribing guidance; the trial alone does not create access | The result came mainly from one Japanese trial population treated early for mild-to-moderate illness |
| Nirmatrelvir and ritonavir, sold as Paxlovid | Established benefit in reducing hospitalisation or death when started early | TGA-approved and PBS-listed for eligible higher-risk patients; check current criteria | Interactions, kidney function, pregnancy and dosing require clinical review |
| Molnupiravir | Randomised evidence of benefit, with a smaller effect than Paxlovid | TGA-approved; subsidy and pharmacy access can change | Often used when Paxlovid is unsuitable rather than as the preferred option |
| Supplements, including niacin | No reliable evidence for preventing or treating COVID-19 | May be sold without a prescription, with variable quality and doses | Potential side effects and delayed medical care |
The comparison also separates evidence from availability. A strong result in one country does not guarantee local stock, a subsidy or a place in every treatment pathway. Likewise, a familiar medicine may have a lower effect size but be more readily prescribed in Australia, while a newer option may still be reserved for particular groups or situations until local prescribing guidance is updated.
Choice also depends on practical matters: swallowing, the number of daily tablets, whether a pharmacy can dispense immediately and whether a person can attend follow-up. A treatment that is theoretically effective but difficult to start on time may offer less benefit than the headline percentage suggests. Written instructions covering doses, missed doses and adverse effects are useful, especially for older people living alone or managing several conditions.