
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
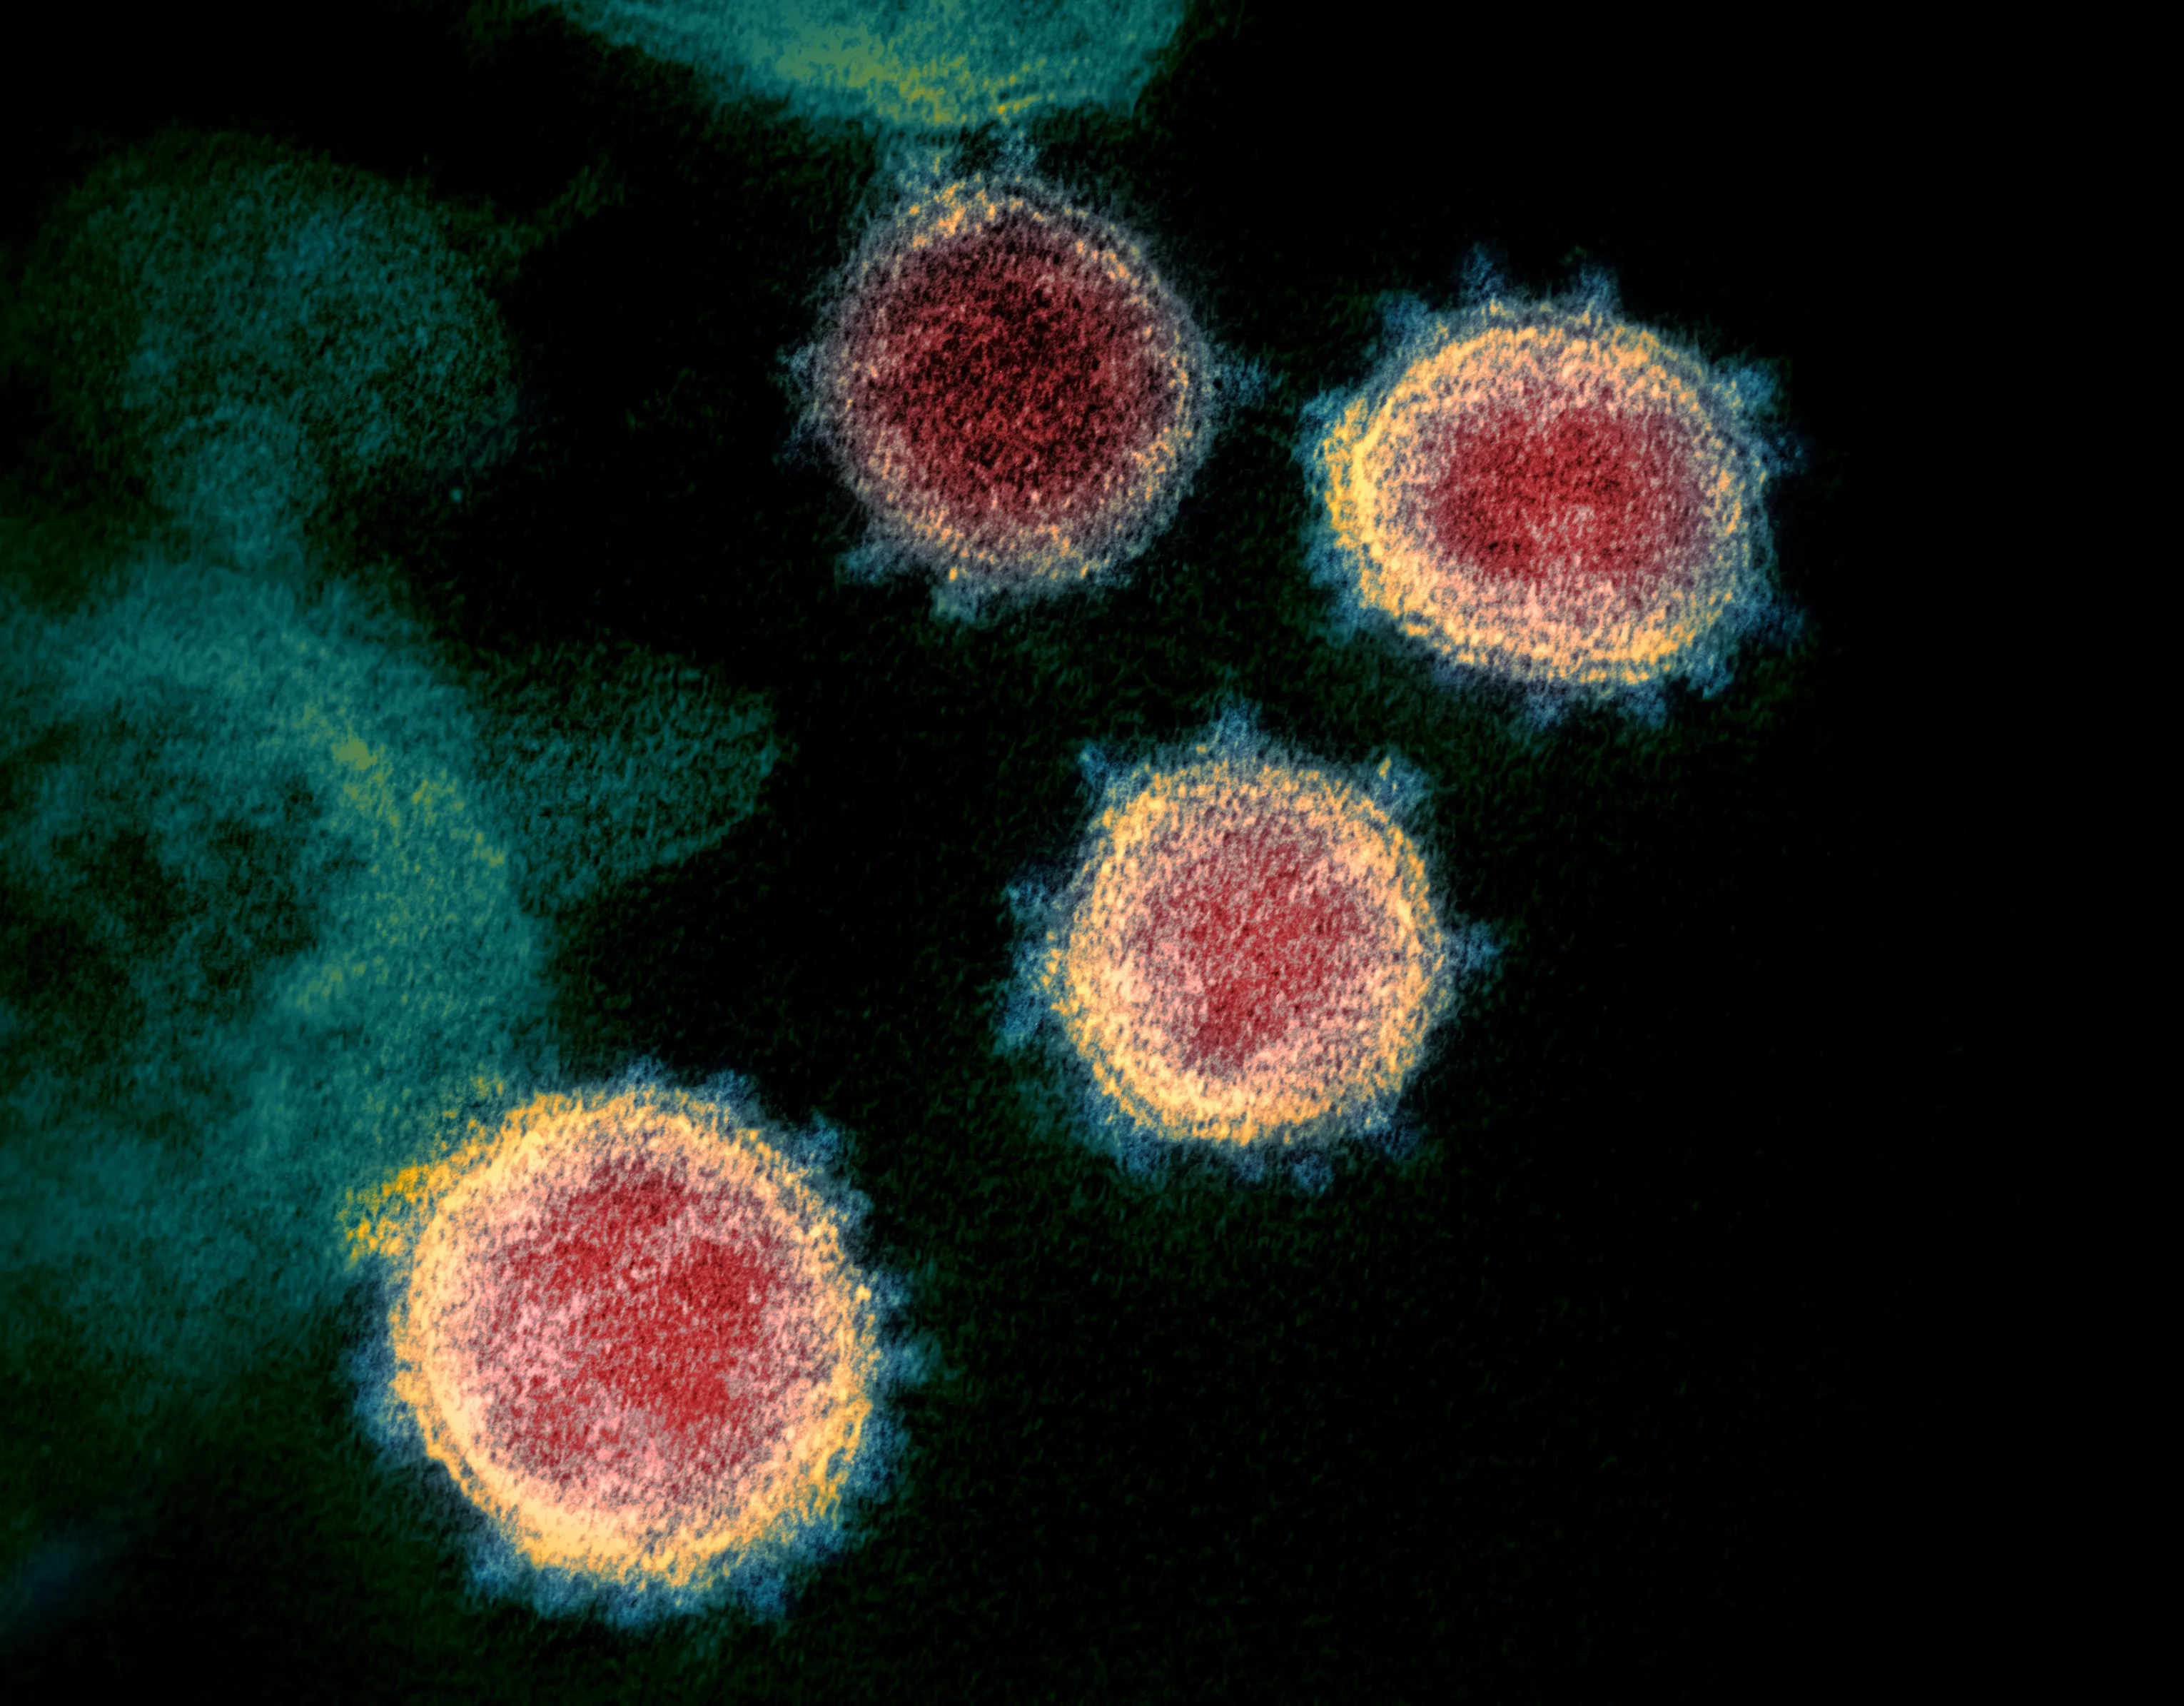

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreThe COVID-19 pandemic placed healthcare workers at the centre of a fast-moving public health emergency, exposing them to infection, exhaustion, grief and difficult decisions for months or years. Doctors, nurses, paramedics, aged-care employees, cleaners and reception staff carried the emotional weight of overflowing hospitals while trying to protect their own families. Learn more about Brooks County.org.
In Australia, the effects were felt from Melbourne’s lockdown wards and Sydney emergency departments to regional hospitals in Queensland, Western Australia and the Northern Territory. Many workers faced shifting rules, workforce shortages, cancelled leave and public anxiety. The immediate crisis has eased, yet anxiety disorders, depression, sleep problems and trauma-related symptoms continue to shape the wellbeing of the health workforce.
Healthcare workers experienced risks that were both physical and psychological. They treated patients with an unfamiliar disease while learning new infection-control procedures, working in uncomfortable personal protective equipment and worrying that they could carry the virus home. A single shift could involve resuscitation, family phone calls, staff testing and the death of several patients.
The pressure was intensified by uncertainty. Early in the outbreak, evidence about transmission, treatments and protective equipment changed rapidly. Workers had to communicate confidence to patients while privately absorbing news about rising case numbers and hospital capacity. This conflict between professional responsibility and personal fear created sustained emotional strain.
Australian hospitals also dealt with periods of intense operational disruption. Victoria’s second wave, the Delta outbreaks in New South Wales and the Omicron surge produced different pressures, including prolonged isolation requirements and large numbers of staff unavailable after exposure. In rural and remote communities, replacing a single absent clinician could be especially difficult.
Burnout is one of the clearest consequences of the pandemic. It can involve emotional exhaustion, cynicism, reduced concentration and a feeling that work has lost its meaning. A worker may still attend every shift and perform competently while feeling detached, irritable or unable to recover during time off.
Anxiety and depression have also become common concerns. Healthcare workers may fear another outbreak, worry about vulnerable relatives or feel guilty about decisions made under pressure. Some experience intrusive memories of crowded wards, distressed families or patients who deteriorated quickly. These reactions can resemble post-traumatic stress, particularly after repeated exposure to death and severe illness.
Sleep disruption often links these symptoms together. Night shifts, overtime and stress can make it difficult to rest even when a rostered day off arrives. Poor sleep then affects memory, patience and physical health, creating a cycle that can make clinical work feel even more demanding. Alcohol and other substances may become unhealthy coping mechanisms for a small but significant number of workers.
Many healthcare employees entered the profession with a strong sense of service. During COVID-19, that commitment sometimes encouraged them to ignore warning signs and accept unsafe levels of fatigue. A worker who believes patients must come first may postpone counselling, conceal distress from colleagues or use annual leave simply to recover enough to return.
Moral injury is another important part of the story. It occurs when people feel forced to act against their values or unable to provide the standard of care they believe patients deserve. During surges, clinicians had to prioritise limited beds, postpone procedures and make decisions about visitors. Even when those choices were necessary, they could leave lasting guilt.
Public attitudes added another layer. Healthcare workers were praised in public campaigns, yet some faced hostility over vaccination, mask rules or hospital restrictions. In Australia, debates that played out outside pharmacies, supermarkets and state border checkpoints sometimes followed workers into their workplaces. Being treated as a symbol of government policy could make an already difficult role feel isolating.
The emotional impact has not been evenly distributed. Nurses, paramedics and emergency staff often spent the most direct time with acutely ill patients. Intensive care teams dealt with repeated deaths and family separation, while ambulance officers worked in unpredictable environments where infection risks and long shifts overlapped.
Younger workers, casual employees and people with limited workplace control may face additional pressure. They may have less authority to change rosters, take leave or challenge unsafe practices. Internationally trained staff and workers from culturally diverse communities may also carry concerns about relatives overseas, visa security or discrimination.
The following comparison shows how pressures can vary by role and setting:
| Workforce group | Common pandemic pressures | Possible mental health effects | Helpful support |
|---|---|---|---|
| Emergency and intensive care staff | High patient acuity, deaths and rapid decisions | Trauma symptoms, exhaustion and sleep problems | Protected recovery time and clinical supervision |
| Nurses and midwives | Long shifts, staffing gaps and emotional care | Burnout, anxiety and reduced morale | Safe staffing, peer support and flexible leave |
| Paramedics | Unpredictable exposure and difficult transfers | Hypervigilance, distress and irritability | Confidential counselling and roster stability |
| Aged-care workers | Outbreaks, isolation and resident loss | Grief, helplessness and depression | Team debriefing and practical workforce support |
| Cleaners, porters and reception staff | Infection concerns and low recognition | Stress, insecurity and disengagement | Clear communication and equal access to care |
Aged-care workers deserve particular attention. Facilities became sites of fear and grief during major outbreaks, while staff had to support residents who could not see partners or children. Workers in cleaning, catering, transport and administration also faced exposure and emotional demands, even though public discussion often focused mainly on doctors and nurses.
Australia’s geography and health system shaped the crisis in distinctive ways. Large metropolitan hospitals in Melbourne, Sydney and Brisbane could draw on specialised services, although they still faced capacity problems. Smaller hospitals in Tasmania, regional New South Wales and northern Queensland had fewer backup staff and could struggle when several employees were absent at once.
For many Aboriginal and Torres Strait Islander communities, the pandemic raised concerns about access, travel and the protection of Elders. Aboriginal Health Services played a crucial role in culturally safe communication and vaccination, while health workers navigated community trust, remoteness and limited infrastructure. These pressures should be understood within the longer history of unequal health outcomes and institutional mistrust.
The local market also affected wellbeing. Rising rents, crowded housing and the cost of commuting added pressure for workers in Sydney, Melbourne and Perth. A nurse finishing a late shift may still face a lengthy trip home or difficulty finding affordable childcare. In regional areas, housing shortages and a thin pool of qualified staff can make it hard for hospitals to recruit replacements or give employees proper recovery time.
Reliable information remains part of psychological safety. Staff and communities need timely updates about cases, restrictions, vaccines and workplace procedures. International developments can be followed through global coronavirus news, while local agencies must translate broad health advice into practical guidance for hospitals, clinics and families.
Mental health support must be built into workforce planning rather than offered only after a crisis. Hospitals can provide confidential psychological services, peer programs, trauma-informed supervision and clear referral pathways. Access needs to be available during working hours, after night shifts and in regional areas, including by secure telehealth.
Work design matters just as much as counselling. Adequate staffing, predictable rosters, meal breaks and protected leave reduce the conditions that produce burnout. Managers should be trained to recognise distress without treating normal reactions as weakness. A private conversation, practical roster adjustment or temporary reduction in duties may prevent a worker from reaching breaking point.
Organisations also need to examine workplace culture. Staff are more likely to seek help when leaders respond without blame and when confidentiality is credible. Incident reviews should focus on learning rather than scapegoating. Workers who report unsafe conditions or psychological harm should be protected from retaliation.
Government policy has a role in sustaining these changes. Funding for public hospitals, aged-care services and rural health programs should account for workforce recovery, not only beds, equipment and recruitment numbers. Professional bodies and unions can help establish minimum standards for psychological safety, while universities can prepare students for the emotional realities of clinical practice.
Individual coping strategies cannot replace safe workplaces, yet they can help workers regain a sense of control. Regular sleep routines, movement, social contact and time away from clinical news may reduce stress. Simple actions such as eating during a shift, taking prescribed breaks and checking in with a trusted colleague are easy to dismiss during emergencies but important over time.
Workers should seek professional assistance when symptoms persist, interfere with relationships or affect clinical judgement. In Australia, support may come through an employee assistance program, a GP, a psychologist, a professional college or a state-based service. A GP can help assess anxiety, depression, trauma symptoms, substance use and sleep disorders, then recommend appropriate care.
Small teams can make support more visible and less stigmatised. Useful habits include:
Managers can reinforce recovery through practical decisions:
Public communication matters too. Families, patients and community leaders can reduce strain by treating health workers with respect, following safety instructions and avoiding personal abuse over contested policies. During future outbreaks, clear messages from trusted Australian health authorities will be essential to protect both public confidence and staff morale.
Recovery will not happen simply because infection numbers fall. Some workers are still processing experiences from earlier waves, while others have moved into different roles or left healthcare altogether. The loss of experienced staff creates a further burden for those who remain, increasing workload and reducing the resilience of hospitals.
Organisations should monitor workforce wellbeing over time through confidential surveys, retention data, sick leave patterns and reports of psychological injury. These measures need to be separated by profession, location and employment type so that hidden problems are not averaged away. A metropolitan hospital and a remote clinic may require very different solutions.
Local support networks can strengthen formal services. Community mental health providers, unions, Aboriginal Health Services, universities and professional colleges can coordinate training and referrals. Public information should be available in accessible language, and services should reflect the needs of culturally diverse workers and people living outside major cities.
Healthcare workers carried an extraordinary burden during COVID-19, but responsibility for their recovery cannot rest on personal resilience alone. Safe staffing, respectful leadership, affordable care and reliable information are workforce protections. Investing in those foundations will help Australia respond more effectively to future outbreaks while giving health professionals a fairer chance to recover from this one.