
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
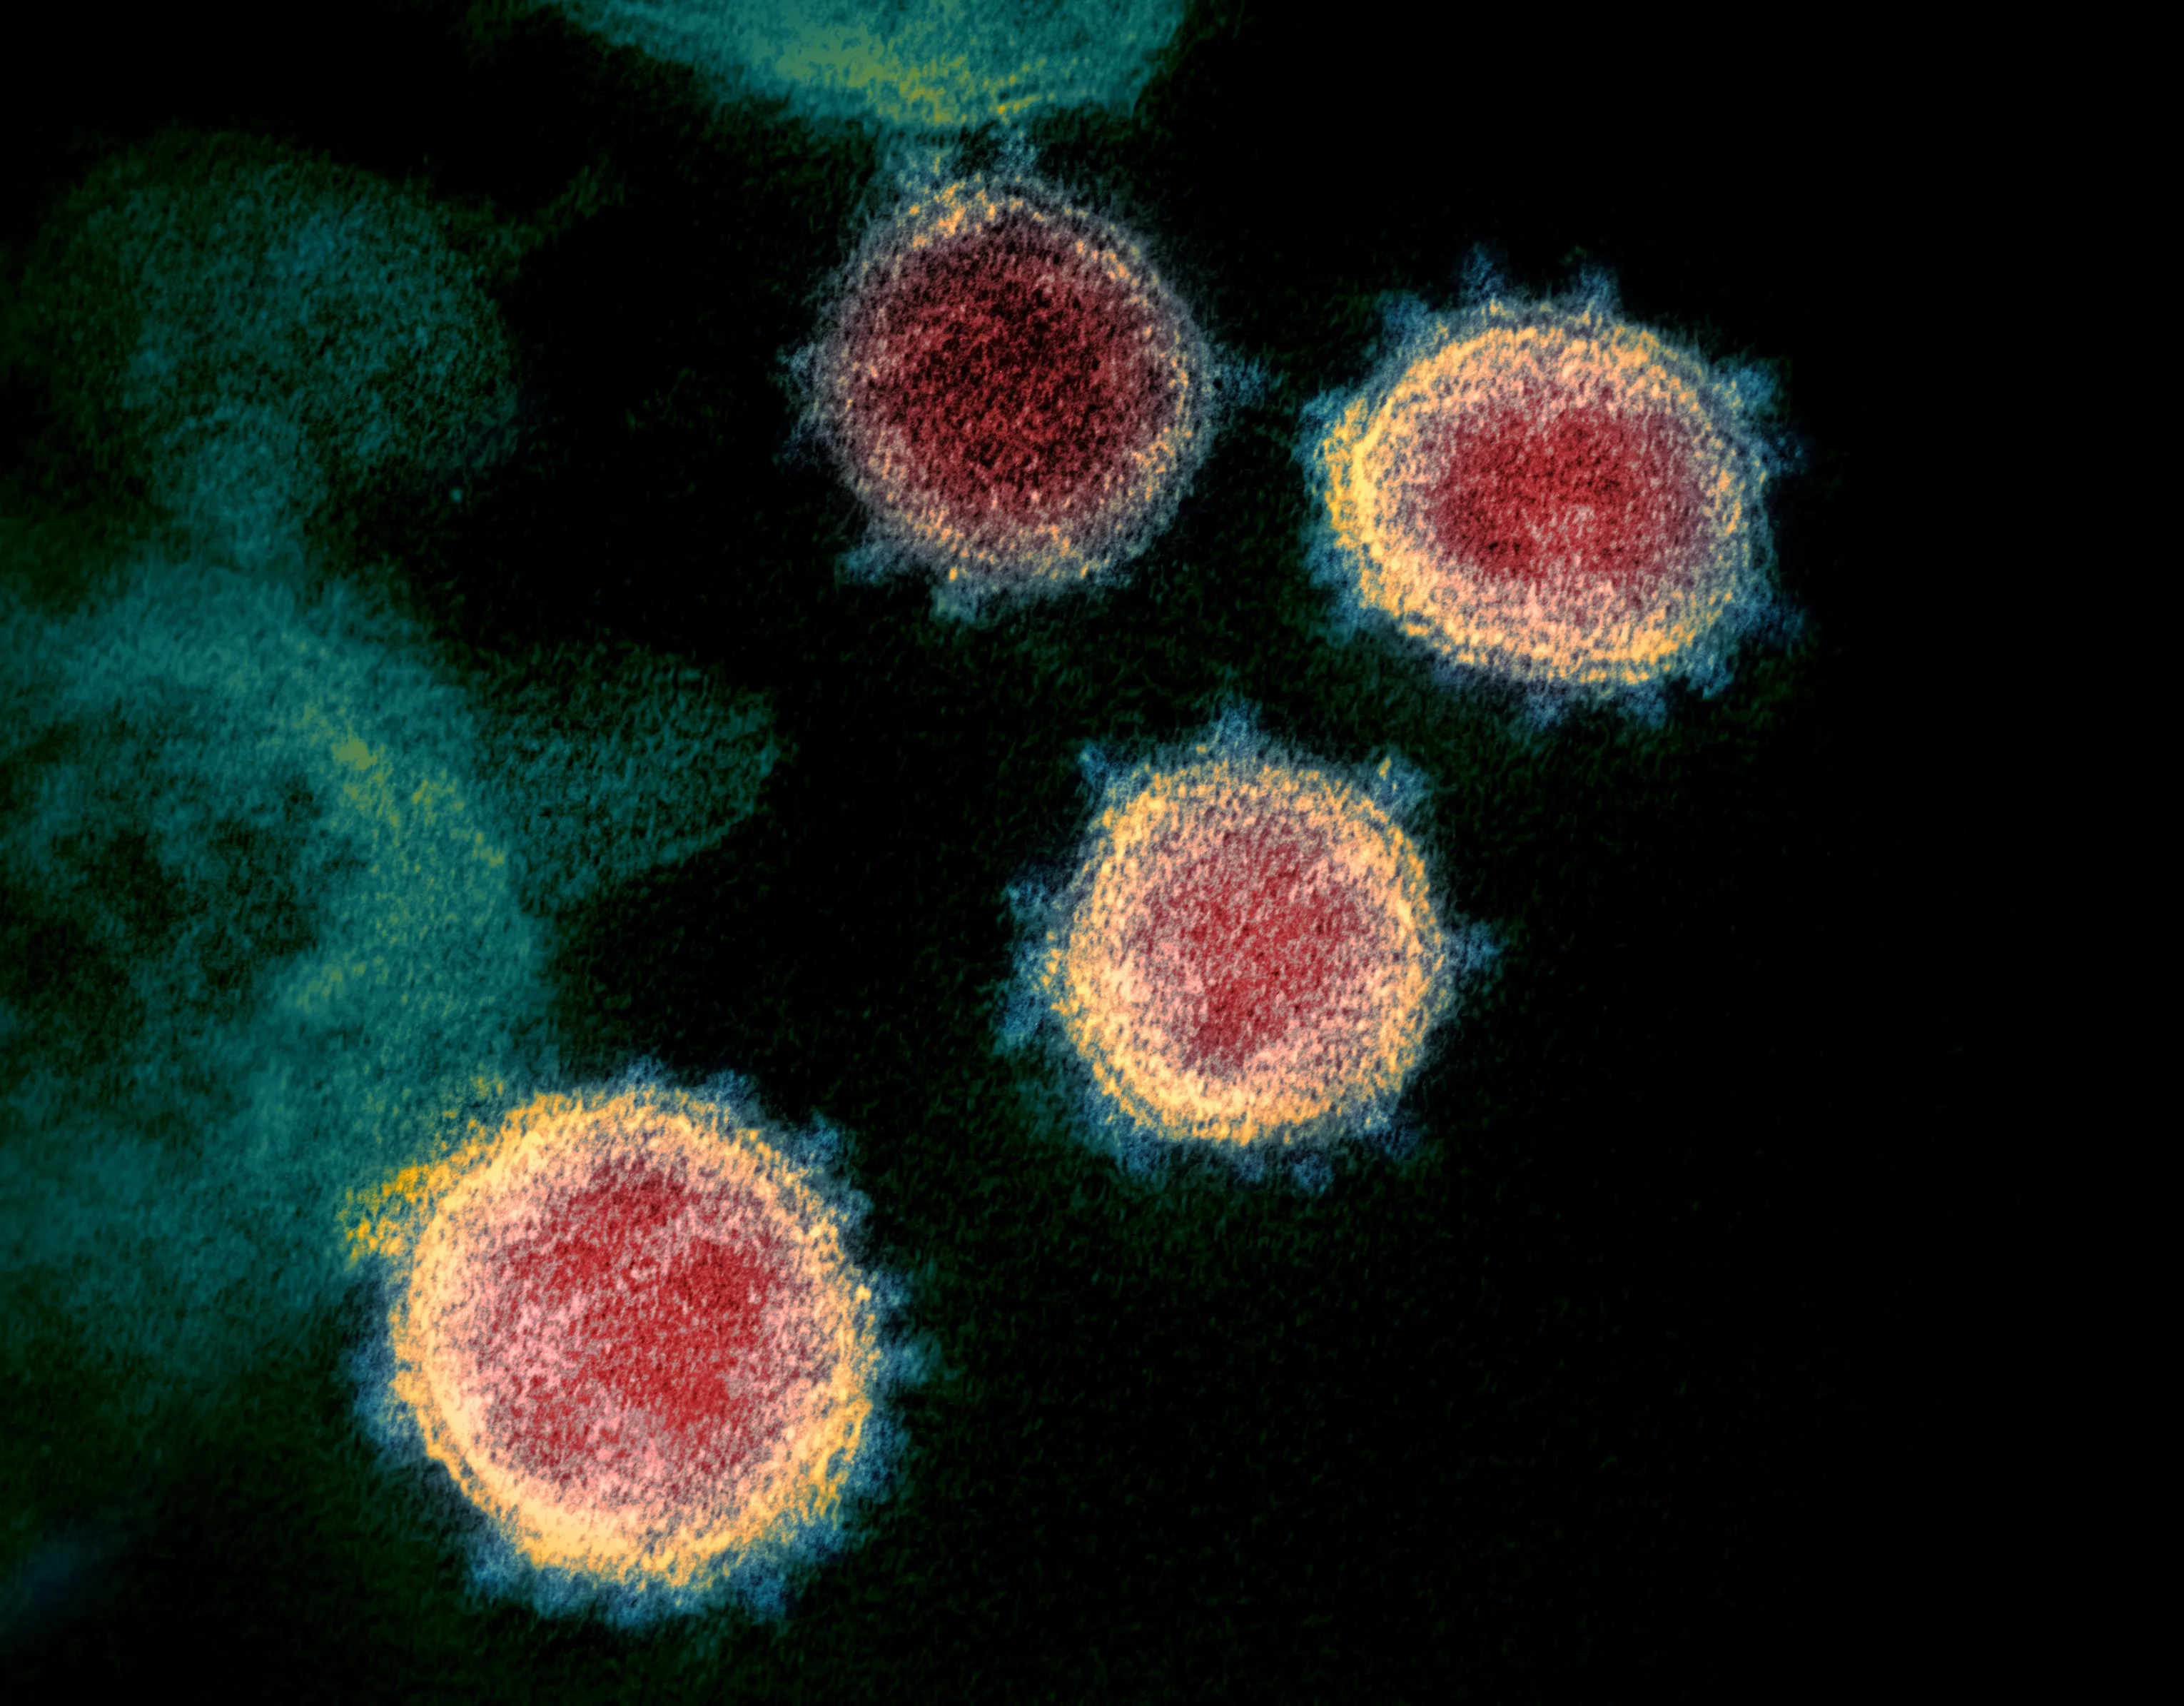

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreChinese authorities have begun tightening movement rules in parts of several major cities as COVID-19 infections rise, reversing the broader opening that followed the end of the zero-COVID era. The measures are usually narrower than the citywide lockdowns seen earlier: officials are ordering temporary stay-home orders for particular residential compounds, workplaces or districts while keeping schools, shops and transport subject to local conditions.
The renewed controls arrive as public health teams confront a familiar problem: rising case numbers can outrun testing, staffing and hospital planning even when severe illness remains comparatively limited. China’s response combines isolation, contact tracing, mask guidance and limits on gatherings, but the exact mix changes from city to city. Residents in affected neighbourhoods may face reduced access to offices, clinics or public transport.
For Australian readers, the story demonstrates how quickly outbreaks can test local capacity without implying that Australia should return to blanket restrictions. The country’s declared domestic COVID-19 pandemic period ended in May 2023, and routine case spikes are now handled through testing, vaccination, clinical guidance and state-level outbreak responses. China’s experience still matters to Australians studying travel, ageing populations and hospital readiness.
Fresh restrictions in Shanghai, Beijing and other large urban centres point to a targeted response rather than a single national shutdown. Local health commissions can seal off a residential compound, suspend work or classes in a defined area and require residents to remain home while contact tracing is completed. These orders normally carry a limited duration, although repeated testing can extend them.
| Measure | China’s renewed local response | Australia’s current framework |
|---|---|---|
| Scale | Building, compound or district restrictions rather than a nationwide shutdown | No routine citywide lockdown; state and territory authorities respond to local risk |
| Case detection | Expanded PCR or rapid testing around detected clusters | Surveillance through laboratories, GPs, pharmacies and wastewater reporting |
| Isolation | Stay-home orders and contact tracing under local rules | No automatic federal border quarantine; requirements depend on state circumstances |
| Health system | Fever clinics and designated facilities manage separation and pressure | Primary care, public hospitals and aged-care providers operate within local surge plans |
Returning to area controls carries political weight because it echoes the mass isolation policies abandoned during the reopening period. Chinese officials face pressure to contain clusters before they become citywide while avoiding the economic disruption associated with prolonged closures. Health authorities also need to show that hospitals, testing laboratories and medical teams can manage any increase in demand.
Implementation can vary sharply even between neighbouring districts. Some communities receive permission to leave for groceries, medical care or exercise, while others face more rigid instructions and checks. One affected compound can still disrupt commuting across a large metropolitan area, particularly when workers must enter a sealed workplace or use public transport that passes through controlled districts.
Several overlapping factors can contribute to a renewed infection wave. Immunity from previous infection and vaccination may decline over time, newer variants can alter immune escape, and people may spend more time indoors as weather turns colder. Dense housing, busy transport networks and substantial international travel also create opportunities for outbreaks to move quickly through connected populations.
Reported infections also depend heavily on how authorities find them. Expanded PCR or rapid testing around clusters can reveal more asymptomatic cases than a passive system focused on people seeking medical care. Testing policy, laboratory capacity and delays in publishing results can produce sharp daily variations that may resemble genuine surges in transmission.
The policy response is trying to reduce transmission without allowing hospitals to become overwhelmed. Vaccination and prior immunity can lower the probability of severe disease, but a large number of infections still creates staff absences, bed use and pressure on oxygen supplies. China’s older population and the prevalence of chronic conditions make close monitoring of hospital admissions, intensive-care demand and mortality essential.
Affected residents may be instructed to work from home, keep children away from school and avoid shared spaces. Food deliveries may need to be left at a building entrance, while access to clinics can be reorganised into separate respiratory and non-respiratory streams. For migrant workers or people living alone, the social effects of even a short stay-home order can be substantial.
Language and information gaps can make local rules harder to follow. Residents often rely on neighbourhood WeChat groups, property-management notices and translations shared by employers. Broader collections of health information resources can provide useful background, although official district notices and municipal accounts should determine the actual restrictions and their timing.
Hospitals and clinics face the challenge of maintaining routine treatment while isolating infectious patients. Dedicated fever clinics, teleconsultations and staggered outpatient appointments can reduce exposure, but they also require additional cleaners, protective equipment and clinical staff. Community testing teams and contact tracers become as important as hospital beds when the aim is to identify transmission chains early.
Readers who want a fast numerical overview can consult live case statistics, then return to official local reports for interpretation. Headline totals are useful for spotting direction, but they rarely explain why infections are rising or how serious the outbreak is. Dates, testing volumes and local reporting definitions need to accompany every comparison.
Hospital occupancy, staff absences, test positivity and severe outcomes often tell a more useful story than confirmed cases alone. Wastewater surveillance can provide an early indication of community transmission, while emergency department admissions and intensive-care referrals show whether rising infections are translating into pressure on clinical services. Each measure has delays and reporting gaps.
Raw totals should not be compared directly across jurisdictions. Countries use different testing strategies, case definitions and death classifications, and some data are revised retrospectively. This matters when Chinese city-level figures are placed beside Australian state data, especially because the two systems now operate under fundamentally different policies and expectations.
Australia no longer maintains the nationwide framework used during the early pandemic. State and territory health units have primary responsibility for outbreak control, while federal agencies provide border, vaccination and surveillance functions. A rise in cases may lead to targeted settings advice, testing campaigns or aged-care protections without producing automatic stay-home orders across an entire capital city.
For many Australians, “lockdown” remains everyday shorthand. A Sydney commuter might describe a brief office closure as a lockdown even though routine case spikes do not trigger one in NSW. In Melbourne, rapid antigen tests are widely available from chemists and supermarkets, while people in Brisbane can obtain local guidance through Queensland Health. Western Australia and South Australia publish their own alerts, so national summaries can conceal meaningful differences.
Travellers arriving at Brisbane Airport or Melbourne Tullamarine should check current Chinese entry rules through the airline and Australian Smartraveller advice before departure. Recent contact with an infectious person may warrant testing and staying away from others while symptoms develop. Australian healthdirect on 1800 022 222 can provide clinical guidance, with emergency services contacted for urgent symptoms such as breathing difficulty, confusion or collapse.
COVID-19 can affect more than the lungs, and the possible neurological consequences remain an active area of research. A linked brain inflammation review examines evidence linking infection with neuroinflammation and, in some cases, neurological injury. The findings indicate biological mechanisms worth investigating, but they do not mean every neurological symptom after infection has the same cause.
People recovering from COVID-19 may experience fatigue, headaches, concentration problems or dizziness for varying periods. New weakness, seizures, severe headache, confusion or loss of consciousness require prompt medical assessment rather than being dismissed as ordinary after-effects. Older patients and residents of Australian aged-care facilities need particularly close observation because an infection can cause rapid changes in mobility, hydration and cognition.
Reliable interpretation therefore depends on more than a dramatic headline. Test positivity, hospital capacity, severe outcomes, vaccination uptake and transparent local communication reveal whether containment measures are working. The central issue in China’s renewed restrictions is whether targeted surveillance and clinical capacity can keep pace with transmission before local outbreaks broaden, while Australia continues building the resilience needed for future waves without repeating the social and economic costs of widespread shutdowns.