
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
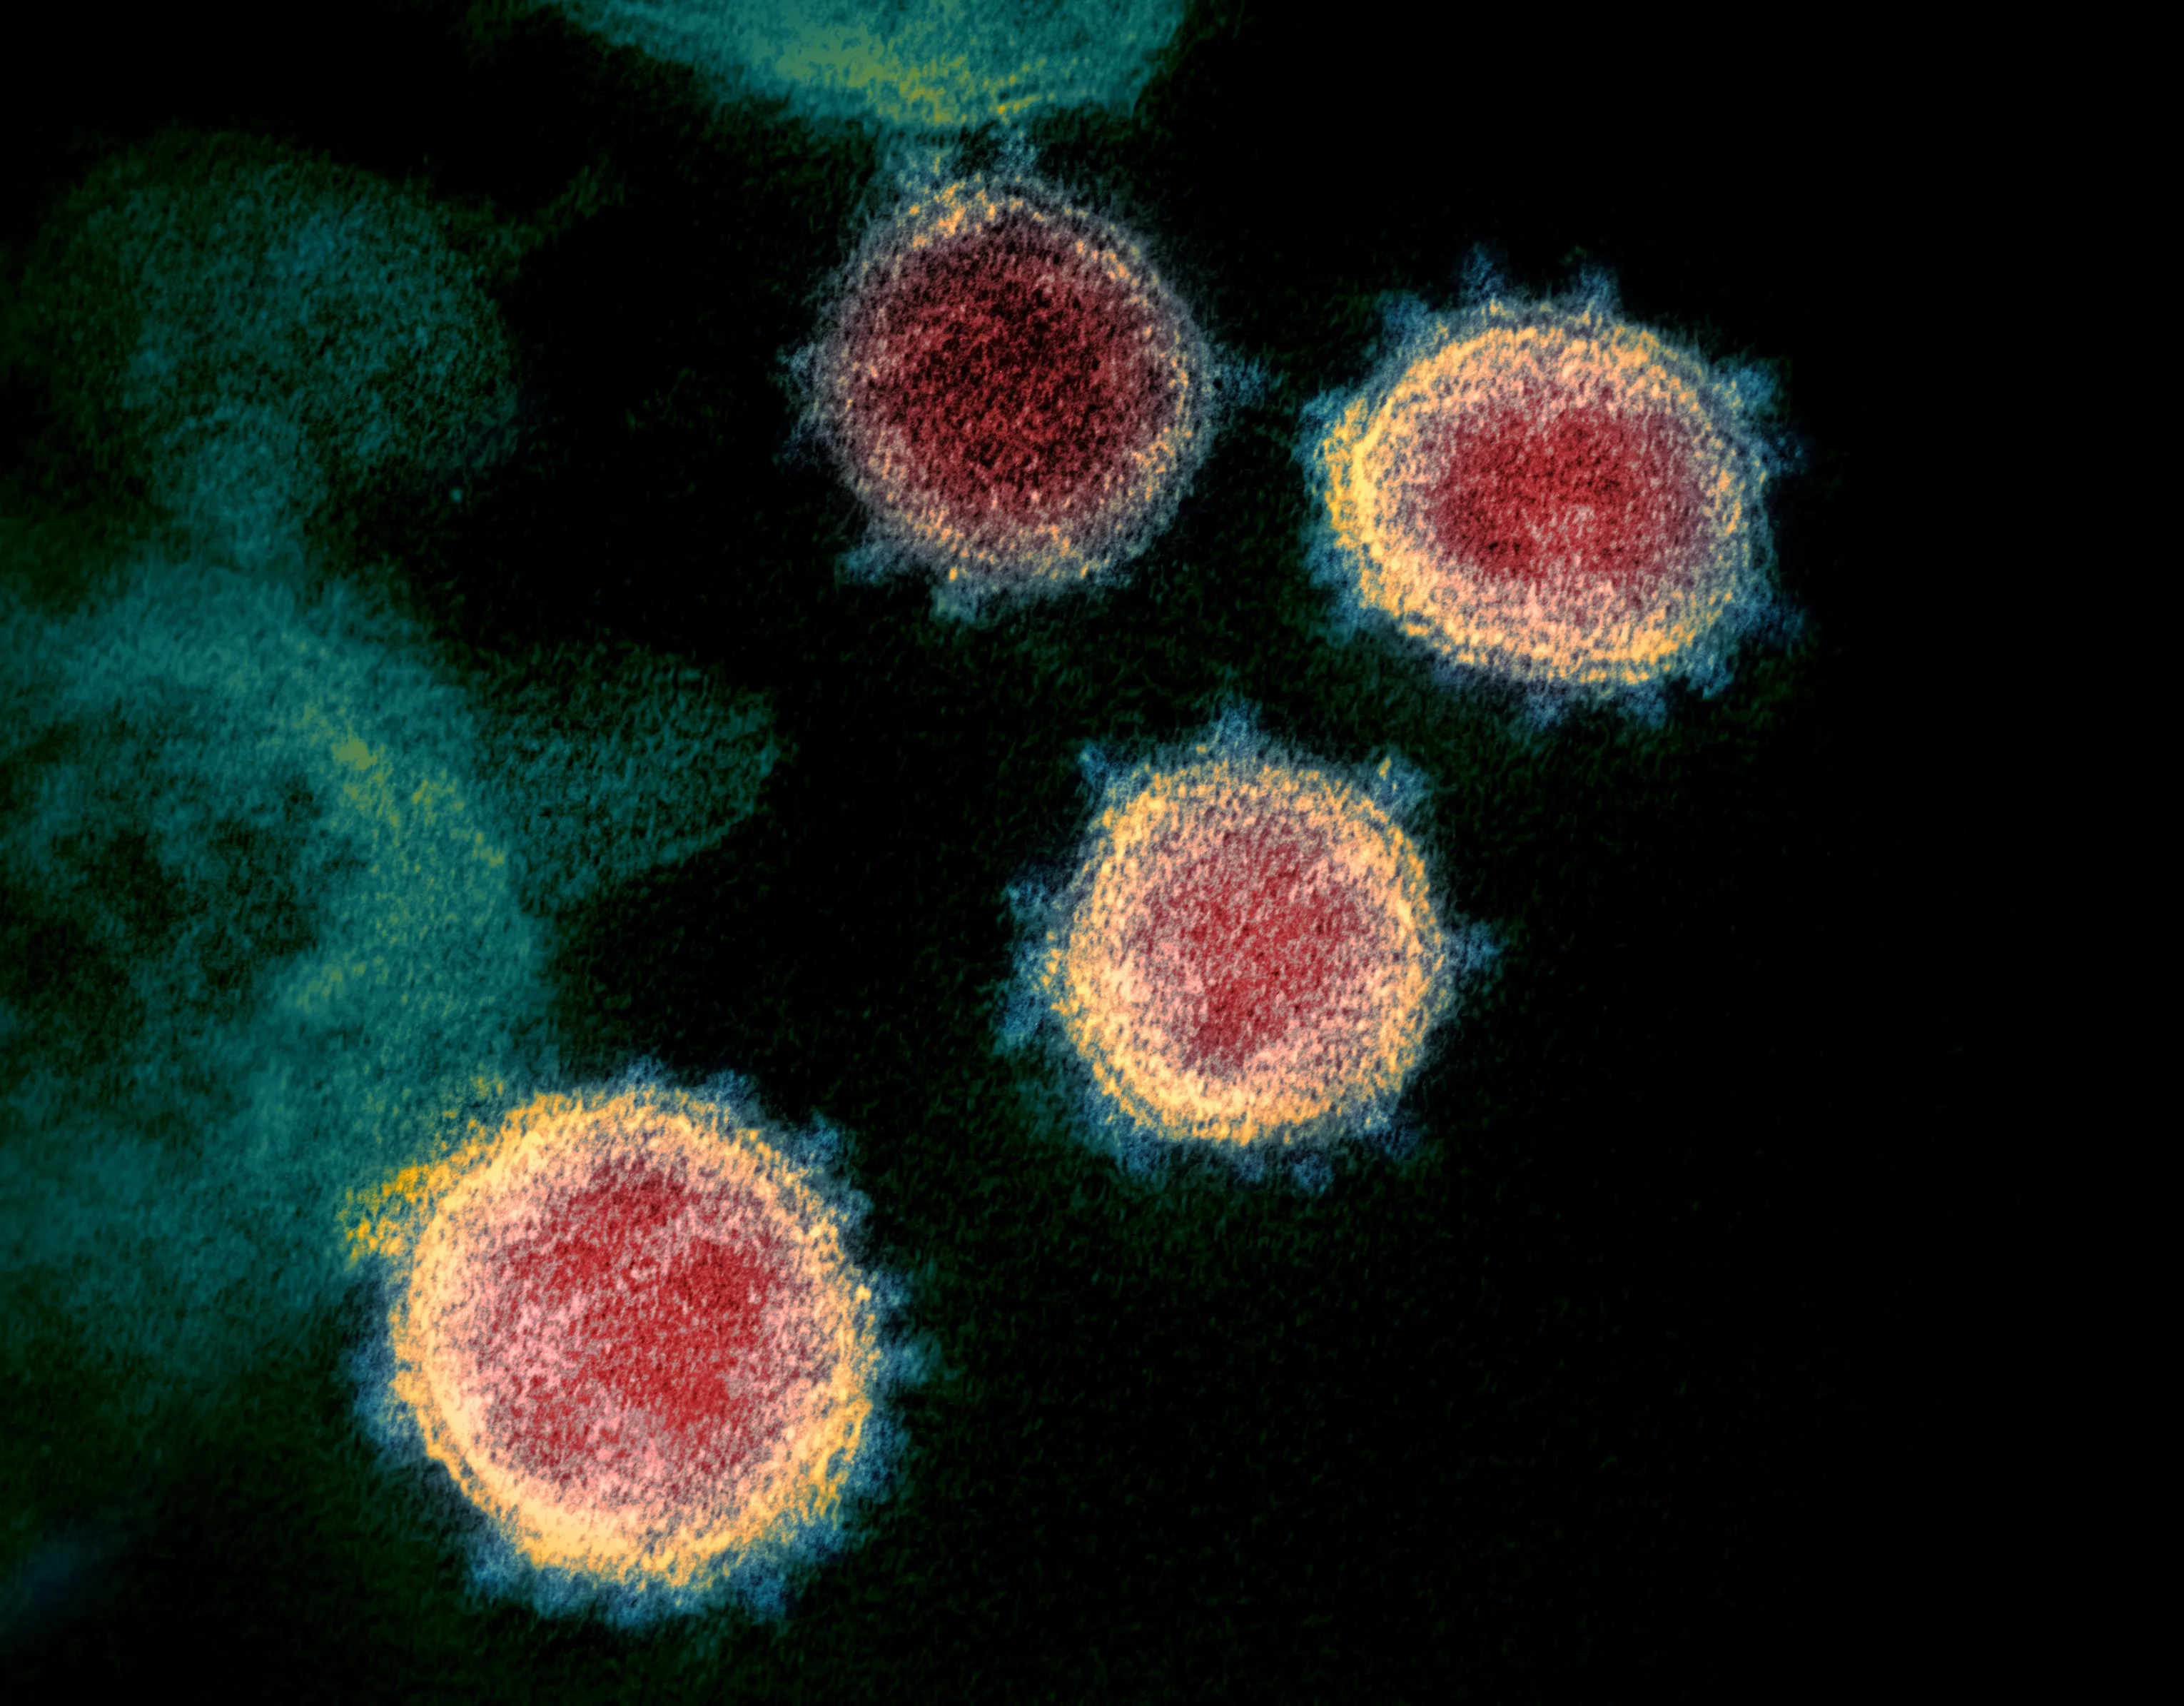

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreSouth Africa paused the rollout of the Oxford-AstraZeneca COVID-19 vaccine in February 2021 after preliminary research suggested that the jab offered limited protection against mild to moderate illness caused by the B.1.351 variant, now commonly associated with the country. The decision arrived just as millions of doses were ready for use, turning a scientific finding into an immediate public-health and logistical problem.
The pause did not mean the vaccine was unsafe. It reflected uncertainty about how well the vaccine prevented symptomatic infection from a fast-spreading variant. Researchers and health officials still believed vaccination could provide meaningful protection against severe disease, hospitalisation and death, but the available trial data did not yet answer those questions with enough confidence for South Africa’s immediate strategy.
South Africa received its first major AstraZeneca shipment in early February 2021, with plans to use it for healthcare workers. The vaccine had shown strong protection against the original strain and had already been authorised in several countries. Its relatively simple storage requirements made it particularly attractive for large-scale distribution, including areas where ultra-cold freezer capacity was limited.
A small clinical trial involving younger adults produced the concern. Participants who received AstraZeneca’s vaccine appeared to have only modest protection against mild or moderate COVID-19 caused by B.1.351. The study was too small to establish whether the vaccine prevented serious outcomes, so the evidence did not justify declaring the product ineffective across the board.
South African officials therefore chose to delay administration while scientists examined alternatives. The decision illustrated how quickly a new variant could change vaccine policy. A product that remained useful against one version of the virus might perform differently when mutations altered the spike protein targeted by the immune response.
The B.1.351 variant carried several mutations in the spike protein, including changes in a region that helps the virus attach to human cells. Some of those mutations appeared to reduce the ability of antibodies generated by previous infection or vaccination to neutralise the virus. Similar concerns were being studied with variants first detected in the United Kingdom and Brazil.
Protection against infection is only one measure of a vaccine’s value. A vaccine may become less effective at stopping every case while continuing to reduce the likelihood of pneumonia, intensive-care admission and death. Early clinical signals from several vaccines suggested that cellular immunity and other immune responses could still help prevent the worst consequences of infection, even when antibody protection was weakened.
That distinction mattered in South Africa, where the goal was to reduce pressure on hospitals as well as slow transmission. A temporary pause allowed officials to consider whether AstraZeneca could be redirected to areas where the variant was less prevalent, used alongside another vaccine, or reserved for a later booster programme adapted to the new strain.
The episode also highlighted the limits of early trial results. The AstraZeneca study had a relatively young participant group and few severe cases, meaning it could not reliably measure protection from hospitalisation or death. Headlines describing the vaccine as a failure risked confusing reduced protection against mild infection with an absence of all health benefits.
South Africa moved towards the Johnson & Johnson vaccine for healthcare workers after reviewing early evidence that a single dose provided substantial protection against severe COVID-19 caused by the local variant. The vaccine’s one-dose schedule and ordinary refrigerator storage were practical advantages for a country managing a broad and sometimes difficult-to-reach population.
The Pfizer-BioNTech vaccine was another option, although its two-dose schedule and colder storage requirements created operational complications. Supplying a national programme requires more than purchasing doses. Authorities must manage transport, refrigeration, appointment systems, trained staff, consent procedures, adverse-event monitoring and public communication.
AstraZeneca’s future role was left open rather than permanently rejected. Vaccines can be modified, and booster doses may be designed to target variants that escape some existing immunity. The pause also gave manufacturers and researchers time to study whether a revised dosing interval, a variant-specific formulation or a combination of vaccine platforms would improve protection.
Public confidence became a central issue. People waiting for a jab could interpret a pause as evidence that vaccines were dangerous, while people already vaccinated might worry that their dose had become worthless. Clear explanations were essential: the concern involved performance against a particular variant, not evidence that the vaccine caused COVID-19 or posed an unusual safety threat.
For Australia, the South African decision was relevant even though local transmission levels were far lower at the time. The Therapeutic Goods Administration assessed vaccine quality, safety and effectiveness, while the Australian Technical Advisory Group on Immunisation provided expert advice on how approved products should be used. Approval and policy advice were separate steps, allowing Australia to consider local conditions and emerging international evidence.
Australia also had its own supply and manufacturing questions. CSL’s Melbourne facility was contracted to produce millions of AstraZeneca doses, making the vaccine important to the national rollout. A change in international guidance could therefore affect production schedules, public expectations and the mix of vaccines offered through general practices, hospitals and vaccination clinics.
Everyday conditions shaped the risk calculation. A resident in Sydney or Melbourne might encounter a GP appointment system, a state-run vaccination hub or a pharmacy, while someone in regional Queensland, Western Australia or the Northern Territory could face longer travel distances and fewer appointment options. The vaccine’s standard refrigerator storage was useful for distribution across a country with large remote areas.
Australian legislation also formed part of the response. The Biosecurity Act 2015 supported federal measures at the border, while state and territory public-health orders governed isolation, quarantine and local restrictions. Mask rules, limits on indoor gatherings and testing requirements could be changed quickly when an outbreak occurred, as communities in Melbourne and Sydney experienced during earlier waves.
Local habits mattered too. Australians had become accustomed to checking state exposure sites, carrying masks on public transport and scanning QR codes when entering cafés, shops and workplaces. These measures reduced transmission opportunities while vaccination expanded, although they could not replace immunisation as a long-term strategy.
The South African pause demonstrated why vaccine announcements require careful wording. Saying that AstraZeneca had “failed” would have been inaccurate, because the evidence addressed mild and moderate disease from one variant in a limited trial. Saying there was “no problem” would have been equally misleading, because reduced protection against symptomatic infection could still affect transmission and healthcare demand.
Authorities needed to explain relative risk in terms people could understand. The key questions were whether a vaccine reduced severe illness, whether its benefits outweighed its risks, and how well it worked against the strains circulating in a specific location. Those answers could differ between countries and could change as the virus evolved.
Political debate also influenced the public response. Governments were under pressure to secure doses, meet delivery targets and avoid wasting supplies, while health agencies had to respond to new evidence without appearing indecisive. Readers following the wider debate can compare this episode with international policy coverage, though vaccine decisions should ultimately be judged against clinical evidence and advice from recognised health authorities.
The communication challenge was particularly important for Australia’s diverse population. Messages needed to reach people through GPs, state health departments, pharmacies, workplaces and multilingual community organisations. A single national announcement could not address every concern about eligibility, side effects, appointment access or the difference between vaccine effectiveness and vaccine safety.
The controversy reinforced the value of flexible vaccine programmes. Governments need several supply options, reliable surveillance and the ability to change recommendations when variants alter the balance of benefits. A rollout built around one product can become vulnerable if manufacturing is delayed, a variant reduces effectiveness or new safety information changes eligibility.
It also showed that vaccination policy cannot be separated from public behaviour. Even after a person receives a dose, masks, ventilation, testing and isolation may remain important while community transmission is high. In Australia, this could mean continuing caution on crowded trains in Sydney, busy indoor venues in Melbourne or travel between states during an outbreak.
Incentives have since appeared in different forms around the world, from workplace arrangements and easier access to vaccination centres to state-backed prize schemes. Coverage of later US programmes, including vaccine lottery coverage, shows how governments experimented with encouraging uptake. Incentives may attract attention, but trust, convenient appointments and honest information remain more durable foundations.
The main lesson is that a pause can be part of responsible vaccine governance. South Africa acted when early evidence raised a credible question, then adjusted its approach as more data became available. For Australia and other countries, the episode encouraged closer variant surveillance, diversified procurement and public updates that distinguished uncertainty from danger.
| Issue | What the South African evidence suggested | Relevance for Australia |
|---|---|---|
| Protection against mild illness | AstraZeneca offered reduced protection against mild or moderate disease caused by B.1.351 | Effectiveness needed to be assessed against strains circulating locally |
| Protection against severe disease | The trial was too small to provide a firm answer, so severe-outcome protection remained uncertain rather than disproven | Hospitalisation and death were critical measures for Australian policy |
| Vaccine safety | The pause concerned effectiveness against a variant, not a newly identified safety problem | Safety monitoring by the TGA and state health systems remained essential |
| Storage and delivery | AstraZeneca was easier to store than vaccines requiring ultra-cold conditions | Refrigerator storage supported distribution through Australian clinics and regional services |
| Public confidence | Abrupt policy changes risked confusion and vaccine hesitancy | Clear advice from the TGA, ATAGI, GPs and state health departments was necessary |
| Future use | The vaccine might still have value against other strains or in an updated formulation | Flexible procurement and variant surveillance could guide later boosters |
The decision in South Africa was therefore a warning about viral evolution rather than a final verdict on one vaccine. It showed how clinical results, variant surveillance, manufacturing capacity, legislation and public trust must work together when a pandemic changes faster than national plans.