
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
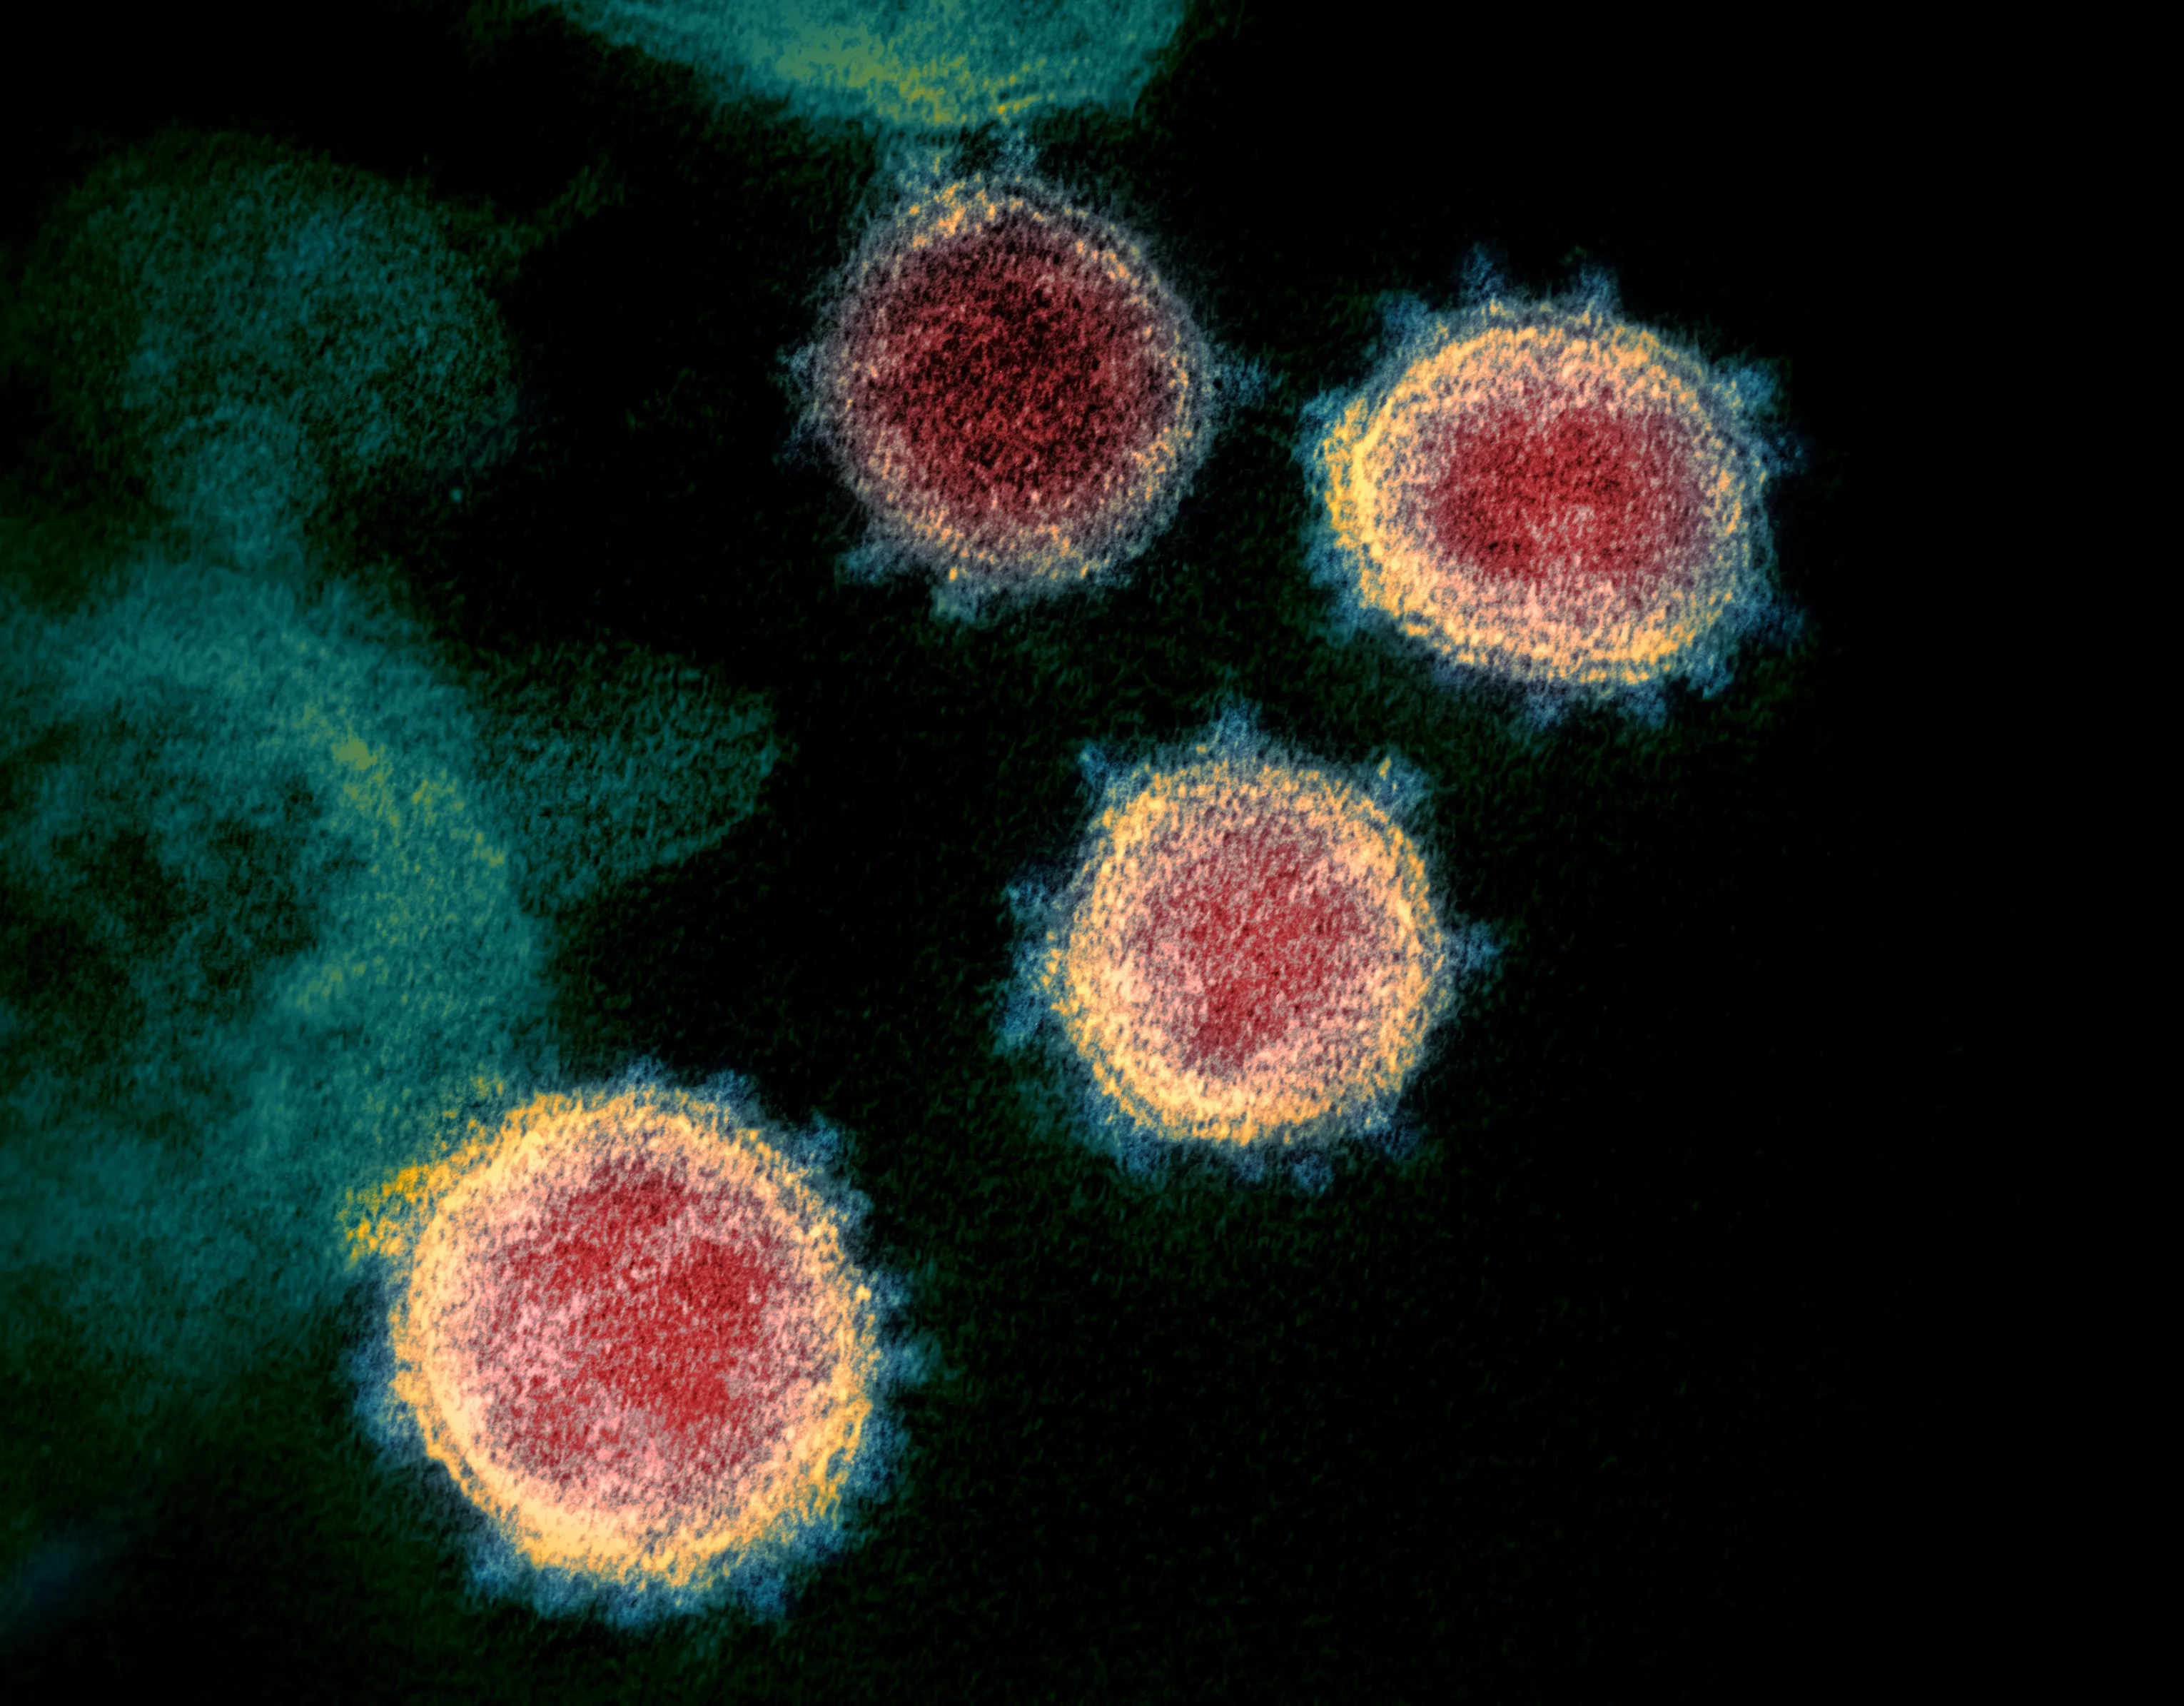

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreThe World Health Organization's endorsement of convalescent plasma gives hospitals a conditional option for treating hospitalised COVID-19 patients who need oxygen. Announced in 2020 and carried into later living guidance, the decision did not make plasma a universal or stand-alone treatment. It supported use within established clinical care while researchers continued gathering evidence.
Convalescent plasma is the antibody-containing part of blood donated by someone who has recovered from COVID-19. It differs from monoclonal antibody medicines, which are manufactured to target a defined viral component. Donor plasma contains a broad mix of antibodies and other protective proteins, so its potency can differ substantially between donors and against different variants.
Reports that WHO “approves” a treatment can obscure the distinction between a scientific recommendation and national regulatory approval. WHO does not authorise drugs for sale; it assesses evidence and publishes guidance. Member-country regulators and health systems then decide whether and how to provide a therapy. Convalescent plasma therefore depends on local blood-collection rules, hospital protocols and informed consent.
For Australians, the issue is practical rather than abstract. Recovered patients can contribute plasma through Australian Red Cross Lifeblood and participating state health services, while public and private hospitals decide whether a patient is eligible. Sydney and Melbourne have supported collection and transfusion programs, and local guidance from NSW Health, the Victorian Department of Health and other state authorities remains more relevant than a generic WHO statement.
WHO's position has always been limited to a defined clinical setting. The conditional recommendation concerned hospitalised patients with COVID-19 who required oxygen, not healthy people, exposed contacts or people with mild disease treated at home. It did not endorse plasma for routine prevention, and it did not replace vaccination, antiviral assessment, corticosteroids when appropriate, or supportive respiratory care.
The wording also matters for doctors and patients. WHO suggested that suitable plasma could be used as part of a holistic treatment plan while trial evidence remained limited. Later analyses and living-guideline updates have not turned it into an open-ended promise. Recommendations can narrow as data improve, which is why the current national protocol and product information should take priority over an old news headline.
Donor recruitment begins with people who have recovered from a laboratory-confirmed infection and meet strict eligibility criteria set by the blood service and relevant health authority. Applicants give a health history, undergo infection-screening tests and may need to demonstrate a suitable interval since recovery. The process is more demanding than donating ordinary whole blood because every unit must be traced, tested and accepted under a controlled collection programme.
Plasma is separated through plasmapheresis, with red cells and other components returned to the donor. Laboratories measure antibodies, often reporting a titre that indicates neutralising strength. High-titre units are generally preferred where the clinical question is antiviral activity. Donors are also matched by blood group, and some programmes consider whether their antibodies remain useful against the variant then circulating locally.
At the hospital end, an approved protocol determines when a transfusion is justified, which product is suitable and how closely the patient is monitored. Timing can influence results, particularly whether treatment begins before severe inflammation develops. Plasma is not a retail medicine sold by the vial in Australia; it is a supervised blood component or investigational product, administered through the transfusion service rather than an online pharmacy.
Early studies reported encouraging signals, including improved oxygen requirements in some severely ill patients. Those findings came largely from observational cohorts, where improvements could also reflect other treatments or the natural course of illness. Randomised studies produced a more mixed picture, suggesting that benefit may depend on disease stage, antibody concentration and the care given alongside plasma. Evidence is strongest as a conditional option, not as a general cure.
Donor matching becomes harder when variant information is incomplete. A CoronavirusNewsLive report on global testing shortages explains how reduced testing and sequencing can obscure which variants are spreading and weaken efforts to assess whether donated antibodies remain effective. Better surveillance is therefore part of evaluating the therapy, not merely a separate epidemiological concern.
| Approach | Main purpose | Role in a hospital pathway | Key limitation |
|---|---|---|---|
| Convalescent plasma | Supplies a broad mixture of donor antibodies | May be considered under protocol for patients needing oxygen | Donor potency, timing and supply vary |
| Corticosteroids | Controls harmful inflammation in severe illness | Standard adjunct when oxygen is required | Not antiviral and requires clinical selection |
| Monoclonal antibodies | Delivers manufactured, targeted antibodies | Available only when authorised, active and in stock | Variant resistance and limited durability |
| Oxygen and supportive care | Maintains breathing and monitors complications | Foundation of hospital treatment | Severe disease can progress despite support |
These approaches are not interchangeable, and a patient may need more than one. Plasma cannot supply oxygen or control every inflammatory pathway. Its value lies in adding passive antibody when local evidence, product quality and clinical circumstances justify that specific intervention.
In Australia, the Therapeutic Goods Administration oversees the safety and regulatory framework for blood and plasma products under the Therapeutic Goods Act 1989. State and territory health services, the National Blood Authority and Australian Red Cross Lifeblood operate much of the collection and supply network. During an outbreak, recovered-donor recruitment and priority access to units are coordinated through those public systems, with any research use covered by ethics and governance requirements.
Collection has been visible in major cities. NSW Health and Lifeblood services in Sydney have run recovered-donor clinics and hospital collections, while Victorian services have used similar networks in Melbourne and regional centres. These programmes depend on volunteers returning after infection, not on buying a speculative treatment. Donors are told that their plasma may help another patient, although they cannot be promised a direct clinical benefit.
Australia's plasma market has a distinctive structure. CSL Behring operates plasma-derived manufacturing at Broadmeadows in Melbourne, producing medicines such as immunoglobulin and clotting factors from donated plasma. That commercial manufacturing stream is separate from the recovered-patient plasma pathway used for COVID-19 treatment. Convalescent plasma is generally supplied to eligible patients through a hospital blood service rather than sold openly in pharmacies.
Federal biosecurity powers and state public-health laws shape the surrounding response. The Commonwealth Biosecurity Act 2015 provides a framework for managing biosecurity risks, while measures such as isolation requirements and emergency orders have generally been enacted through state legislation, including NSW's Public Health Act 2010 and Victoria's Public Health and Wellbeing Act 2008. This layered system means donor recruitment and local treatment eligibility can differ across a border.
Everyday habits also affect how safely the system functions. Australians are accustomed to staying home when acutely unwell, although pandemic-era guidance made that expectation more visible. Checking local health alerts, improving indoor ventilation and wearing masks in crowded clinics or on public transport during respiratory surges help protect blood donors, reduce pressure on hospitals and preserve a stable donor pool for patients who need plasma for other conditions.
Transfusion medicine applies strict safeguards because donor blood can carry infectious risks or cause reactions. Screening includes viruses such as HIV, hepatitis B and hepatitis C, while donation history and recent travel are reviewed. Compatibility testing, informed consent and close observation help manage risks including allergic reactions, fluid overload and transfusion-related lung injury. Clinicians balance those hazards against the severity of the illness and the expected benefit.
Vaccine safety scrutiny is separate from plasma effectiveness, but both require careful interpretation of rare events. A WHO investigation into rare blood clotting examined exceptionally uncommon events after COVID-19 vaccination. Such investigations assess signals and causality; they do not show that every serious illness following vaccination was caused by it, nor that blood products can prevent the same events.
Plasma also carries a specific biological concern: antibodies that do not neutralise the virus could theoretically worsen infection, a risk often called antibody-dependent enhancement. Evidence for harm in carefully selected hospital use is limited, but it supports early donor screening, product testing and a narrow treatment threshold. Vaccination remains the more reliable way to reduce severe infection and should not be delayed in the hope of obtaining convalescent plasma.
For a patient, the recommendation translates into a set of clinical checks. Doctors consider oxygen level, disease duration, existing treatments, blood-group compatibility and the availability of a suitably tested unit. Families may be told that the treatment is experimental or conditional in some settings, and that the chance of benefit can differ sharply between early and late disease. Clear consent documents should describe both the hoped-for effect and known transfusion risks.
Communication is especially important because the scientific position has evolved. A recommendation from 2020 is not the same as a permanent declaration, and local guidance can change as variants, case patterns and evidence move. Digital trust also depends on explaining uncertainty without exaggeration; readers seeking a wider perspective on online information can consult Tazkra online.
The lasting policy lesson is that convalescent plasma occupies a narrow but genuine place. It is neither a replacement for vaccination nor a reason to abandon proven supportive care. Where Australian blood services can supply high-quality units and hospitals have evidence-based protocols, the WHO endorsement gives clinicians a framework for weighing individual benefit while continuing to measure outcomes in real-world use.