
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
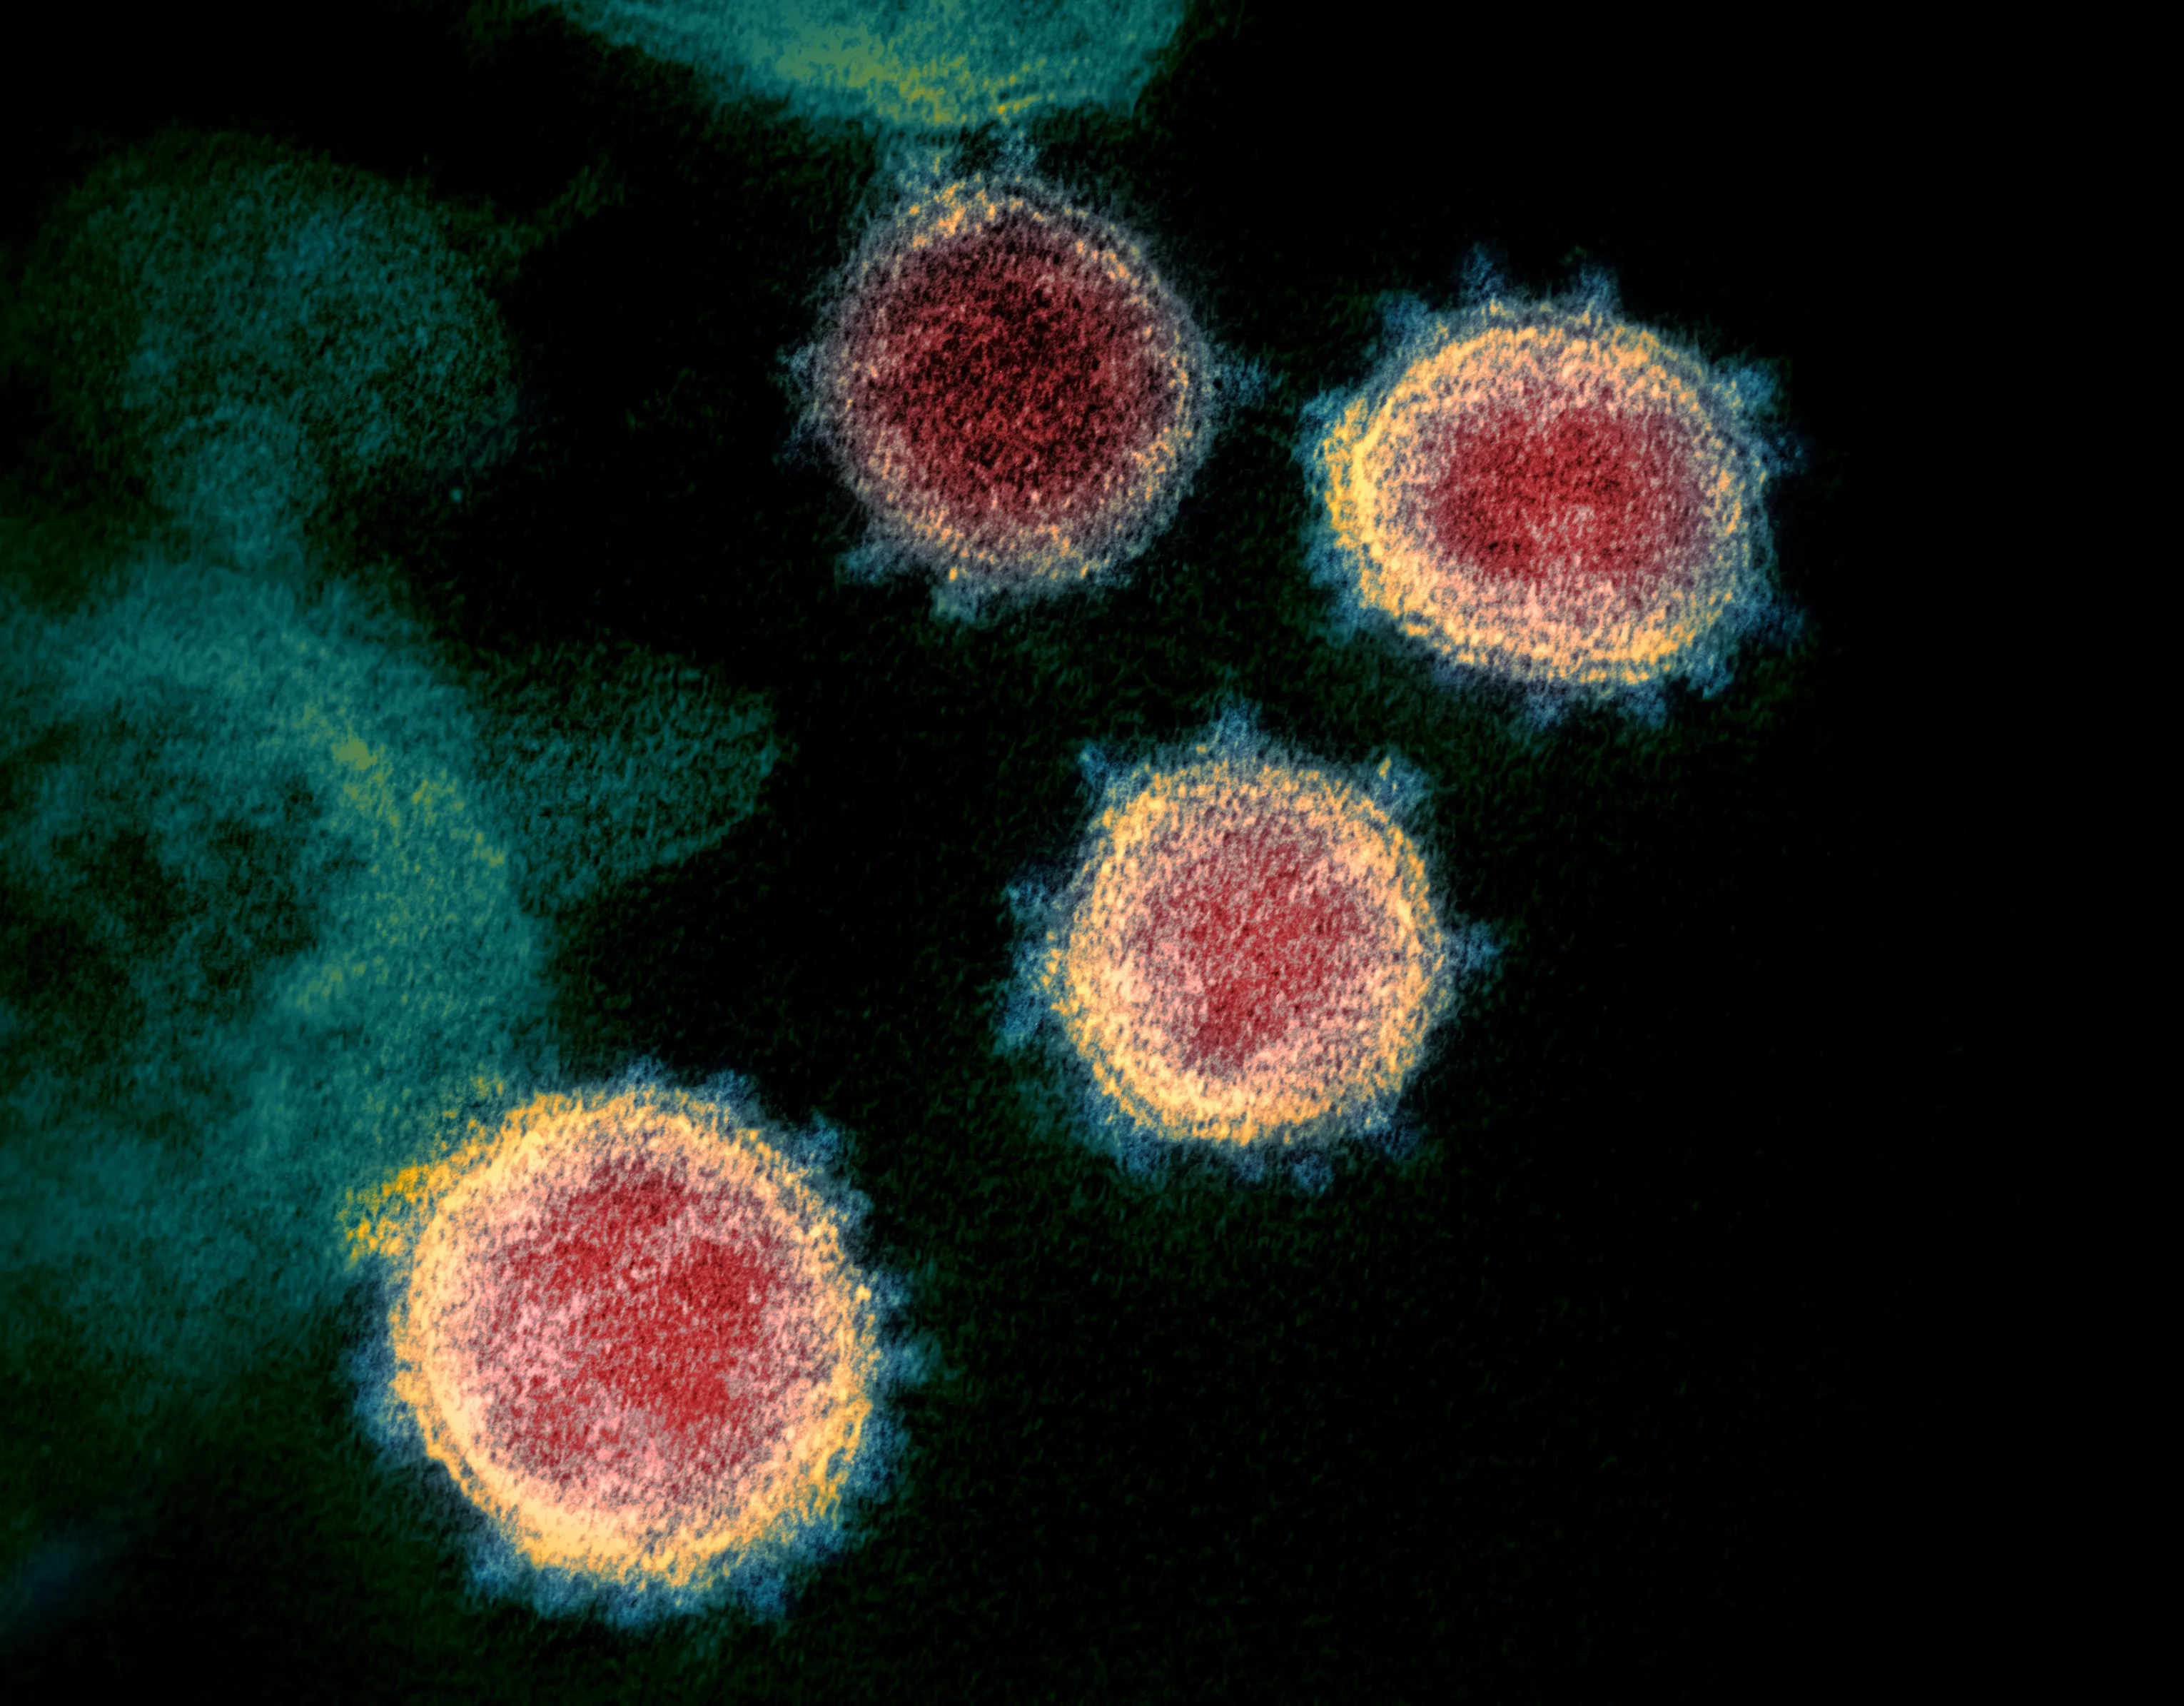

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreThe World Health Organization has supported a flexible approach to COVID-19 vaccination when supplies, safety considerations or local policy make a standard schedule difficult. Its Strategic Advisory Group of Experts on Immunization, known as SAGE, examined whether vaccines from different manufacturers could be used across doses. This approach is often called heterologous vaccination, interchangeability or a mix-and-match schedule. Learn more about Como Reencontrar Um Vizinho De Infância Usando O Cep.
The discussion became especially important during the early vaccine rollout, when countries faced uneven deliveries and changing advice about the AstraZeneca vaccine. Research suggested that receiving different vaccine platforms could produce a strong immune response, although the evidence, timing and recommended combinations varied. For Australians, the issue has practical importance because vaccine advice has changed with age, health status, variant circulation and the availability of pharmacies, GPs and state-run clinics.
WHO guidance did not mean that everyone should automatically swap vaccines at their next appointment. It meant that a different vaccine could be considered when the original product was unavailable, when a person had received a dose that was no longer preferred, or when national authorities judged the benefits to outweigh the uncertainties.
The phrase “mixing COVID-19 vaccines may improve immune response” refers to findings from studies of immune protection, especially when a viral-vector vaccine was followed by an mRNA vaccine. A first dose can prime the immune system, while a later dose made with a different technology may broaden the response. Researchers measured antibodies and T-cell activity, but laboratory results were only part of the decision.
WHO also stressed that recommendations depended on the products approved in each country. The Pfizer-BioNTech and Moderna vaccines use messenger RNA, while AstraZeneca uses a non-replicating viral vector. Novavax uses a protein-based approach. These differences allowed scientists to investigate whether a sequence involving separate platforms could offer useful protection without creating unacceptable safety risks.
Vaccination trains the immune system to recognise the coronavirus spike protein. A second dose using the same platform can reinforce that training. A different platform presents the target in another way, potentially stimulating several arms of immunity and reducing the chance that the immune response focuses too narrowly on the delivery technology.
Several studies found that an AstraZeneca first dose followed by an mRNA dose generated a substantial antibody response. Some research also indicated stronger cellular immunity than particular same-vaccine schedules. These results helped public-health agencies respond to supply shortages and concerns about rare blood-clotting events associated with AstraZeneca, particularly in younger adults.
A stronger laboratory response does not automatically equal complete protection from infection. Immune protection can decline over time, and new variants may partially evade antibodies. Vaccines have consistently been more valuable for reducing severe illness, hospitalisation and death than for guaranteeing that a person will never catch or transmit the virus. The meaning of “better immunity” therefore depends on the outcome being measured.
Australia’s rollout was shaped by the Therapeutic Goods Administration, the Australian Technical Advisory Group on Immunisation and state and territory health departments. ATAGI advice did not always mirror WHO wording because Australian authorities considered local supply, age-specific risks, domestic case numbers and the availability of Pfizer and Moderna. The preferred product for a particular person could therefore change as evidence and supply changed.
In Sydney and Melbourne, many people booked through mass vaccination hubs during periods of high demand, while residents in regional New South Wales, Victoria and Queensland often relied on local GPs or community pharmacies. A person who had received AstraZeneca at a hub might later be offered an mRNA booster by a GP, particularly when the national recommendation shifted. Australians commonly call vaccination a “jab”, but the casual language can hide important differences in dose timing and eligibility.
Access also varies for Aboriginal and Torres Strait Islander communities, people in remote areas and residents who face transport or appointment barriers. Clinics serving rural Western Australia, the Northern Territory or far north Queensland may manage different logistics from a suburban pharmacy in Brisbane. Cold-chain requirements, appointment availability and changing stock can all affect whether a person receives the same product or a different one.
People checking vaccine history should use an Australian Immunisation Register record, their GP or an official health department source rather than relying on social media posts. During earlier rollout periods, state booking systems and federal advice could appear inconsistent because they were addressing different populations and supply conditions. The practical question was usually which authorised vaccine was available and recommended for that individual at that time.
Mix-and-match vaccination was studied because safety had to be assessed alongside immune response. Expected reactions included a sore arm, fatigue, headache, muscle aches and fever for a short period. Some heterologous schedules produced more noticeable short-term symptoms, but these generally resolved quickly. Severe adverse events remained uncommon, although no medical intervention is risk-free.
A person’s age, pregnancy status, immune condition, previous infection and history of vaccine reactions can affect the appropriate schedule. People with significant immunocompromise may need additional doses or a different timing pattern because their first response may be weaker. Advice for a patient receiving cancer treatment, an organ transplant recipient or someone taking immune-suppressing medicine cannot be reduced to a general online rule.
There is also a difference between a primary course and a booster. A primary course establishes initial protection, while a booster refreshes immunity after protection has declined. Recommendations for boosters have shifted as population immunity increased and the virus evolved. Readers can review current discussion of booster guidance, but Australian residents should still confirm eligibility and product advice through an Australian clinician or health authority.
Urgent medical attention is appropriate for severe or unusual symptoms after vaccination, including chest pain, trouble breathing, fainting or signs of a serious allergic reaction. Reports of adverse events are investigated by regulators, and reporting a suspected reaction does not prove that vaccination caused it. This monitoring is central to decisions about changing products between doses.
The evidence supporting a mixed schedule came from clinical trials, observational studies and immune laboratory tests. Trials could compare antibody levels after different sequences, while real-world studies could examine infections, hospital admissions and safety in larger populations. Each design answered a different question, and the results were not always directly comparable.
Antibody concentration was an important marker, but it was not the only measure of protection. T cells may help limit severe disease even when antibody levels fall. Previous infection, age and the interval between doses can also influence results. A study showing a higher antibody level after one combination does not necessarily prove that it will prevent more infections in every community.
Variant changes complicated the picture. Early studies often focused on the original virus or earlier variants, while later waves involved Delta, Omicron and subvariants. A schedule that performed well against one variant might have a different effect against another. Updated vaccine formulations and booster timing therefore became as important as the question of whether the first and second doses matched.
Public confidence was another part of the evidence landscape. Clear explanations helped people understand why advice could change without meaning that earlier guidance had been reckless. In Australia, uncertainty was particularly visible when AstraZeneca recommendations changed by age and when vaccine supply improved. Explaining the reason for a change was more useful than presenting every update as a contradiction.
The central message was flexibility with safeguards. A mixed schedule could be a reasonable and effective option when recommended by health authorities, especially if the initial product was unavailable or a different vaccine was preferred for safety reasons. It was not a universal instruction to seek a particular brand or to combine doses independently.
Australians should keep a record of vaccine brand, dose date and vaccination setting. This can be useful when moving between a pharmacy in Adelaide, a GP in Perth or a travel clinic in Cairns. It also helps clinicians determine whether a person is due for a booster, belongs to a higher-risk group or needs extra advice before vaccination.
Health information can become mixed with unrelated online claims, particularly when people search for old friends, local contacts or community updates. Even a general neighbour search guide should not be treated as a source of medical information; vaccine decisions belong with trusted health services and official Australian guidance.
The following summary separates the main concepts that were often discussed together:
| Issue | What the evidence or guidance indicated | Practical meaning in Australia |
|---|---|---|
| Vaccine platform | mRNA, viral-vector and protein-based vaccines stimulate immunity through different technologies | Product choice depended on approval, supply, age and current recommendations |
| Mixed primary schedule | A different vaccine could be used for a later dose in specified circumstances | People should follow ATAGI, TGA, GP or vaccination-service advice |
| Immune response | Some combinations produced higher antibody or cellular responses | A laboratory improvement did not guarantee complete infection prevention |
| Short-term reactions | Fatigue, fever, headache and a sore arm were common expected effects | Most reactions were temporary, but serious symptoms required medical assessment |
| Booster doses | Protection can decline and recommendations change with variants and risk | Eligibility and timing should be checked against current Australian guidance |
| Higher-risk groups | Immunocompromised people may respond differently and need tailored schedules | Specialist or GP advice is important before changing a vaccination plan |
WHO’s position helped countries manage a rapidly changing pandemic, but national authorities remained responsible for translating evidence into local policy. In Australia, that translation involved regulators, immunisation experts, state services, pharmacies and primary-care clinics. The lasting lesson is that vaccine schedules can be adapted when evidence supports the change, provided safety monitoring and individual medical advice remain at the centre.