
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
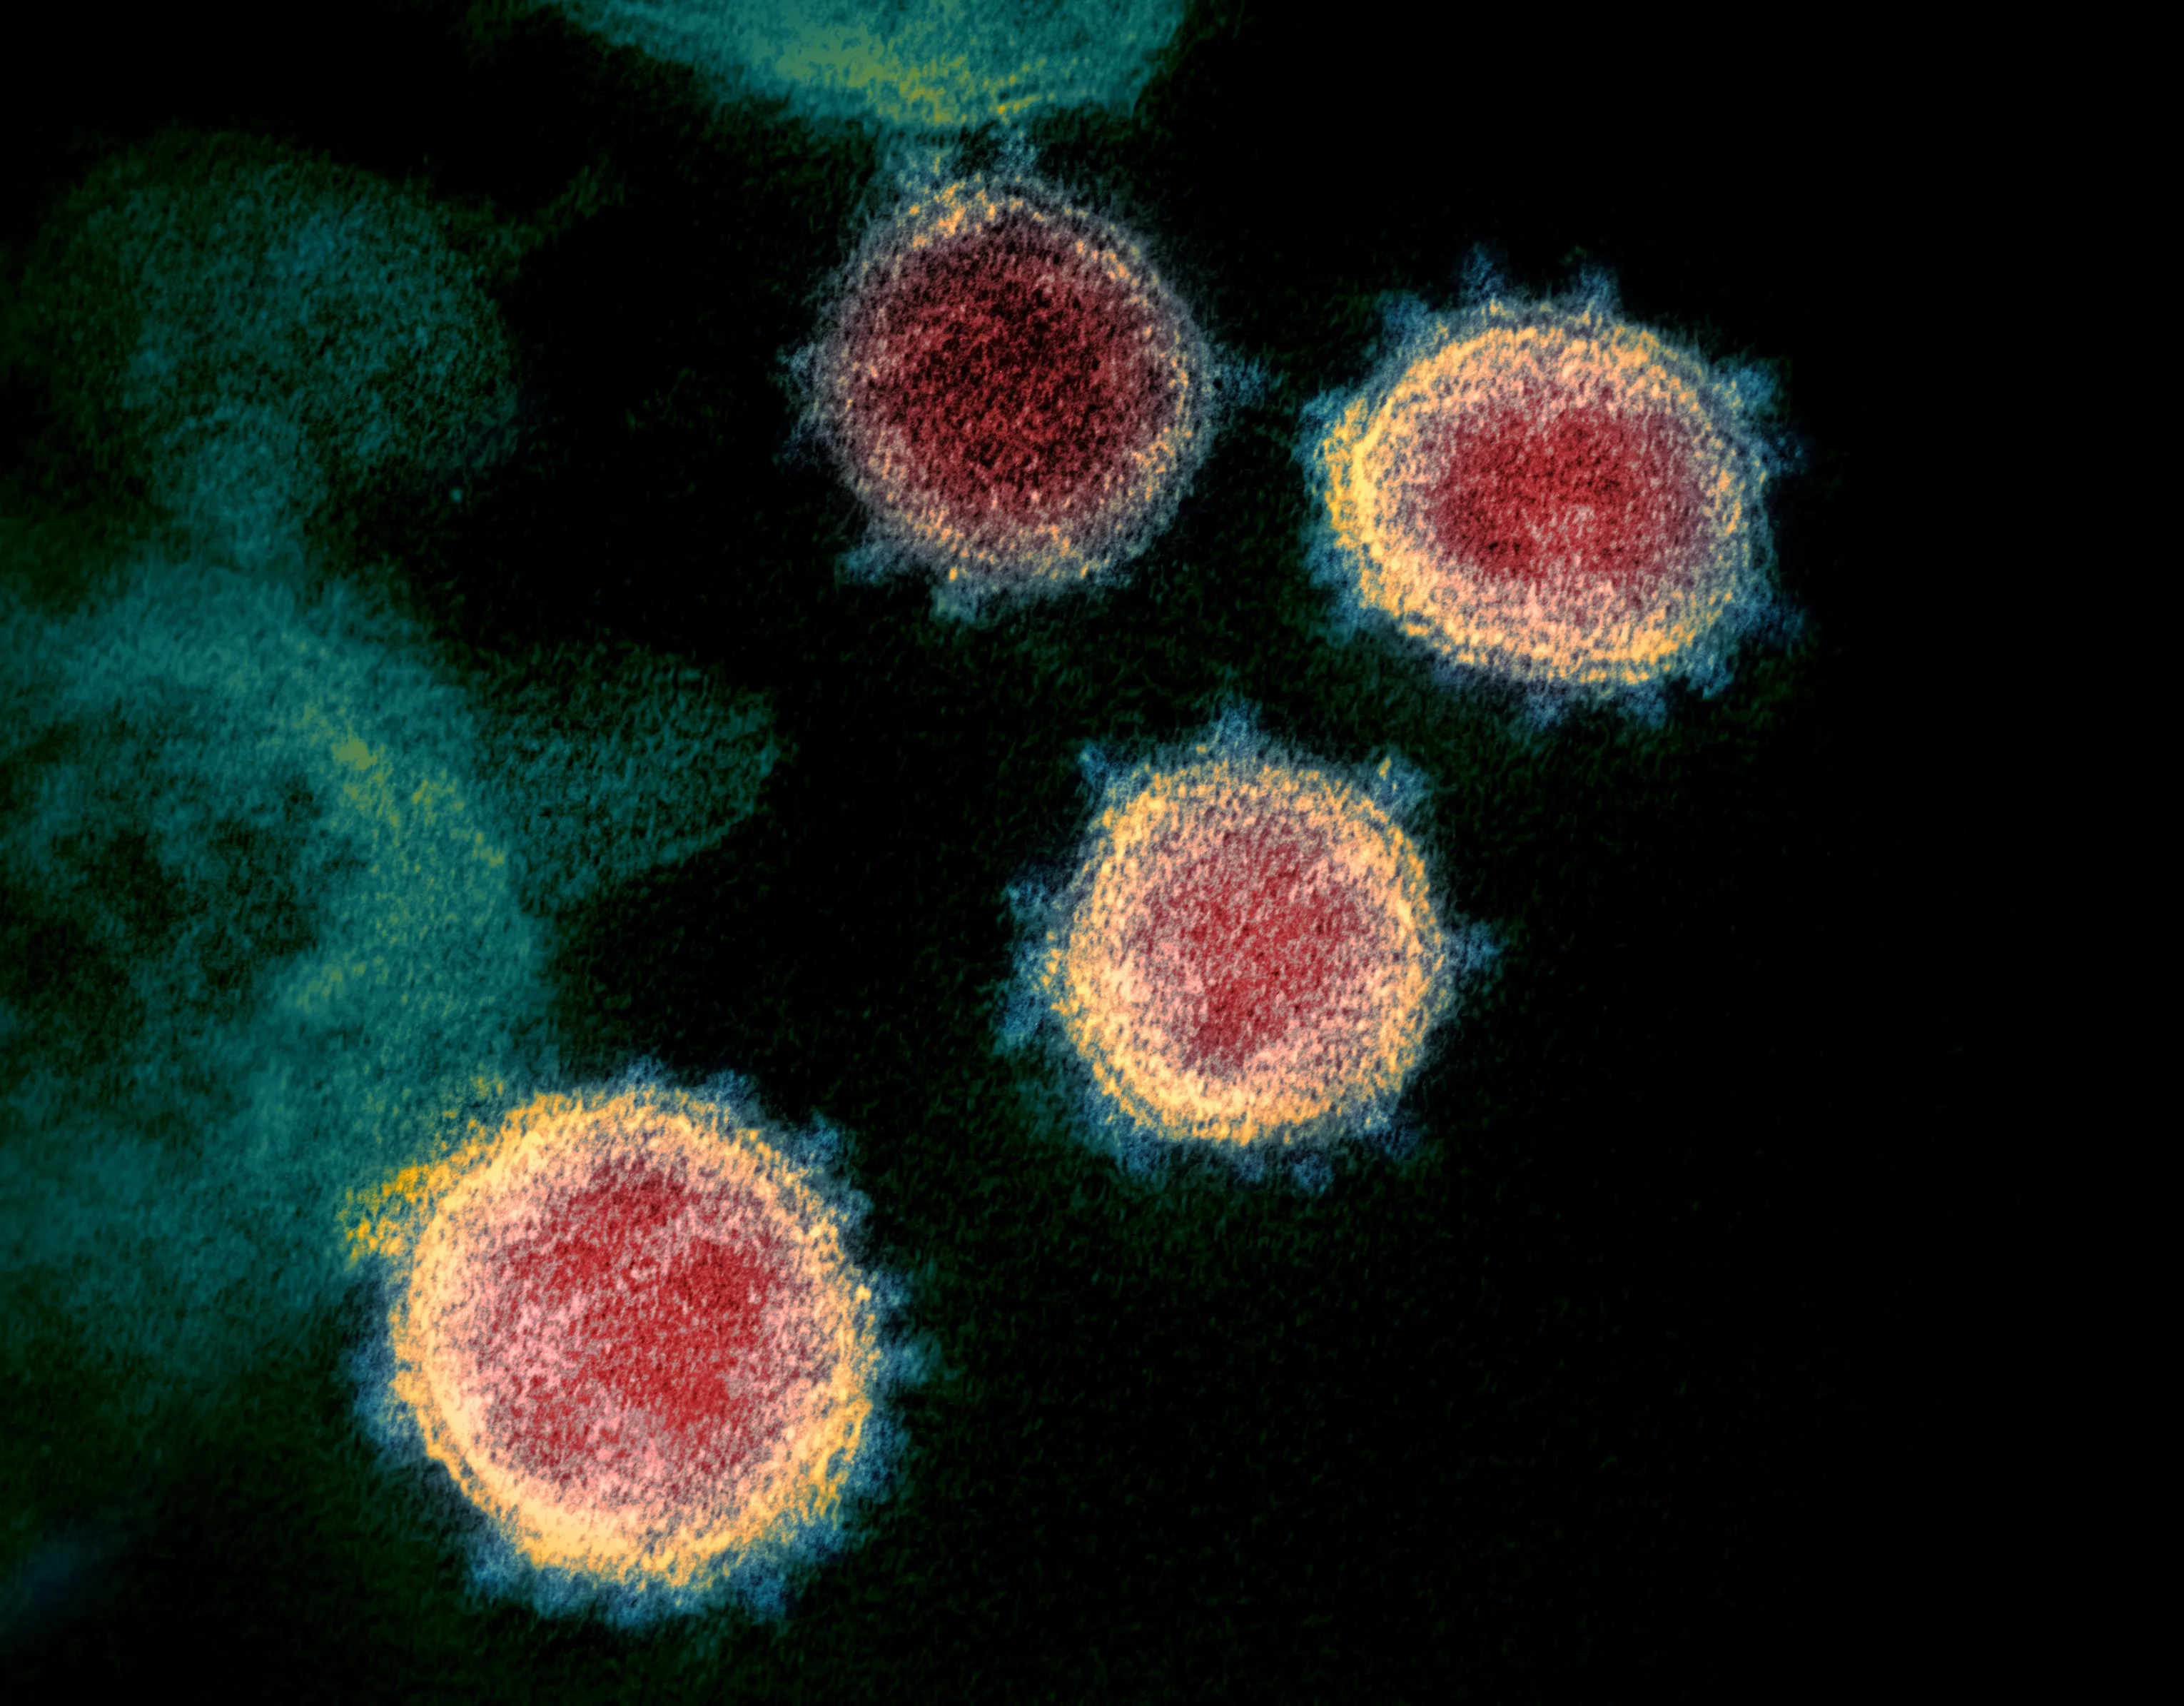

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreNew research suggests that COVID-19 may affect the auditory system in some people, with reported symptoms including tinnitus, muffled hearing, sound sensitivity, dizziness and, less commonly, measurable hearing loss. These problems have appeared during or after infection, although researchers are still working out how often they occur and whether the virus directly damages the inner ear.
For many patients, the change is temporary and improves as other post-viral symptoms settle. For others, ringing in the ears or difficulty understanding speech can continue for weeks or months. The experience can be especially disruptive in busy places such as Sydney railway stations, Melbourne cafés or open-plan offices, where background noise makes a mild hearing problem much more noticeable.
The evidence does not mean that every person with tinnitus has had COVID-19, or that infection will inevitably lead to permanent deafness. Age, noise exposure, medication, stress, circulation problems and other infections can contribute to hearing symptoms. A careful assessment by a GP, audiologist or ear, nose and throat specialist remains important.
Studies published since the early stages of the pandemic have reported a possible link between SARS-CoV-2 infection and auditory symptoms. Reviews of available evidence have included cases of tinnitus, hearing impairment, vertigo and balance disturbance. Some patients developed symptoms during the acute illness, while others noticed them during recovery or as part of longer-lasting post-COVID conditions.
Researchers have proposed several explanations. The infection may trigger inflammation around the auditory nerve or the small blood vessels that supply the cochlea, the inner-ear structure responsible for hearing. Fever, immune activity and changes in blood circulation may also affect how sound signals are processed. A severe illness can place considerable stress on the body, potentially revealing an existing hearing problem that had previously gone unnoticed.
The quality of the evidence varies. Many early reports were based on small groups, questionnaires or individual case studies rather than large controlled trials. Tinnitus is also difficult to measure objectively because it is a personal perception of sound. A person may describe ringing, buzzing, hissing, clicking or a low electrical hum, while a standard hearing test appears normal.
This is why scientists generally describe an association rather than proof that COVID-19 directly causes every reported case. Larger population studies and longer follow-up are needed to separate the effects of infection from ageing, anxiety, loud noise, medicines and the social disruption of the pandemic.
COVID-related auditory symptoms can vary widely. Some people report a blocked or underwater sensation, reduced clarity, or difficulty following a conversation when several people are speaking. Others notice a constant or intermittent ringing that becomes stronger at night, during periods of stress, or after exposure to loud music.
Tinnitus can occur with normal hearing, but it may also accompany high-frequency hearing loss. A person may still hear speech yet struggle with consonants such as “s”, “f” and “th”. Sounds can seem distorted, and television volume may gradually rise without the person realising it. Ear pressure, dizziness and a reduced tolerance for everyday sounds are also reported by some patients.
A sudden drop in hearing is different from ordinary ear blockage. Sudden sensorineural hearing loss can develop over hours or a few days, often in one ear, sometimes alongside tinnitus or dizziness. It requires urgent medical assessment because treatment may be more effective when started promptly. Waiting to see whether the ear clears on its own can delay care.
People who notice persistent symptoms should record when they began, whether one or both ears are affected, and whether the change followed infection, medication or loud noise. A GP can check for wax, middle-ear fluid, infection and other common causes before arranging a formal audiogram. A hearing test can identify frequencies that are difficult to detect even when everyday hearing seems broadly normal.
In Australia, a practical first step is usually a visit to a general practitioner, with Medicare helping cover eligible medical consultations according to the doctor’s billing arrangements. A GP may refer a patient to an audiologist or an ear, nose and throat specialist. Public wait times and private fees can vary between metropolitan areas and regional communities, so people may need to ask about costs before booking a test.
Pharmacists in local communities, including large retail chains and independent chemists, can offer general guidance about medicines and ear-care products, but persistent tinnitus should not be self-treated with unproven supplements. Ear candles and inserting cotton buds can cause injury or push wax deeper into the canal. Consumers should check that any medicine or device is approved for use in Australia and discuss possible side effects with a health professional.
The Therapeutic Goods Administration continues to monitor medicines, medical devices and vaccine safety. Current evidence does not support stopping prescribed treatment or avoiding vaccination solely because of fear of tinnitus or hearing loss. A person who develops a new symptom after any medical treatment should report it to a clinician, who can assess timing, alternative explanations and the need for further investigation.
Digital health records and online information can be useful, but privacy matters. During the pandemic, public discussion of health surveillance included proposals that smartphone data report could help track movement patterns. That debate also highlighted the importance of understanding how sensitive health information is collected, stored and shared. Hearing symptoms should be discussed through secure clinical services rather than public posts that reveal personal details.
For Australians in Brisbane, Perth or smaller regional towns, access to audiology may require travel or a longer appointment wait. Telehealth can help with follow-up discussions, although it cannot replace an in-person ear examination or hearing test when symptoms are new, one-sided or rapidly worsening.
Tinnitus is common and has many possible triggers. Long-term exposure to machinery, headphones, concerts, sporting events and construction noise can injure delicate hair cells in the cochlea. Australians working around mining equipment, agriculture machinery or busy transport networks may face substantial occupational noise and should use correctly fitted hearing protection.
Earwax build-up, allergies, sinus congestion and middle-ear infections can create pressure or muffled hearing without involving the inner ear. Jaw clenching and temporomandibular joint problems can intensify ringing, particularly during stressful periods. Poor sleep and anxiety can also make tinnitus feel louder, even when the underlying sound has not changed.
Medicines are another consideration. Some drugs can affect hearing or balance, especially at higher doses or when combined with kidney problems. People should never stop an important prescription without medical advice, but they should provide a complete list of medicines, vitamins and recreational substances during an assessment.
COVID-19 may be one factor among several. A patient who had the virus before noticing tinnitus may reasonably suspect a connection, yet timing alone cannot establish causation. Doctors may consider the infection history alongside age, previous hearing tests, noise exposure, ear symptoms, cardiovascular health and any history of migraine or neurological disease.
A clinical review from a specialist medical publication can provide useful background, but it should complement rather than replace personal medical care; readers may find further discussion in the Apollo Medical Journal. Reliable health reporting should distinguish preliminary findings from established clinical guidance and should explain the limits of small studies.
There is no single treatment that removes all post-COVID tinnitus or hearing loss. Care depends on the cause and the results of examination. Wax removal, treatment of an ear infection, hearing rehabilitation or management of another medical condition may improve symptoms. When tinnitus persists, sound therapy, counselling and cognitive behavioural approaches can reduce distress even if the perceived noise does not disappear completely.
Hearing aids may help people who have measurable hearing loss, and modern devices can be adjusted to support speech in noisy settings. Australia’s hearing services market includes public programs, private audiology clinics and different levels of device support, so eligibility and out-of-pocket costs should be checked carefully. Some adults may qualify for assistance through government schemes, while others may need private assessment and purchase.
People should seek urgent care for sudden hearing loss, severe vertigo, facial weakness, new neurological symptoms, intense ear pain or discharge. A hearing change in one ear, pulsatile tinnitus that matches the heartbeat, or symptoms after a head injury also deserves prompt medical review.
Useful steps include:
| Hearing symptom | Possible significance | Appropriate next step |
|---|---|---|
| Brief ringing after loud noise | Often linked to temporary auditory stress | Rest the ears and reduce further noise exposure |
| Tinnitus lasting days or weeks | May reflect infection, hearing loss, medication or another cause | Book a GP or audiology assessment |
| Muffled hearing with congestion or ear pressure | Could involve wax, fluid or middle-ear inflammation | Arrange an ear examination |
| Sudden hearing loss in one ear | Potential medical emergency | Seek urgent medical care |
| Pulsing noise in time with the heartbeat | May need investigation of blood-flow or vascular causes | Contact a clinician promptly |
The central message is measured rather than alarmist: COVID-19 may be associated with hearing loss and tinnitus in some patients, but the strength of that relationship is still being investigated. Early attention gives clinicians a better chance to identify treatable causes, protect remaining hearing and provide support when symptoms continue during recovery.