
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
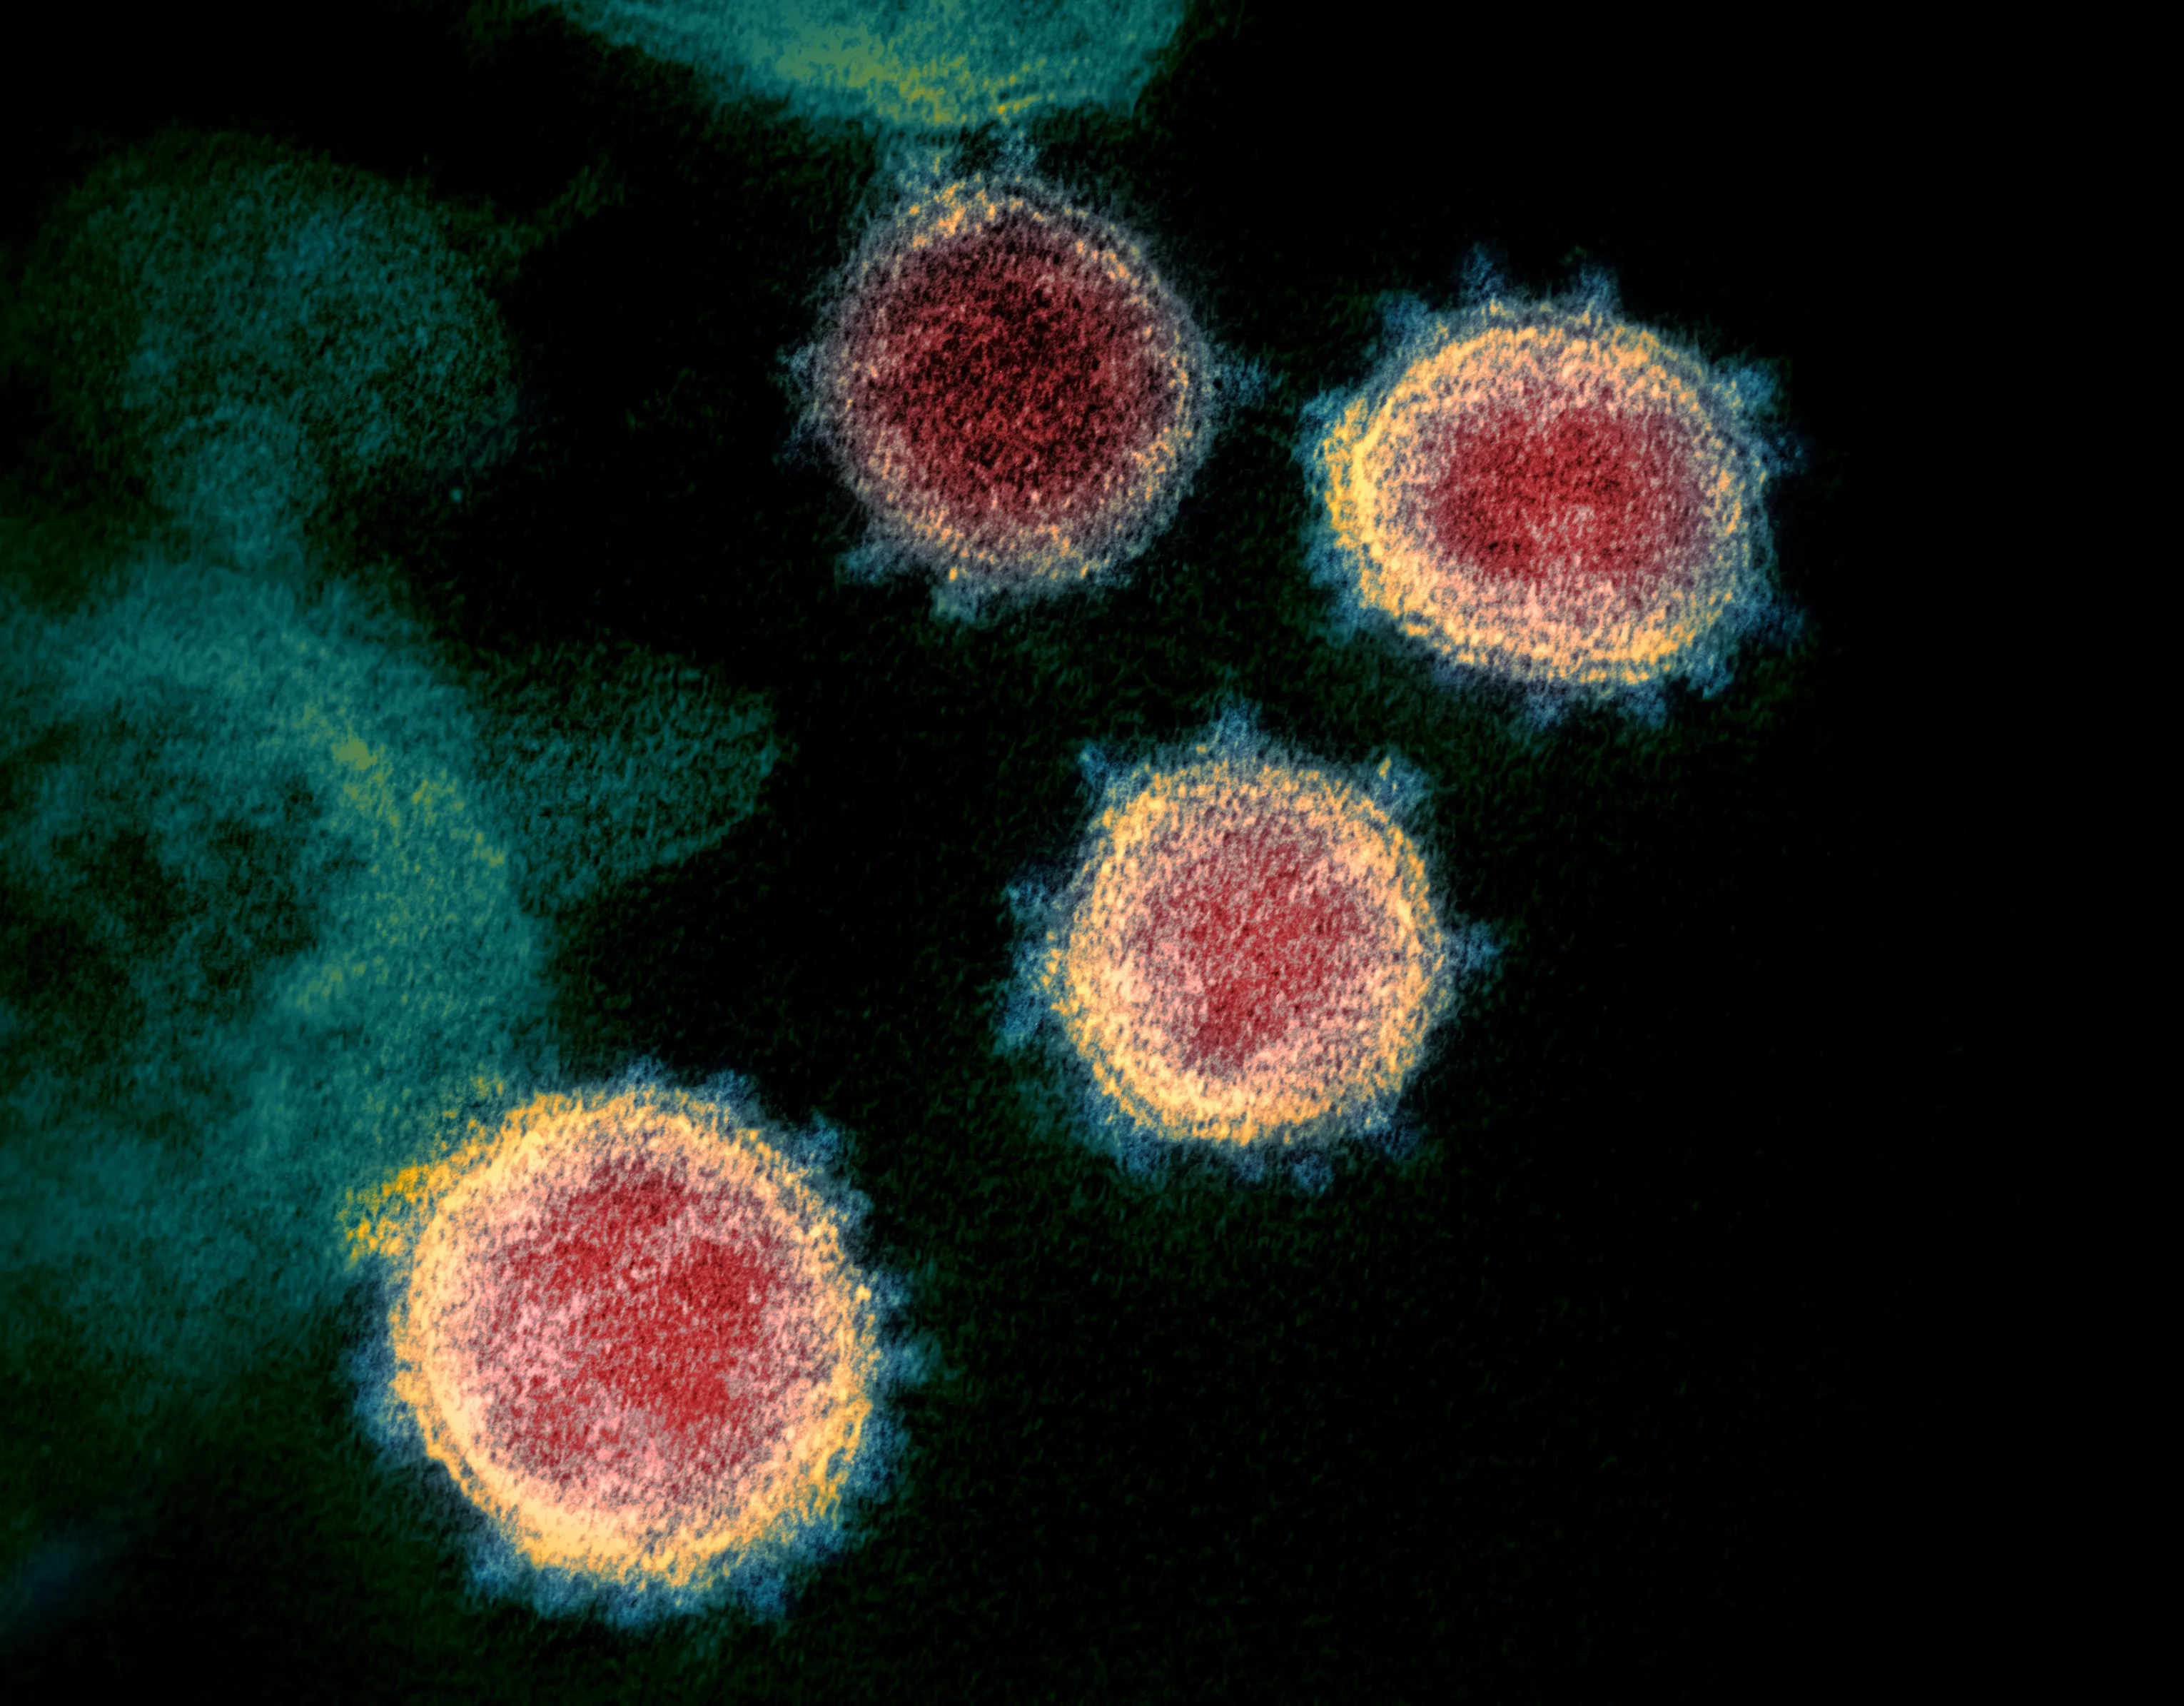

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreLong COVID clinics overwhelmed by patient demand across the United States are struggling to assess and treat people whose symptoms persist long after an initial SARS-CoV-2 infection. Reports from academic hospitals and community practices describe appointment backlogs, exhausted specialist teams and growing numbers of referrals from primary care. The surge reflects a broad mix of illnesses, with many patients requiring a combination of medical treatment, rehabilitation and social support.
Patients commonly describe persistent exhaustion, unrefreshing sleep, headaches, brain fog, shortness of breath, dizziness and changes in smell or taste. Post-exertional malaise is another defining concern: physical or mental activity can trigger a delayed worsening of symptoms, sometimes days later. That pattern can make standard exercise prescriptions or intensive rehabilitation programmes unsuitable for some people.
For Australian readers, the experiences reported in major US cities are familiar in several respects. Long-COVID assessment services have developed within public health systems in Melbourne, Sydney and Brisbane, although access depends on local referral rules and available capacity. The condition has also reshaped how many people use telehealth, manage work and plan treatment around unpredictable periods of reduced capacity.
The two countries differ in how care is funded and coordinated. In the US, insurance coverage, employer benefits and state programmes create fragmented pathways. Australia relies more heavily on Medicare, general practitioners and public hospitals, but public waiting lists and shortages of specialist staff create similar pressures. Understanding those differences helps explain why the same collection of symptoms can produce very different experiences for patients.
Demand has become difficult for clinics to absorb. National surveys in the US have produced estimates of long COVID affecting tens of millions of adults, although the figures vary with survey wording and the definition of a case. Clinics receive referrals for symptoms lasting months, recurrent infections that do not fit previous expectations and health problems that complicate returning to work.
The referral bottleneck often begins before a specialist appointment. Some patients need a cardiologist for suspected post-viral heart issues, a neurologist for cognitive symptoms or a respiratory specialist for persistent lung complaints. Others require several assessments because no single test can confirm long COVID. Primary-care teams are trying to determine which symptoms need urgent investigation and which can be managed while waiting for a specialist clinic.
Many clinics have expanded telephone appointments and multidisciplinary staff, but these measures can take time to establish. A new patient may require a medical review, a functional assessment, a review of medications and a discussion of work, exercise and daily activities. Short consultations designed around a single symptom may fail to capture the fluctuating and overlapping nature of the condition.
Patients can send requests for clarification about source dates, regional terminology or supporting material through contact the newsroom, while urgent medical concerns should be directed to a treating service.
Long COVID is not confined to respiratory symptoms. Autonomic dysfunction can cause a rapid heartbeat, lightheadedness or a worsening of existing conditions when standing. Changes in temperature regulation, gastrointestinal distress and joint pain are also reported. Cognitive symptoms may include difficulty concentrating, finding words, retaining information or completing tasks that were previously routine.
These symptoms can affect employment, education, relationships and household duties. A person may appear well during a short medical appointment yet need substantial recovery afterward. Fluctuating periods of improvement can make the condition hard for colleagues, employers and even family members to understand. The resulting frustration is adding pressure to an already strained clinical relationship.
Severe post-exertional malaise can remain hidden when patients are focused on meeting medical appointments. Travelling to a clinic, walking through a hospital and waiting in a chair may consume much of a patient’s available energy. Consequently, a referral that appears routine on paper may produce a major physical cost for someone with post-viral illness.
Clinics are responding with longer assessments, symptom diaries and triage systems that account for function as well as test results. The aim is not simply to label every prolonged symptom as long COVID, but to identify overlapping conditions, investigate appropriate areas and create a plan that reduces avoidable harm.
Care pathways differ between the US and Australia, but both face shortages, waiting lists and unequal access. The comparison also shows why international statistics should be interpreted carefully: state policies, insurance arrangements and hospital funding can produce substantial variation within each country.
| Factor | United States | Australia |
|---|---|---|
| Typical access route | Referrals may come from primary care, while some clinics accept direct appointments and private payment | Public specialist care commonly requires a GP referral, with private pathways also available |
| Main funding arrangements | Employer health plans, Medicare, Medicaid, state programmes and self-payment | Medicare, public hospitals, private insurance and patient contributions |
| Common access problem | Insurance authorisation, high copayments and limited networks can delay specialist review | Long public outpatient lists, uneven GP capacity and shortages of allied-health staff |
| Cost exposure | Patients may face substantial out-of-pocket costs depending on coverage and employment | Medicare subsidises many services, although some allied-health care and appointments can still attract gaps |
| Workplace support | Paid leave and disability benefits vary by employer, state and contract | The Fair Work Act provides minimum paid sick-leave entitlements for many employees |
| Longer-term support | Private disability insurance, Social Security disability programmes and vocational rehabilitation | NDIS support for eligible people, employer arrangements and other disability services |
In the US, the absence of a universal long-COVID pathway can force patients to navigate several agencies before receiving coordinated care. Employers with generous health plans may provide easier access, while temporary or hourly workers can face the greatest barriers. Even within a single city, waiting times and treatment options can differ sharply according to insurance status.
Australia’s system offers a more consistent public entry point through Medicare and general practice, but it is not a guarantee of prompt specialist care. A GP can provide a referral, document functional limitations and arrange a management plan for Medicare-subsidised allied-health services. The local market of private physios, occupational therapists and psychologists can fill some gaps, though patients may still face out-of-pocket charges and variable waiting times.
Legislation shapes part of the recovery process as well as access to treatment. Under the Fair Work Act 1999, most full-time and part-time employees have at least 10 days of paid sick leave a year, subject to the National Employment Standards and applicable agreements. Casual employment generally does not carry the same entitlement. People whose symptoms cause substantial ongoing disability may also qualify for support through the National Disability Insurance Scheme.
There is no single treatment that resolves long COVID for everyone. Clinicians generally combine symptom management with pacing, sleep support, nutritional advice, rehabilitation and treatment of conditions that may coexist with post-viral illness. The starting point is often a detailed account of what the patient can tolerate, what triggers deterioration and which activities are currently essential.
Pacing means balancing activity and recovery without repeatedly exceeding a person’s energy limit. Fixed increases in exercise can be harmful when a major symptom is post-exertional malaise, so programmes must adapt when symptoms worsen. Some patients benefit from input from occupational therapists or physiotherapists who understand post-viral illness, while others need additional support for pain, anxiety, sleep disturbance or orthostatic intolerance.
Claims about devices can be particularly confusing. Foot supports may help people with a separate mechanical or sporting problem, but orthoses should not be presented as a cure for long COVID or as a way to push through post-exertional symptoms. General background on sports orthoses information can help patients understand their possible use, although suitability depends on an individual assessment.
Australia’s private allied-health market has responded by developing post-viral fatigue programmes in cities such as Melbourne and Sydney. Access through a GP management plan may provide rebates for eligible services, but availability, cost and practitioner expertise remain uneven. Telehealth has become a familiar option because it reduces travel and allows patients to remain in a stable environment during assessments.
The growing workload is producing consequences beyond consultation rooms. Delayed treatment can leave physical symptoms poorly understood, medication side effects unaddressed and rehabilitation goals out of date. Administrative staff are also managing referral volumes while clinicians balance long COVID with influenza, respiratory viruses and other routine conditions.
Access is least reliable for people with limited paid leave, limited savings or no nearby specialist service. This pattern has appeared in US cities with large populations of essential workers and in rural communities where the nearest long-COVID programme may be hundreds of kilometres away. Telehealth can bridge some distance, but it still depends on reliable internet, suitable devices and clinicians familiar with complex post-viral symptoms.
Australian patients face similar barriers within a different system. Crowded trains and trams, long hospital trips and the physical effort of attending multiple appointments can worsen fatigue. Masking remains common in healthcare settings and on public transport, while rapid antigen tests are familiar to many households from the pandemic period. These habits can reduce immediate infection risk, yet they do not prevent every case or resolve symptoms that continue after recovery.
For people relying on the National Disability Insurance Scheme, evidence about functional impact is important when requesting support. However, proving fluctuating limitations across medical, cognitive and social domains can be time-consuming. Employers and insurers can also question capacity inconsistently, especially when symptoms vary from week to week.
The pressure is likely to persist until clinics gain stable staffing, coordinated funding and faster routes to multidisciplinary assessment. Until then, the United States faces a growing gap between the number of people seeking help and the clinical capacity available to provide it, while Australia continues to see similar demand through its public and private pathways.