
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
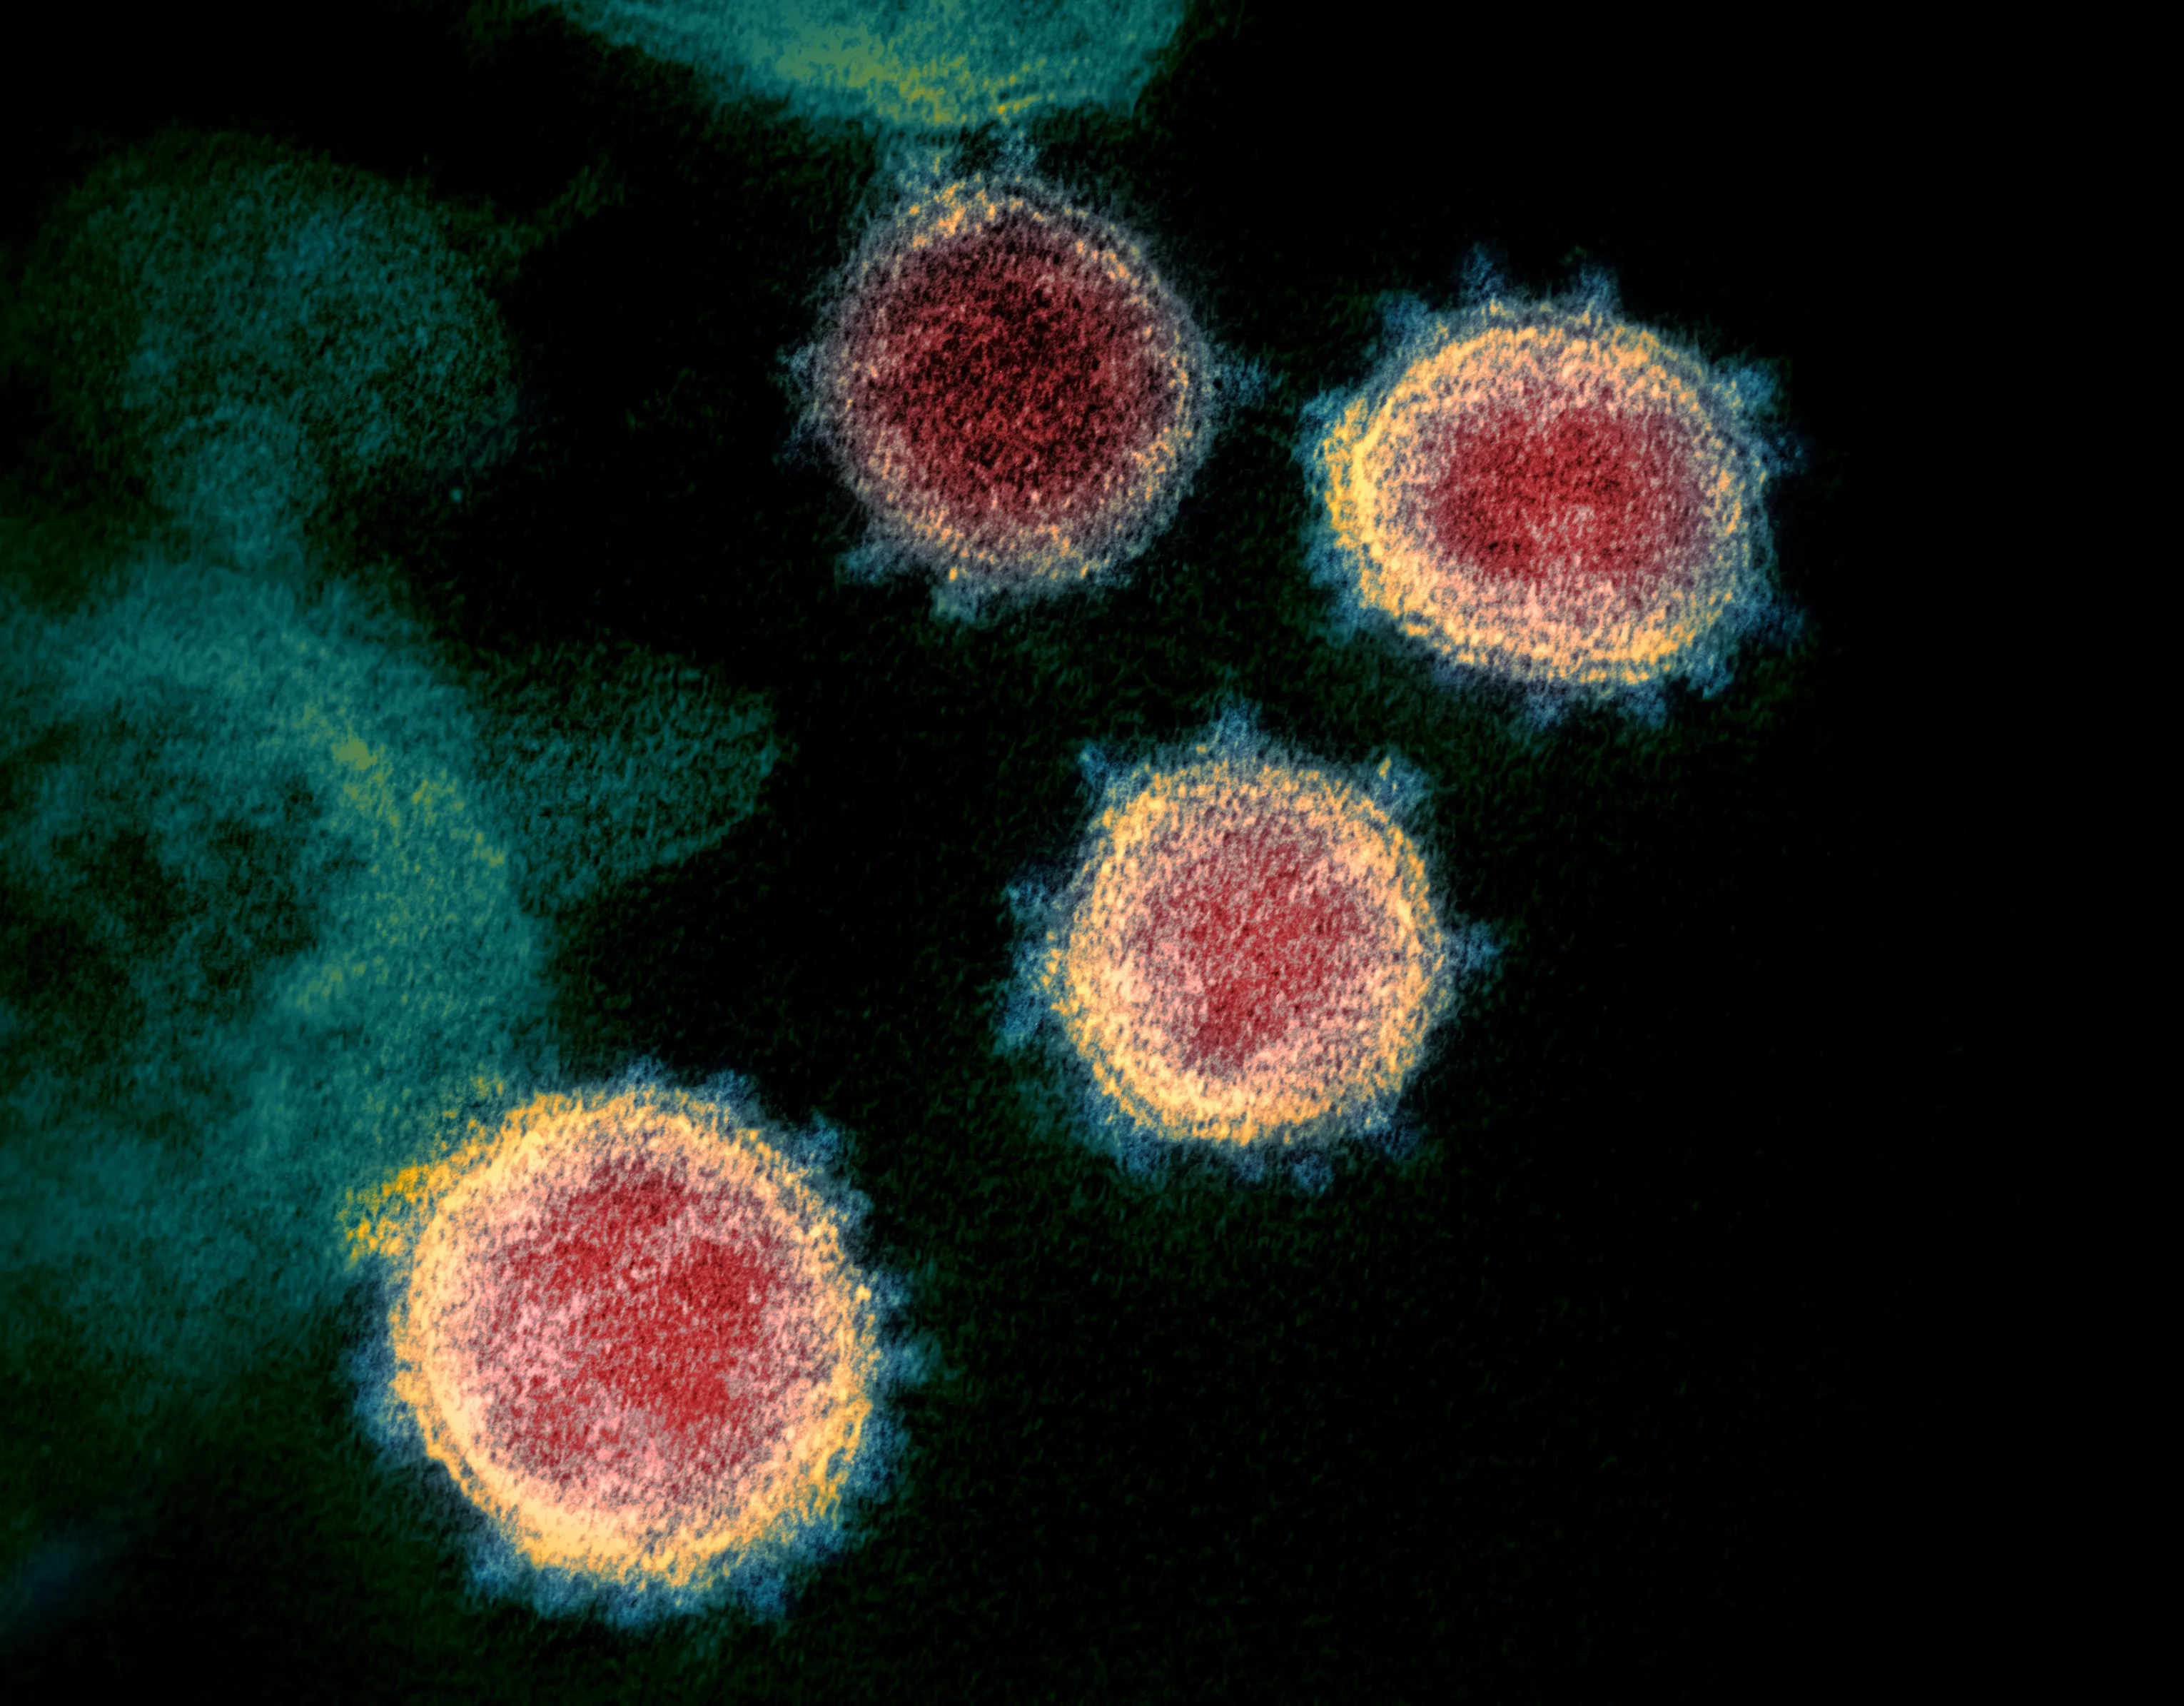

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreThe US COVID-19 death toll has exceeded 500,000 as the nation passes a grim milestone. Official reports place the pandemic’s cumulative fatalities above half a million, with daily deaths briefly returning to the levels recorded during the previous winter surge. The figure covers confirmed and probable deaths attributed to COVID-19, including losses in hospitals, nursing homes and private homes, but it does not capture every death indirectly linked to disrupted care, economic stress or delayed treatment. Learn more about Plan De Emergencia Ante Explosiones Por Polvo Combustible En Silos.
The milestone arrived after repeated surges, shifting public-health guidance and an uneven vaccine rollout. It also exposed profound differences between countries: population size, age structure, reporting practices and border policies all shaped the final count. Australia experienced outbreaks of its own, yet its local response and domestic market were far removed from the scale seen across much of the United States.
The threshold was crossed in March 2021, roughly a year after the WHO declared COVID-19 a pandemic. Official totals were assembled from state and local reports, and the national death rate was about 151 for every 100,000 residents. Provisional life-expectancy figures also showed a decline of about a year in 2020, one of the sharpest annual reductions in the modern United States.
| Measure | United States | Australia in early 2021 |
|---|---|---|
| Reported COVID-19 deaths | More than 500,000 | Fewer than 1,000 |
| Population | About 331 million | About 25.5 million |
| Deaths per 100,000 people | Roughly 150 | Under 4 |
| Main outbreak pattern | Repeated urban and Sun Belt surges | Concentrated outbreaks in Sydney and Melbourne |
| Core controls | State-led restrictions, testing and vaccine campaigns | Border caps, hotel quarantine, tracing and state health orders |
These comparisons need caution because jurisdictions counted probable deaths and published data on different schedules. Even so, the gap per capita was immense. In Australia, the early national toll remained below one thousand deaths while Victoria was absorbing outbreaks and New South Wales was managing smaller clusters. In America, several states had already recorded tens of thousands of deaths, and the national total continued climbing long after the first emergency response ended.
The human burden was concentrated among older adults, people with chronic illnesses and residents of long-term care facilities. Doctors, nurses, nursing-home staff, paramedics and cleaners also faced infection, burnout and bereavement. Many families experienced grief while hospitals restricted visitors, turning private loss into a long public emergency.
The count also concealed quieter harms, including postponed cancer screening, delayed organ transplants and disrupted childhood vaccinations. Health workers experienced exhaustion and moral injury, while communities struggled with isolation, financial insecurity and fear of infection. Each represented a secondary cost of concentrating healthcare resources on COVID-19.
The virus moved through workplaces, churches, restaurants, schools, airports and family gatherings before testing could keep pace. Asymptomatic transmission made infection harder to detect, while shortages of protective equipment and inconsistent guidance exhausted many health systems. Global demand for gloves, masks, oxygen and medicines placed further pressure on supply chains as elective procedures were postponed. The first winter brought crowded emergency departments, ambulance backlogs and mass outbreaks among nursing-home residents, revealing how quickly routine care could be displaced.
A national public-health strategy developed through federal guidance, state orders and local health departments. Restrictions changed repeatedly as scientific understanding evolved, and political division made mask rules, school closures and vaccine access contentious. Misinformation about airborne spread and vaccine safety deepened distrust in some communities. Essential workers often had to choose between crowded workplaces and unpaid illness, while crowded housing made isolation far harder.
The burden also fell unevenly. Black and Hispanic communities experienced higher mortality after adjusting for age, and rural hospitals often had fewer intensive-care beds and specialists. Native American communities and some urban neighbourhoods faced longstanding shortages in medical infrastructure and public services. At the same moment the United States faced its winter wave, India was overwhelmed by an oxygen shortage and parts of Latin America reported severe hospital pressure. The pandemic demonstrated that a disease crossing borders can expose weaknesses in health systems, supply chains and public trust simultaneously.
Australia’s first major outbreak centred on Melbourne, where a second wave in 2020 led to a long lockdown, strict stay-at-home orders and criticism of quarantine arrangements. Later clusters in Sydney tested NSW contact tracing and QR-code check-ins, while aged-care outbreaks in Victoria again triggered restrictions and scrutiny of infection control. Melbourne testing queues and vaccination hubs became familiar sights, and many residents shifted from ordinary routines to scheduled tests, daily health checks and regular updates about exposure sites.
Border policy created a very different national rhythm. Returning travellers encountered international flight caps, medical testing and hotel quarantine, while Western Australia maintained some of the country’s strictest interstate arrival rules. Customs and biosecurity procedures remained part of every arrival, while health forms and quarantine bookings added new layers. The stringent border regime bought time, but it also separated families, disrupted tourism and placed heavy demands on quarantine workers and hotel operators.
Public-health agencies relied on the Australian Department of Health and state health teams, while the Therapeutic Goods Administration assessed vaccines and treatments before use. Aged-care facilities faced visitor limits, staff screening and outbreak plans. State-run vaccination hubs and Medicare-funded general practices supported the rollout, while public messaging focused on staying home when unwell, using ventilation where possible and acting on local health advice.
The disruption was visible in Australian shops. Panic buying in March 2020 left Woolworths and Coles shelves bare in some locations, while later shipping delays caused shortages of staples and hygiene products. JobKeeper and income support softened the shock to household finances, but the ASX suffered sharp swings and the Australian dollar moved as markets repriced the risk of a prolonged shutdown. Some households also researched digital assets while conventional savings remained idle; the site’s crypto buying guide outlines access, fees and volatility for Australians weighing that market.
Vaccination changed the trajectory of the disease, though the protection arrived only after the milestone. Pfizer-BioNTech and Moderna jabs began in the United States in December 2020, initially prioritising older adults in hospitals and nursing homes. Australia began its rollout in February 2021 after regulatory review, using Pfizer-BioNTech and AstraZeneca. Delays, uncertain supply and uneven take-up left many communities exposed while doses were still being administered.
Later variants altered the balance between infection and death. Delta drove large outbreaks through the middle of 2021, while Omicron’s arrival late that year brought much higher transmission and allowed more vaccinated people to become infected. Vaccination, prior infection and improved treatment sharply reduced the chance of critical illness for many, yet older people and people with weakened immune systems remained at elevated risk. Health authorities consequently combined boosters, ventilation, antiviral medicine and surveillance as restrictions eased. Across the world, unequal access to doses meant many countries in Africa, South Asia and Latin America faced another year with limited protection.
Recovery has been uneven beyond the intensive-care unit. “Long COVID” has affected millions with persistent fatigue, breathing problems and cognitive symptoms, while anxiety, depression and social isolation added to the burden of prolonged disruption. The pandemic also widened existing gaps in education, income and access to care. In Australia, emergency leave rules, mental-health services and support for casual workers were repeatedly adjusted as states moved between restrictions and reopening.
The milestone showed how quickly a temporary health crisis can become a long economic and social emergency. Stronger surveillance, faster data sharing, protected sick leave and reliable supplies of protective equipment would allow authorities to act before hospitals fill. Clear national standards can coexist with state-level delivery, but residents need consistent messages about vaccination, testing and treatment, especially when the virus is circulating widely. After-action reviews should also test whether alerts move quickly from laboratories to clinicians, aged-care facilities, schools and the public.
Preparedness also extends beyond hospitals. Hazard assessment, clear lines of command and rehearsed communication are common features of public-safety planning, as illustrated by industrial emergency planning for combustible dust in silos. A pandemic and an industrial fire have different causes, yet both punish organisations that wait for perfect information or confuse a plan on paper with a workable response.
No aggregate number can describe each life lost, but the half-million mark has become a demand for better institutions rather than a fleeting headline. The World Health Organization and national agencies must retain laboratories, genomic surveillance and regional partnerships capable of detecting a new pathogen early. Within the United States, the same lesson applies to hospitals, aged-care operators, businesses and local governments: preparedness works when responsibilities are shared, resources are maintained and decisions remain grounded in transparent evidence.