
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
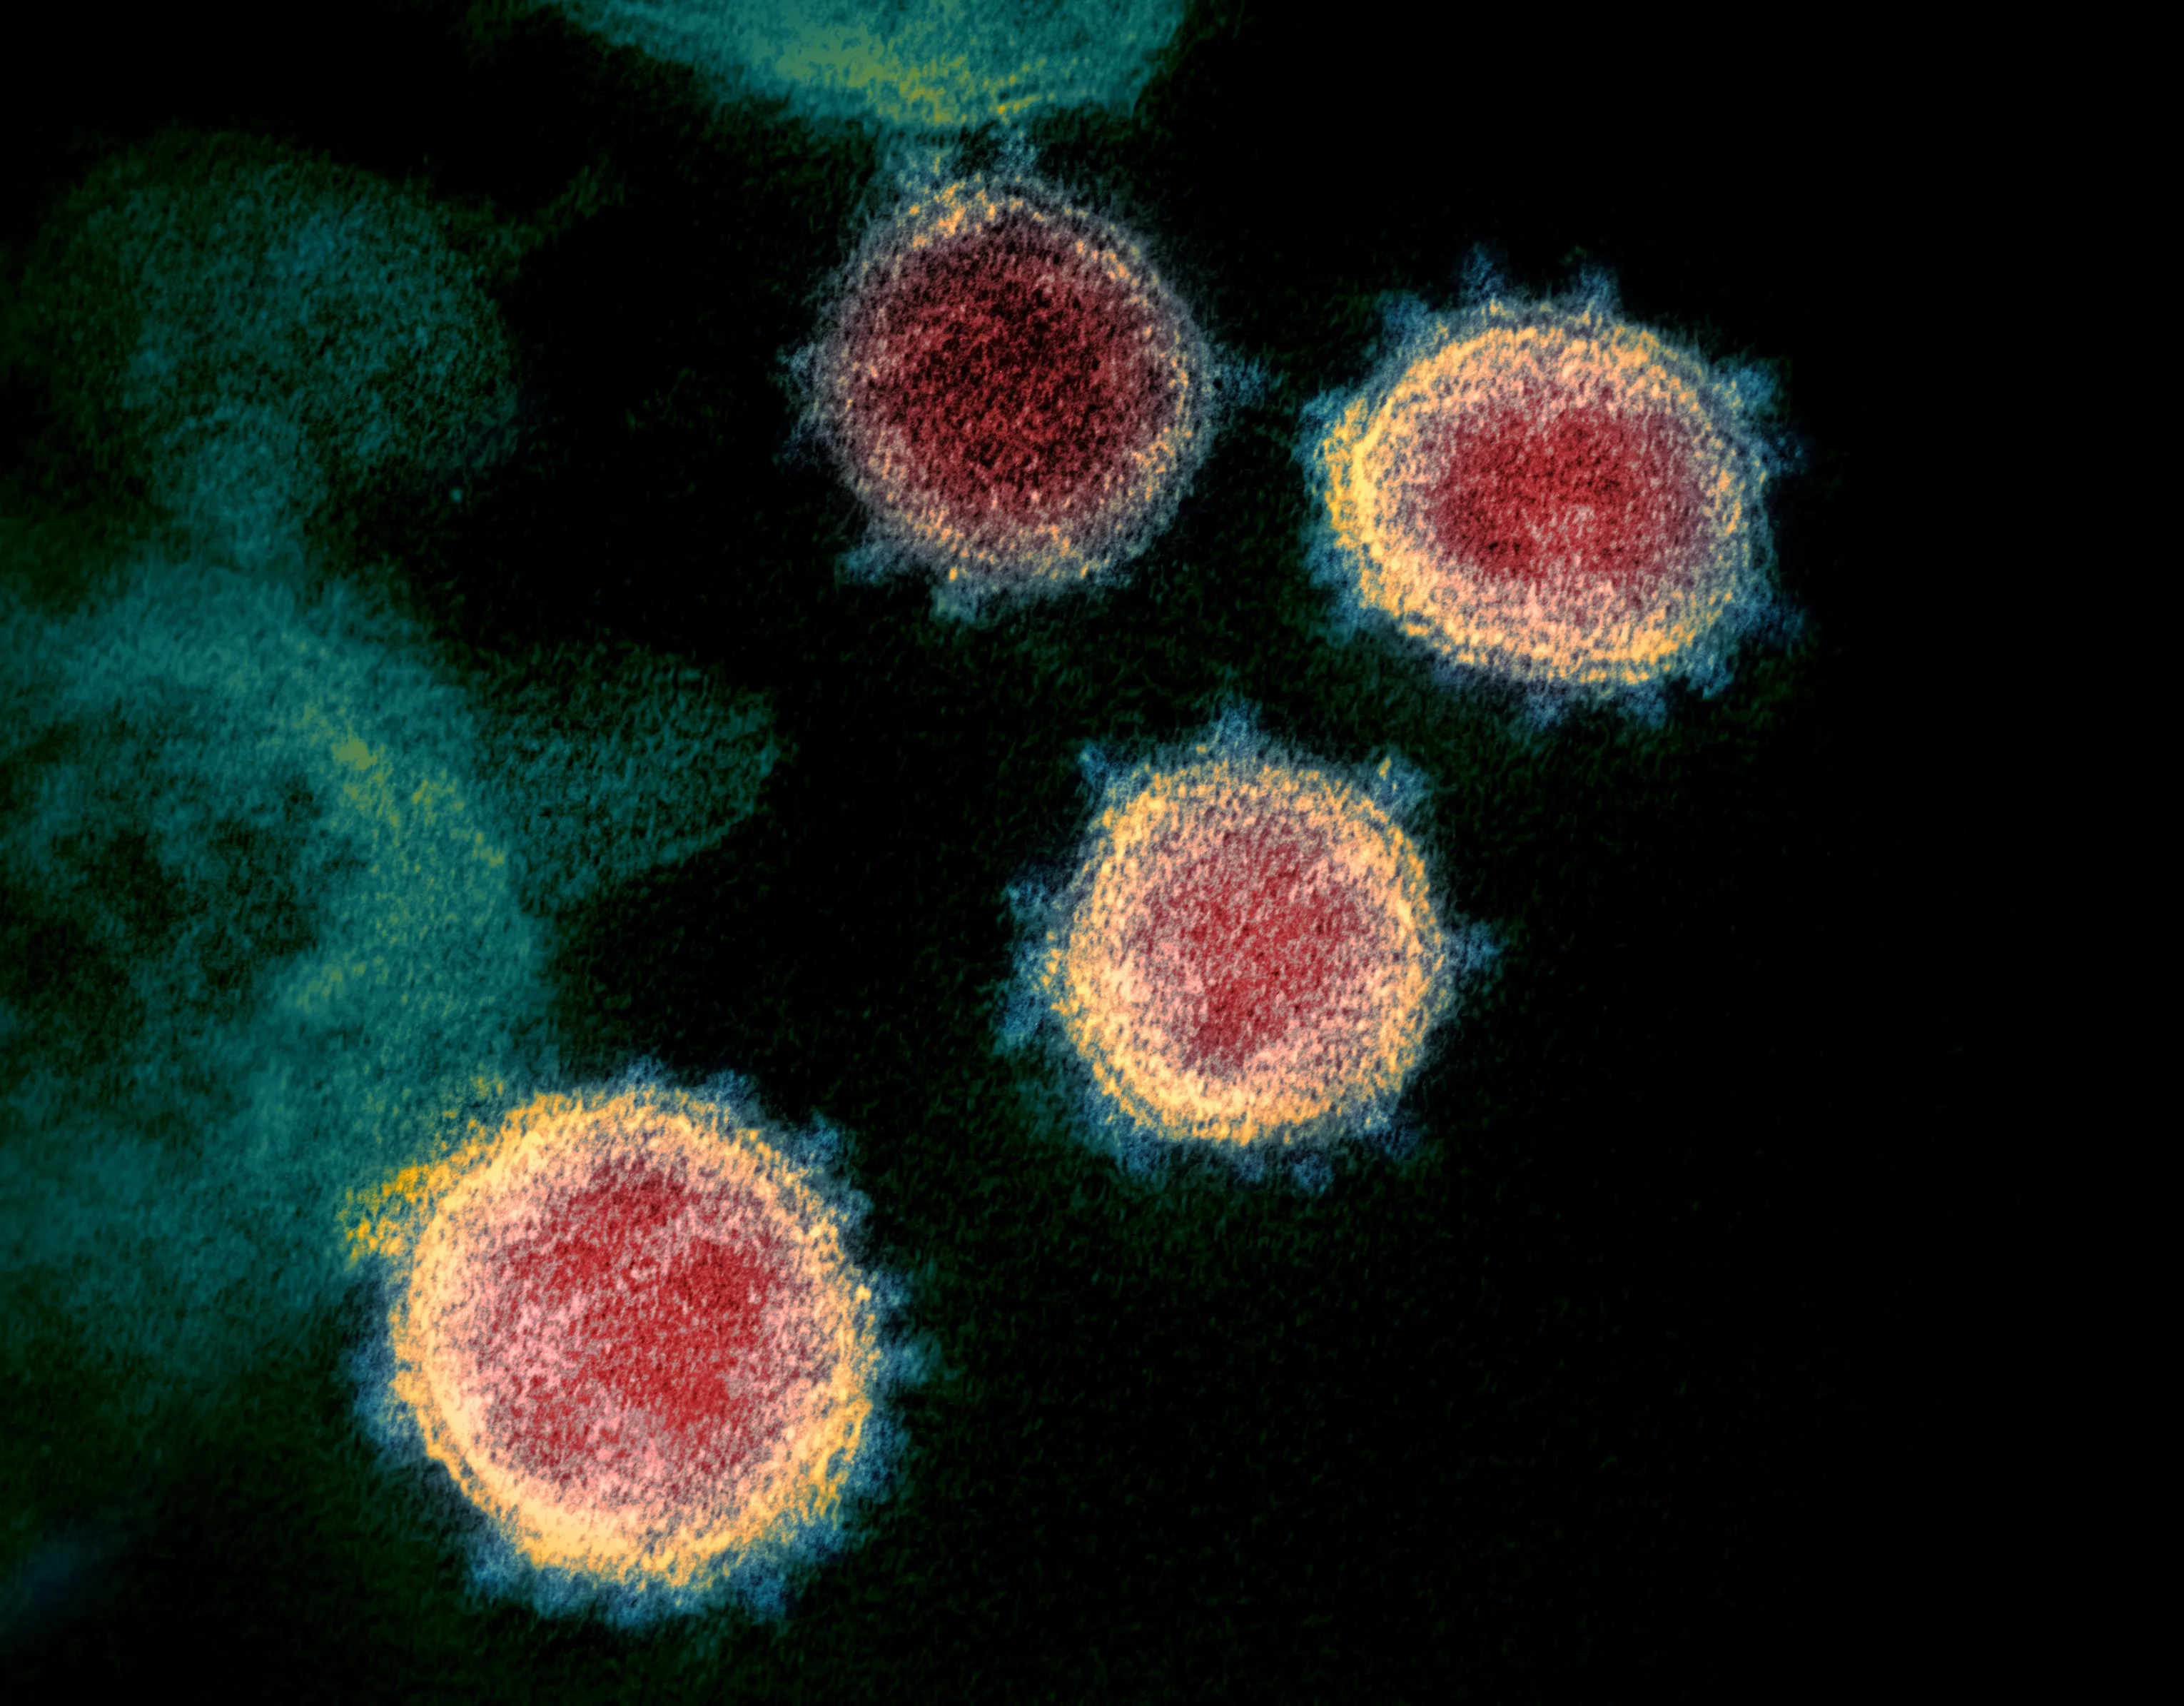

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreThe COVID-19 pandemic has caused delays in routine childhood vaccinations worldwide as health services diverted personnel, families stayed home, and routine appointments were cancelled or postponed. The disruption extended beyond shortages of a particular vaccine. Infection-control rules, lockdowns, disrupted transport, school closures, and transfers of clinicians to emergency and COVID-19 response work weakened ordinary immunisation programmes in both wealthy and lower-income countries.
Missing a scheduled dose does not always mean a child remains unprotected, but it raises the risk of delayed protection against measles, pertussis, tetanus, polio and other preventable diseases. Recovery has been uneven. Some countries quickly restored appointments through catch-up campaigns, while others still face inaccessible rural clinics, insecure funding and conflict. Australia largely protected routine services, yet disruptions in cities, schools and primary care created pockets of missed or late doses among children who had previously reached national coverage benchmarks.
WHO and UNICEF estimates show why the interruption mattered. The proportion of children receiving three doses of diphtheria, tetanus and pertussis vaccine fell from 86 per cent in 2019 to 81 per cent in 2021, while an estimated 23 million children missed basic vaccinations in 2020. Such figures combine first-time zero-dose children with others who began a multi-dose series but failed to finish it, obscuring the different remedies each group needs.
The route back has varied by setting. Mass campaigns and revised outreach restored some services quickly, while countries with persistent travel restrictions or understaffed clinics needed longer. Data systems also became a problem where paper immunisation records could not be moved between districts, or where families lacked internet access for digital reminders. The result was a backlog rather than a single interruption, with children at risk of receiving a first dose while still missing boosters and age-specific vaccines.
Workforce pressure reached every part of care. Nurses who normally ran vaccination sessions were redeployed, paediatricians treated infected patients, and cold-chain and forecasting systems had to manage competing priorities. Reviews collected through peer-reviewed medical evidence describe how emergency departments and primary-care teams were repurposed. These adaptations saved lives during the emergency, but they also shifted routine prevention into a period of reduced capacity.
For families, missed appointments often began with ordinary logistics. A parent might be working from home without childcare, unable to reach a clinic on public transport, or afraid that a crowded waiting room would expose an infant to infection. In cities under strict restrictions, travel to a vaccination service could take longer and require a permit or a booked time slot. In rural areas, a long drive and limited opening hours could make one disrupted appointment harder to reschedule.
Confidence mattered as well. False claims about vaccine safety, influenza and COVID-19 medicines spread quickly on social media, while changes to school and travel rules made official advice harder to verify. Some parents delayed appointments because they believed the virus was too new or because routine medical visits felt unsafe. Clear information from clinicians and public health teams helped distinguish a limited immunisation pause from a suspension of the vaccine programme, and live global coronavirus coverage provided context as local rules changed.
The burden fell hardest on families already facing disadvantages. Remote and refugee communities could lose access to translated information, transport and follow-up calls. Informal workers often could not take paid leave, and children in overcrowded households had fewer chances to attend a clinic alone. Pandemic control measures layered onto food insecurity, displacement and unsafe travel, making timely vaccination part of a wider struggle to maintain ordinary healthcare.
| Service element | Before the pandemic | During the disruption | What recovery requires |
|---|---|---|---|
| Appointments | Regular GP, clinic and school sessions | Cancellations, reduced hours and infection queues | More sessions, flexible times and active recall |
| Outreach | Planned visits for remote communities | Travel limits and reduced staffing | Local partnerships and transport support |
| Supply | Routine stocks matched the schedule | Competing demands affected production and forecasting | Strong forecasting, cold-chain capacity and coordinated purchasing |
| Records | Face-to-face updates were routine | Some paper records and digital reminders were interrupted | Reliable registers and prompt reporting |
| Public confidence | Established trust in immunisation | Safety claims and conflicting messages circulated | Clear advice delivered through trusted local professionals |
Australia entered the pandemic with a comparatively strong platform. The National Immunisation Program funds many vaccines at no charge, the Australian Immunisation Schedule guides their timing, and the Australian Immunisation Register records coverage. Medicare and local health networks support access through general practitioners, public health units and authorised community pharmacies. Because most childhood doses remained available, the central Australian issue was continuity of appointments and follow-up rather than the collapse seen in some disrupted health systems.
Daily life still shaped the damage. In Sydney and Melbourne, repeated lockdowns, case surges and staff redeployments led some clinics to pause or consolidate childhood sessions. Families accustomed to quick trips to a nearby GP or pharmacy had to navigate infection queues, changed opening hours and competing demands for paediatric appointments. School-based clinics also had to change their timetables when students stayed at home, making the usual point of contact less reliable for families who rely on school staff to prompt them.
The experience was different in regional and remote communities. Outreach nurses, Aboriginal health services and partnerships with local councils were important in New South Wales, northern Australia and the Northern Territory, where distance and a small workforce can turn a missed session into a delayed series. Public health agencies used text reminders, recall lists and additional clinics to recover appointments. These efforts were unevenly funded and dependent on local relationships, which explains why national averages can conceal gaps affecting particular communities.
Regulation provided a foundation for safety, but not for guaranteed attendance. The Therapeutic Goods Administration assesses vaccines under the Therapeutic Goods Act 1989, while Commonwealth and state agencies decide how the schedule is funded and delivered. State school-entry provisions, including rules in New South Wales requiring compliance with the vaccination schedule or a recognised exemption, create administrative pressure without imposing a universal vaccine mandate. During a health emergency, those laws and their public health aims still had to be applied without punishing families facing broken appointments.
The local vaccine market also affected delivery. Melbourne-based CSL Seqirus is a major Australian manufacturer and an important part of global vaccine supply, while the National Immunisation Program uses government purchasing to supply eligible doses. The pandemic placed competing claims on ingredients, production capacity and shipping routes, making forecasting essential. Local manufacturing helped buffer Australia from some shortages, yet cold-chain capacity, pharmacy distribution and available clinical staff remained more immediate constraints on a routine appointment.
Catch-up required more than sending another text message. Services could check the Australian Immunisation Register, identify overdue doses and offer short sessions during school holidays, evenings and weekends, then use other visits for vaccinations such as HPV and meningococcal doses. Community pharmacies could vaccinate eligible children, although age and vaccine rules differed. An opportunistic appointment was useful only if the register was updated, because an unrecorded dose could trigger unnecessary repeat visits or gaps in a child’s official record.
Recovery should be judged by completed, timely schedules rather than headline coverage alone. Useful indicators include the number of zero-dose children, the share who finish multi-dose sequences, median age at vaccination and the proportion of overdue children contacted. Global summaries can show the direction of change, but local data are needed to reveal whether an apparent improvement consists mainly of affluent families catching up while vulnerable communities remain outside the system.
Adaptation during the pandemic also showed that institutions could preserve essential functions under pressure. In the United States, the Supreme Court began arguments by phone as courts adjusted to remote hearings. Health services faced a harder task because a missed vaccination can be corrected only through physical access, trusted consent and accurate records. Remote communication supported reminders and triage, yet personal contact remained necessary for every dose.
Trust had to be rebuilt with consistent messages in the languages families use, transparent safety information and easy links to free services. Australia’s most successful catch-up models combined government reminders with local knowledge from GPs, schools, pharmacists and community health workers. The pandemic’s lasting lesson is that immunisation is both a medical service and a public system: clinical safety, reliable supply, accessible clinics and usable records must work together. Until routine coverage again reaches every child on schedule, the delays will remain a quiet risk even after the immediate emergency has passed.