
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
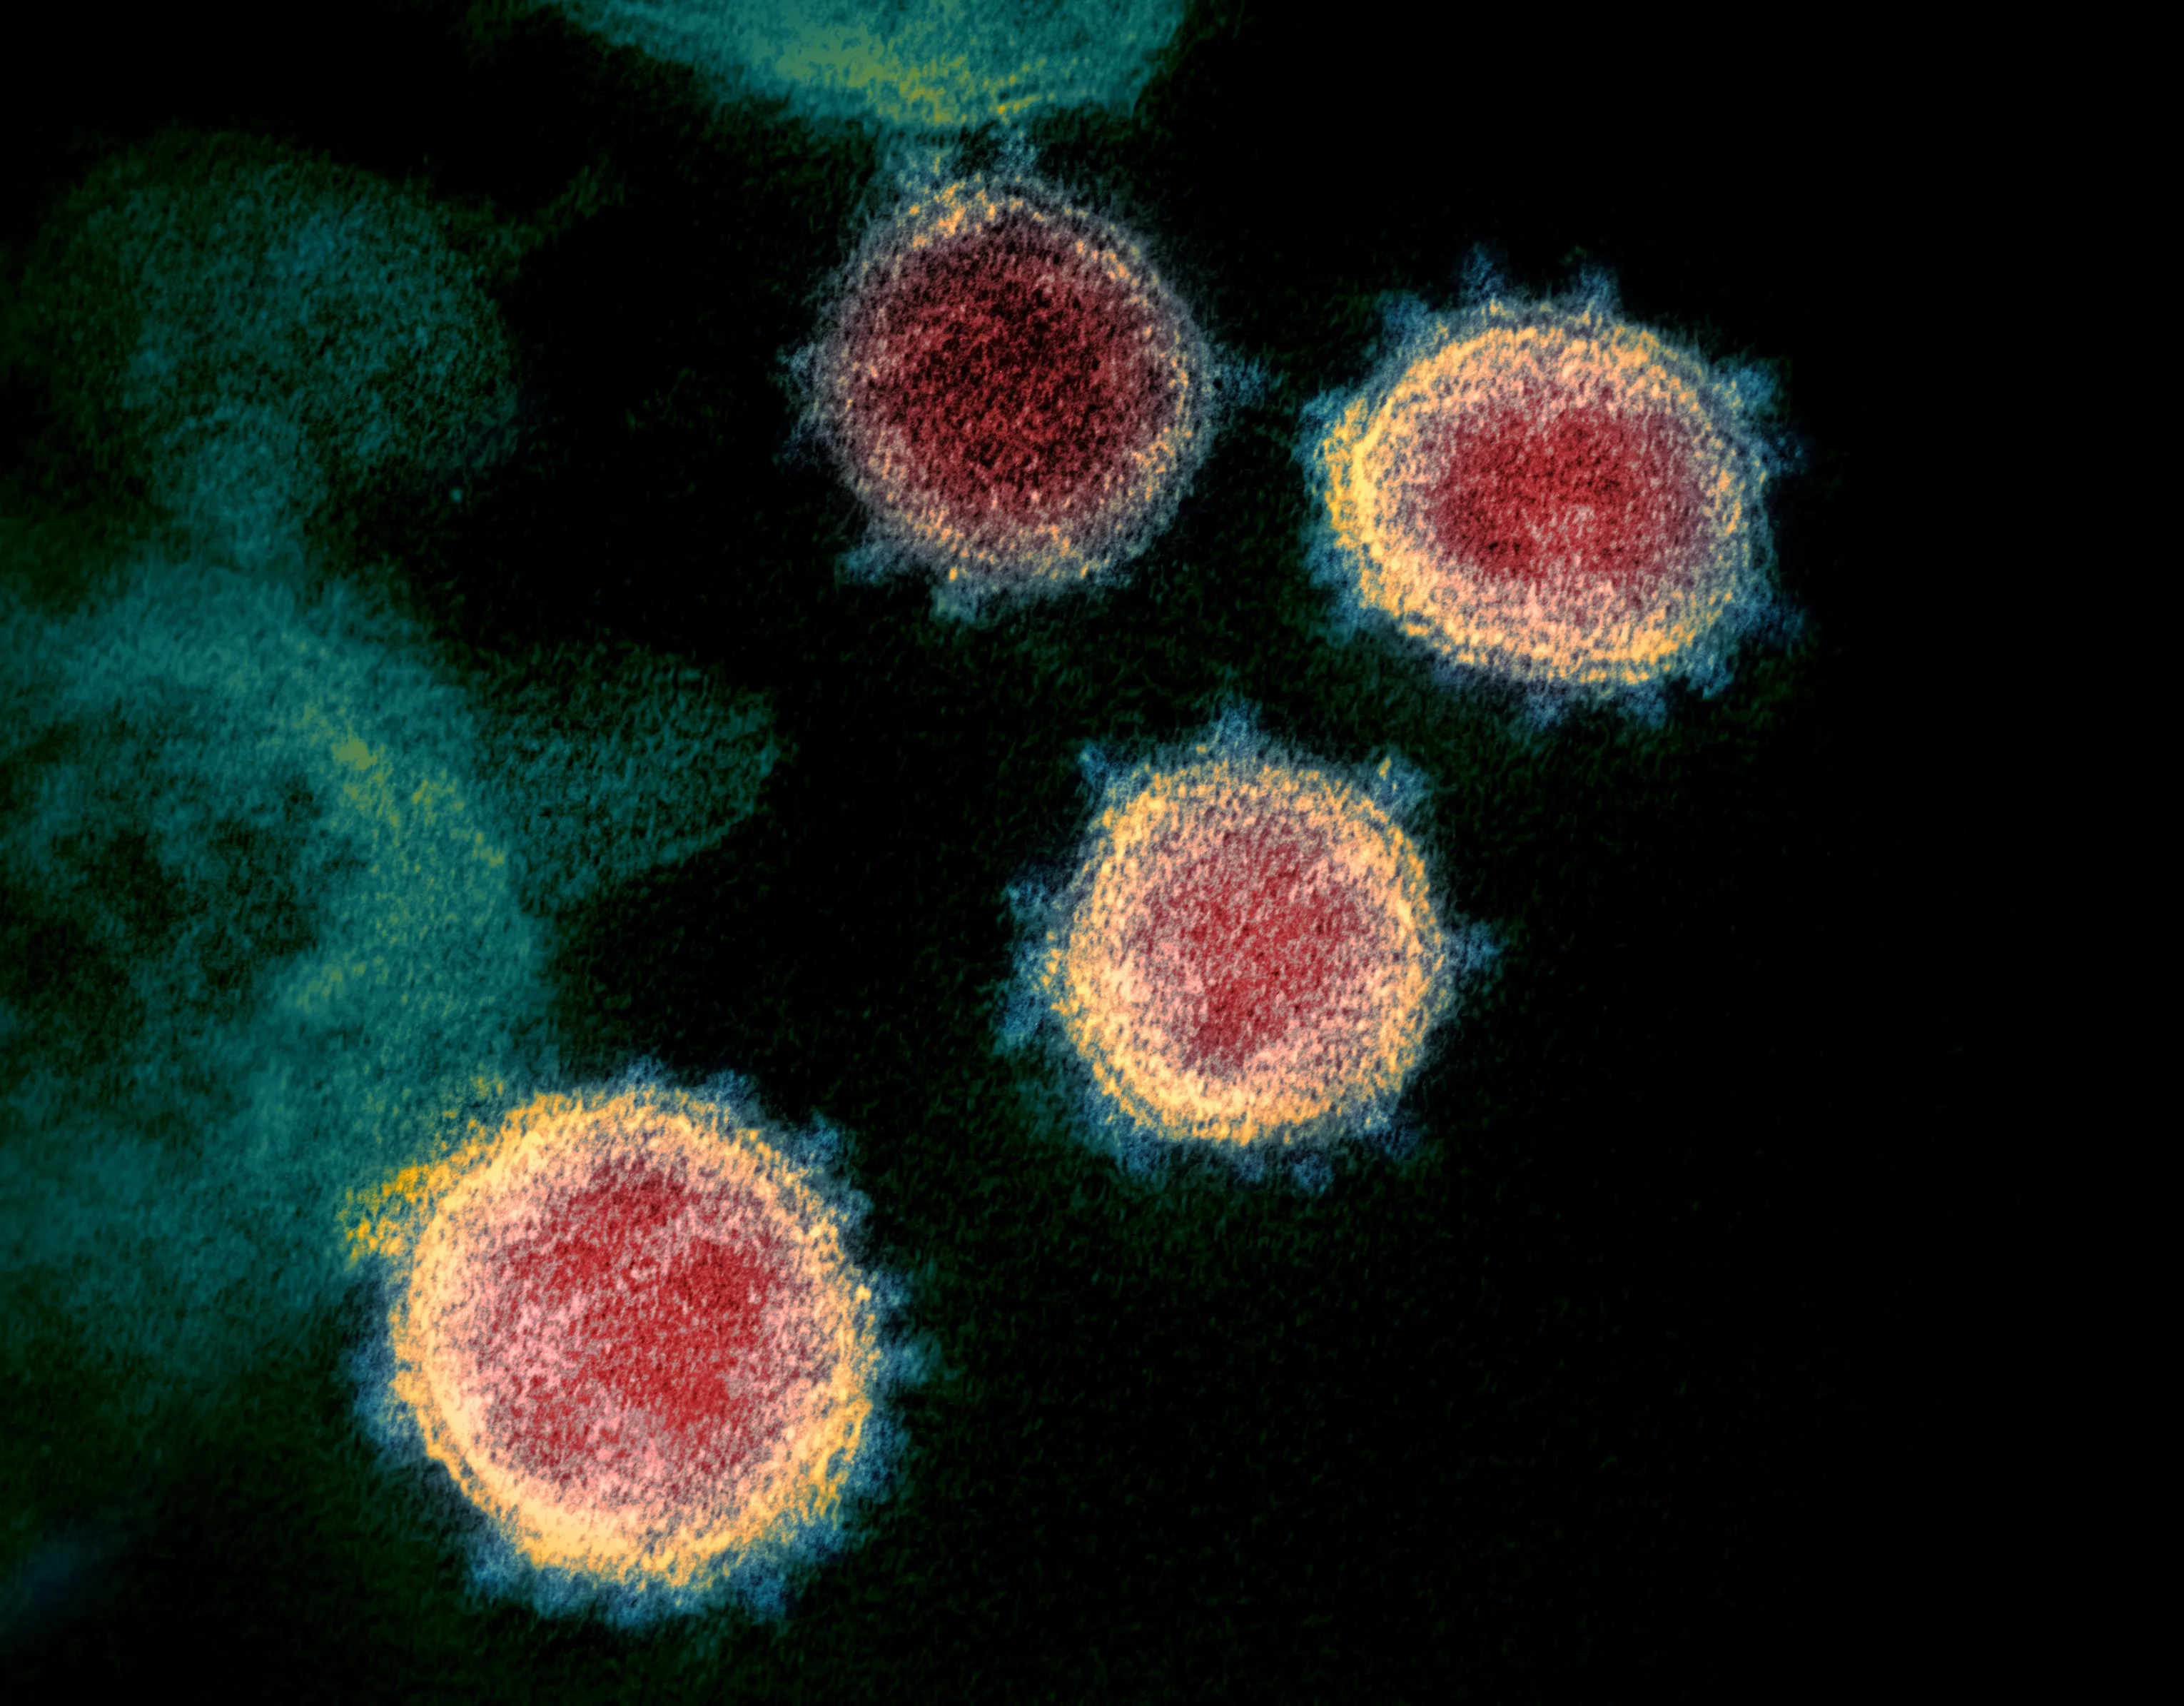

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreThe US reaches 70 percent vaccination rate but Delta variant threatens progress, with federal figures showing that seven in ten American adults had received at least one COVID-19 vaccine dose. The milestone was reached through mass vaccination sites, pharmacies and local health programmes, but it did not mean the outbreak was close to being defeated.
Health authorities warned that Delta was more transmissible than earlier variants and was spreading rapidly among partly vaccinated communities. Hospitalisations were rising in several southern and western states, while vaccination rates were uneven across counties, income groups and racial communities.
For Australians, the American experience offered both a warning and a measure of progress. It showed how quickly a large national rollout could expand, while also revealing how a highly infectious variant could undo gains when uptake stalled. Australia’s own response was shaped by state border controls, local outbreaks and an initially slow supply of vaccines.
The comparison matters because vaccination percentages describe different things in different countries. American milestones were often expressed as a share of adults, while Australian figures also tracked the total population, including children. Those distinctions can make headline numbers appear closer than the underlying level of population immunity.
The American threshold applied to adults who had received at least one dose, not to the entire population and not necessarily to those who were fully vaccinated. At the time, a smaller proportion of adults had completed the recommended vaccine schedule, leaving a substantial gap between first-dose access and protection against severe disease.
The rollout was supported by an unusually large delivery network. Federal agencies used mobile teams and community partners, while pharmacies became an important access point in areas without traditional medical clinics. Employers also organised workplace programmes, and public health departments converted schools, sports facilities and conference centres into temporary vaccination sites.
Reaching the milestone did not establish uniform protection. Some counties had vaccinated most eligible residents, while others recorded rates low enough for sustained transmission. Public health researchers also identified gaps among rural communities, people without reliable transport and groups that had experienced unequal access to healthcare before the pandemic.
Delta’s principal advantage was its ability to spread between people who had close contact, including in households and workplaces. Genomic surveillance showed it becoming dominant in many regions, making the earlier assumption that lower case numbers would automatically produce declining hospital admissions increasingly uncertain.
Vaccination remained highly effective at reducing severe illness, although protection against infection was weaker than against earlier variants. Breakthrough cases therefore did not mean vaccines had failed. Their significance lay in how many occurred and whether they led to hospital admissions, particularly among older people and those with underlying conditions.
That distinction shaped American policy debates. Some states focused on hospital capacity and vaccination incentives, while others reinstated indoor masks or limits on large gatherings. The most effective response depended on combining vaccination with testing, ventilation, sick-leave support and clear communication, especially where community uptake remained low.
Australia began from a different starting point. State and territory governments operated separate booking systems, with vaccination delivered through public hubs, general practitioners, pharmacies—often called chemists by many Australians—and community pop-ups. This mixed model allowed trusted local providers to reach regional and culturally diverse communities, but it also created a patchwork of eligibility rules and appointment availability.
| Measure | United States milestone | Australian position in mid-2021 | Why it mattered |
|---|---|---|---|
| Initial coverage | About 70% of adults had received one dose | Fewer than one in three Australians had started vaccination | The gap affected how quickly communities could be protected |
| Full vaccination | Close to 60% of adults were fully vaccinated | Less than one in four Australians were fully vaccinated | Dose completion mattered for protection against hospitalisation |
| Delivery network | Pharmacies, mass clinics, employers and local health departments | State hubs, GPs, chemists and community clinics | Local trust shaped uptake in both countries |
| Main concern | Uneven county-level coverage and fast Delta spread | Low coverage in parts of Sydney and other outbreak areas | Local pockets could sustain transmission despite national gains |
| Policy response | Mask guidance, vaccine incentives and hospital capacity planning | Border restrictions, testing, quarantine and state outbreak rules | Federal systems could not control every local outbreak |
Australian data also separated states sharply. The Australian Capital Territory and some other jurisdictions built momentum earlier, while parts of New South Wales, Queensland and the Northern Territory struggled to attract first-dose bookings. Sydney’s western and south-western suburbs became a particular focus because low vaccination coincided with several Delta outbreaks.
Melbourne faced a different experience through lengthy lockdown, widespread testing and a state-managed vaccine push tied to workplace and community hubs. Victorians also became familiar with rapid testing and QR-code check-ins, practices that gave authorities more visibility into transmission than many countries had at the start of 2020.
New South Wales demonstrated how an initially contained Delta outbreak could expand through gatherings, households and workplaces. Restrictions focused on western Sydney and other areas with lower vaccination, while testing sites and community teams were directed towards affected communities. The response also exposed how difficult it was to reach people who were tired of restrictions or distrustful of institutions.
Melbourne’s repeated lockdowns showed the cost of relying on suppression while vaccination remained incomplete. Reduced mobility could interrupt transmission, but it also disrupted employment, education and mental health. Border closures and quarantine systems offered time to increase vaccine supply, yet each state and territory government often imposed different rules on residents and businesses.
Australia’s use of the term “double-vaxxed” became part of everyday conversation during the rollout. Many people also referred simply to “the jab”, while workplaces and community organisations shared photographs and messages from people who had been vaccinated. This informal language helped make the campaign visible, although public health officials warned that personal enthusiasm could not compensate for structural barriers.
In the United States, the vaccination campaign became entangled with partisan identity, election politics and debates over federal and state authority. Financial incentives helped some employers increase uptake, while vaccine mandates in healthcare, military and other workplaces generated both higher coverage and legal challenges. The sharpest resistance occurred where distrust of government was already widespread.
Australia faced similar questions through different institutions. State governments controlled most health restrictions, while the Australian Government funded vaccine procurement and national communication. The Australian Technical Advisory Group on Immunisation provided advice on when and how the population should be offered Pfizer, Moderna and AstraZeneca vaccines, with the Therapeutic Goods Administration responsible for regulatory approval.
Access was not simply a matter of personal choice. Shift workers struggled to attend daytime clinics, older residents needed reachable locations, and people with limited English faced barriers when booking systems and health information were not available in their language. Temporary exemptions for medical conditions, overseas supply rules and the timing of second doses also added complexity to national comparisons.
Online misinformation became another obstacle. False claims about vaccine safety, immunity and testing were spread through social media groups and messaging apps, often by people who combined unrelated medical reports into convincing-sounding narratives. Readers seeking wider context beyond specialist reporting can consult broader news context when comparing how different health milestones were presented.
The American milestone became a reference point for governments trying to persuade hesitant populations that vaccination remained worthwhile. Countries below that level studied the US rollout, while those facing major Delta outbreaks were warned that high coverage could not be judged by national averages alone. Local vaccination gaps continued to determine where new clusters emerged.
Australia’s experience also highlighted the importance of adaptable supply chains. Delayed deliveries and changing clinical guidance affected second-dose schedules, while demand shifted across states as residents responded to border closures, employer requirements and local outbreak alerts. The vaccine campaign gradually expanded beyond metropolitan hubs into regional towns, mobile clinics and workplaces where employees could be reached during paid time.
The wider lesson was that percentage milestones needed context. Coverage, dose completion, age distribution, variant prevalence and hospital capacity all told different parts of the story. Delta could circulate widely without producing the same level of severe illness in a well-vaccinated population, but it could still exploit every pocket of low coverage.
Continued monitoring therefore remained essential. Genomic sequencing identified new variants, hospital data showed the effect of changing case numbers, and local reports revealed where barriers to vaccination persisted. CoronavirusNewsLive readers can follow live pandemic updates as the global picture develops. Whether the 70 percent American milestone represented durable control or a temporary high point would depend on how quickly vaccination reached the communities where Delta was already spreading.