
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
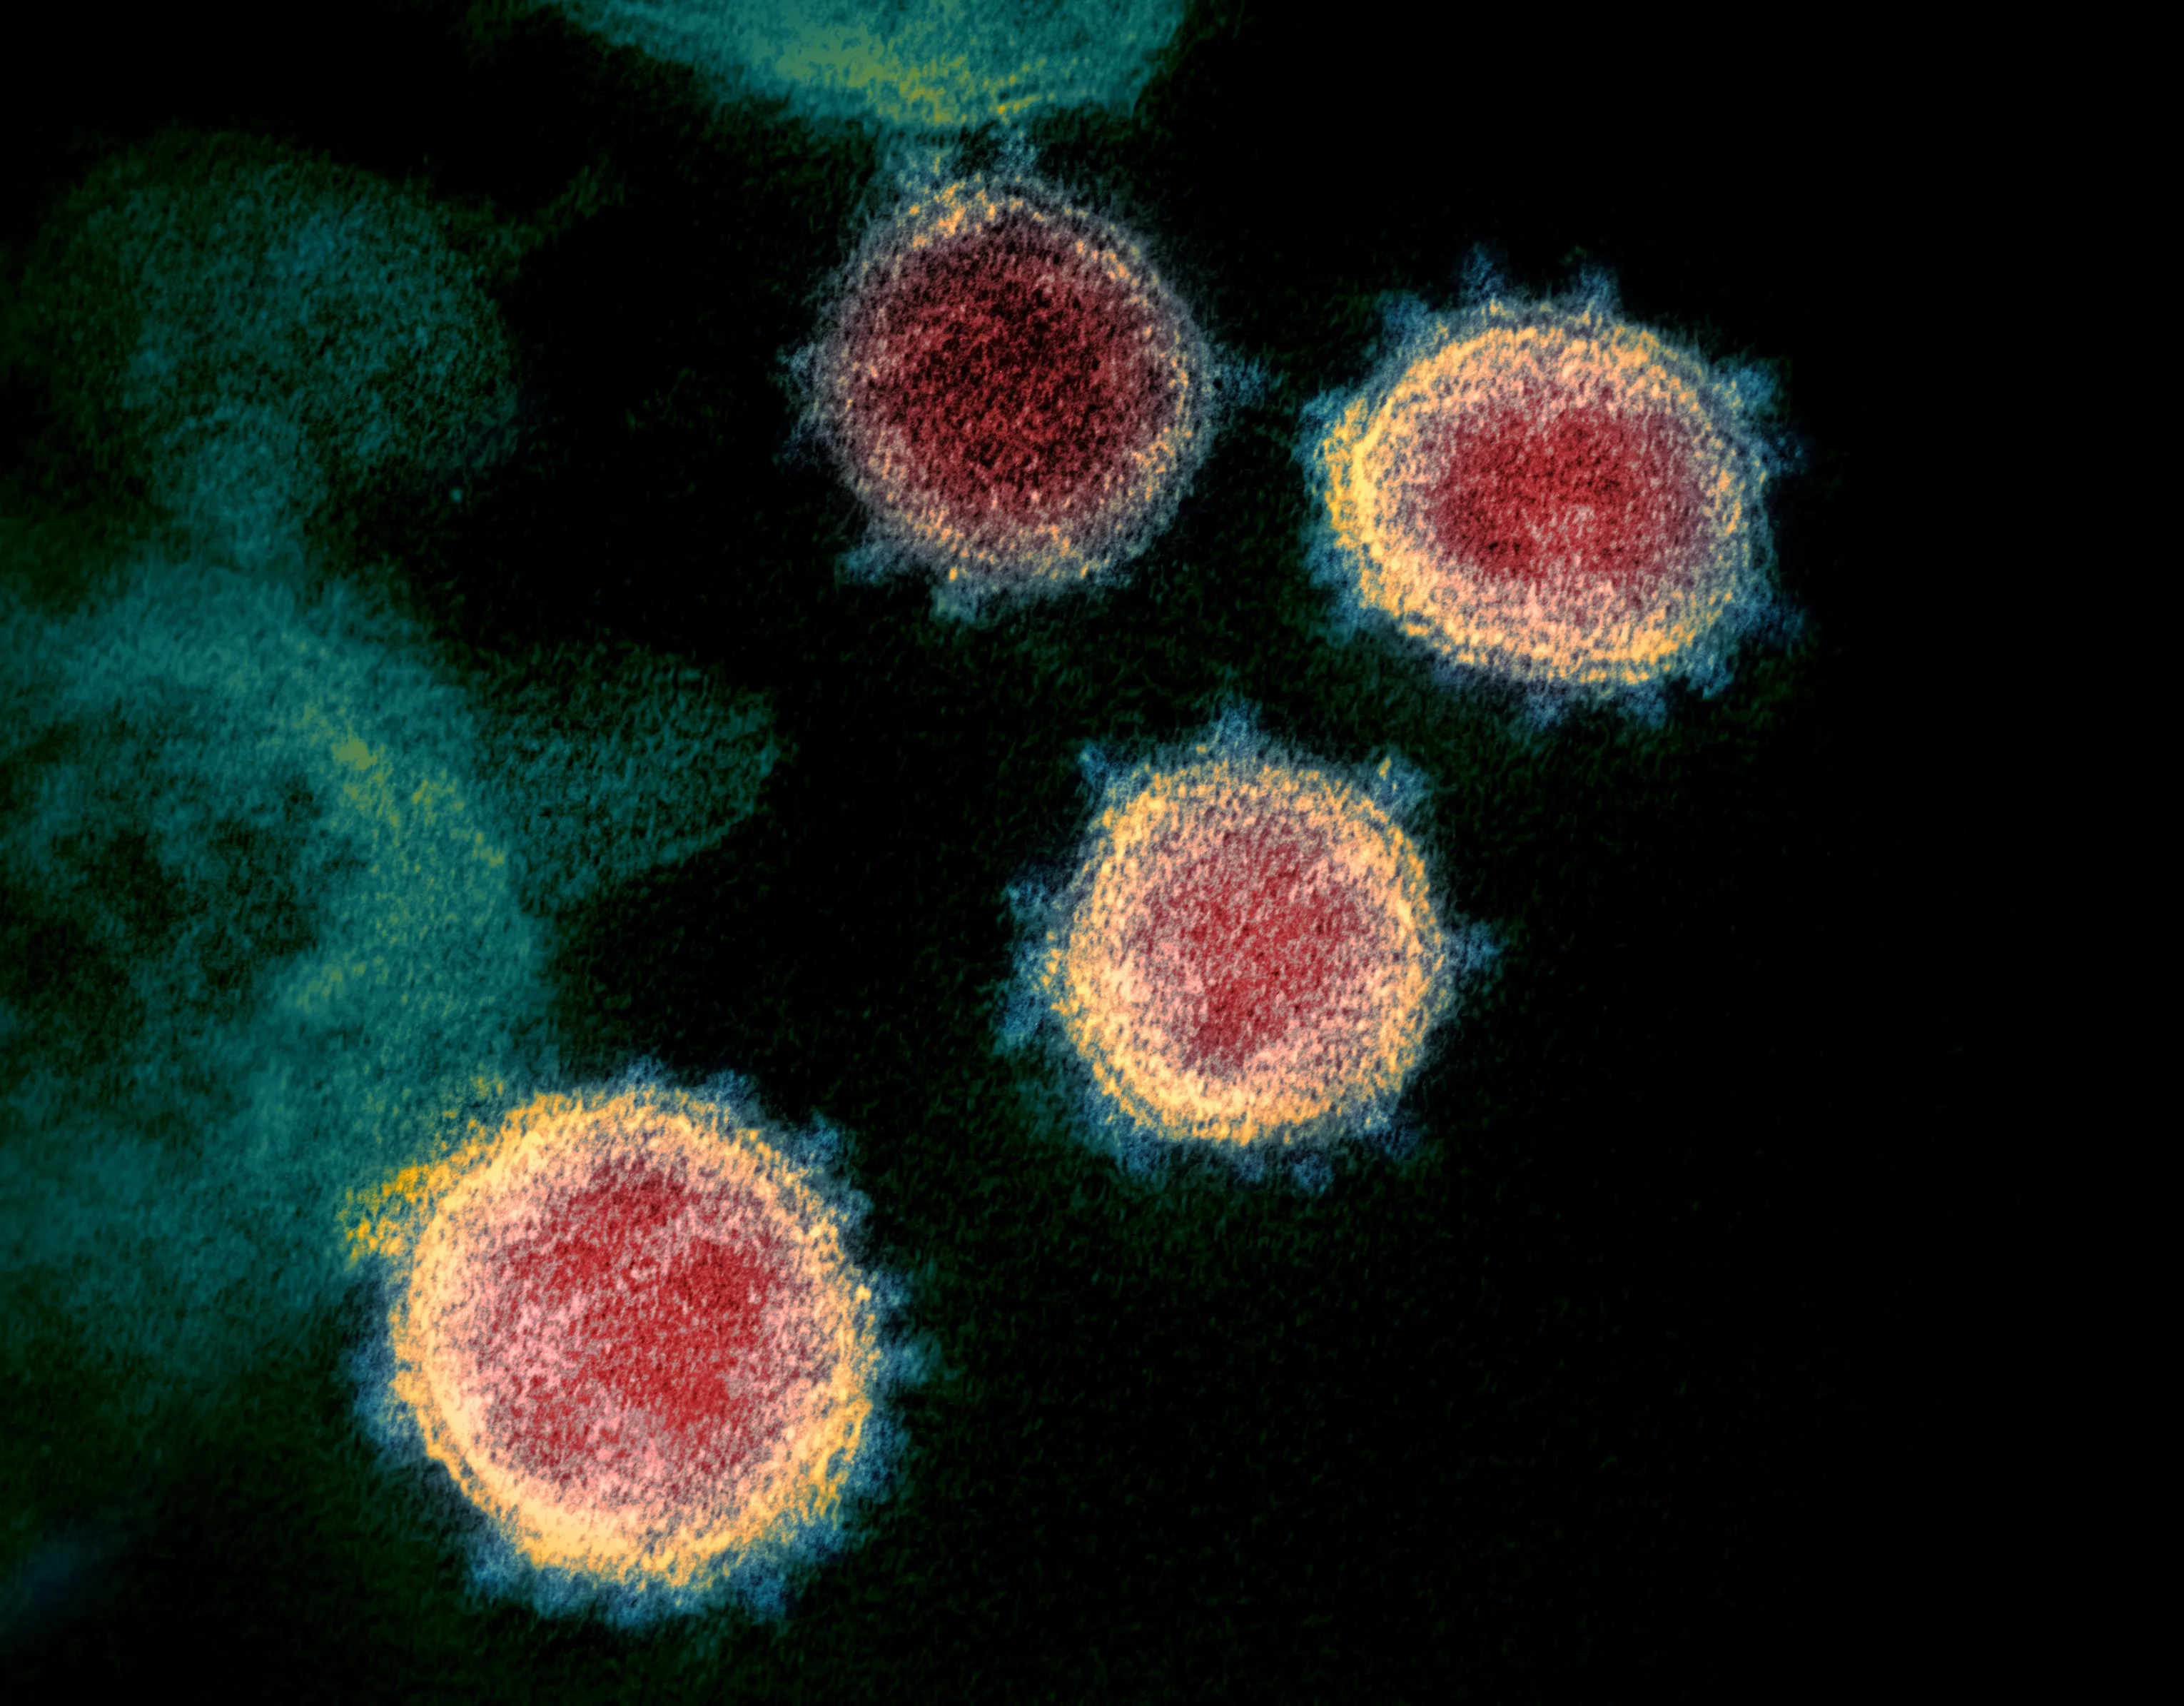

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreRecent reports from a multinational research consortium describe an antibody-based therapy capable of neutralising every SARS-CoV-2 lineage tracked to date, including heavily mutated Omicron descendants that have outpaced several earlier monoclonal products. The data, published in a peer-reviewed journal in late 2025, has stirred cautious optimism among clinicians who spent the early 2020s racing to update treatment protocols with each fresh wave.
The candidate, currently referred to as VYD-911 in trial registries, was engineered from memory B-cells recovered from donors who had survived multiple rounds of infection and vaccination. Researchers say its binding footprint spans a conserved region of the spike protein that rarely mutates without compromising the virus's ability to enter human cells. By targeting a stable viral hinge rather than the hypervariable tip of the spike, the molecule appears to retain potency even as the pathogen continues to drift.
For Australians who weathered extended lockdowns in Melbourne and Sydney, the news lands at a moment when complacency has crept into public discourse even as wastewater surveillance in Brisbane and Perth continues to detect viral fragments. Federal authorities have repeatedly reminded the public that the pandemic is not over, but routine testing has fallen sharply since mandatory reporting ended, leaving virologists partly reliant on sewage signals to gauge community transmission.
Health authorities at the federal and state level have signalled cautious interest, noting that antibody therapies could fill gaps left by vaccines in immunosuppressed populations and could serve as a rapid-response option if a strain resistant to current immunity emerges. Coverage of related new variant alerts from Southeast Asia has intensified calls for pan-variant prophylactics that do not require reformulation every time the virus spawns another descendant.
VYD-911 is not a single antibody but a combination of three engineered immunoglobulins selected for complementary binding angles. Researchers used cryo-electron microscopy to map how each arm of the cocktail grips the spike trimer, then computationally optimised the fragments to extend their half-life in human blood. The resulting molecule stays in circulation long enough to provide several months of passive immunity, an interval that aligns with the dosing schedules already in use for similar products in Australian hospitals.
Unlike convalescent plasma, which varies in potency from donor to donor, monoclonal combinations are manufactured under tightly controlled conditions, allowing clinicians to predict response rates with reasonable confidence. The lead investigators disclosed that VYD-911 was designed to resist viral escape by binding to a region that the spike protein cannot easily remodel without losing the structural flexibility required for membrane fusion.
A second innovation lies in the antibody's effector function. The molecule was tuned to flag infected cells for destruction by natural killer cells, providing a second line of defence beyond simple viral neutralisation. Laboratory experiments suggest that this dual action may also reduce the reservoirs of lingering virus that some researchers associate with persistent symptoms after acute infection.
Phase II data drawn from more than 1,800 participants across the United States, Brazil, South Africa, and Japan showed an 84 percent reduction in symptomatic infection among high-risk household contacts who received the antibody within five days of exposure. The same study recorded a 91 percent reduction in hospitalisation among vaccinated adults over the age of 65 who were treated after testing positive.
Crucially, the researchers tested serum from treated participants against a panel of pseudoviruses engineered to carry spikes from every variant of concern, including BA.2.86, JN.1, and the recently tracked XEC lineage. Neutralisation titres remained within an order of magnitude across the panel, a stark contrast to earlier monoclonals whose effectiveness collapsed once Omicron displaced Delta in 2022. The investigators describe the breadth of coverage as the most extensive seen in any antibody candidate to date.
Independent commentators caution that pseudovirus assays do not always predict clinical performance, and that real-world effectiveness depends on factors such as the dose administered, the timing of administration, and the recipient's underlying immune status. Still, the consistency of the laboratory signal across such a wide variant set has drawn attention from regulators in the European Medicines Agency and the United States Food and Drug Administration.
Australian scientists played a substantial role in the early characterisation of VYD-911, with teams at the Doherty Institute in Melbourne and the Kirby Institute in Sydney contributing viral isolates and pseudovirus reagents used in the neutralisation assays. Researchers at the University of Queensland's Centre for Clinical Research in Brisbane coordinated recruitment for the adult outpatient cohort, drawing participants from general practices around the Brisbane River corridor.
Several Australian hospitals, including Royal Melbourne, Royal Prince Alfred in Sydney, and the Queen Elizabeth Hospital in Adelaide, are expected to participate in the upcoming Phase III expansion. Patients with primary immunodeficiency, organ transplant recipients, and people undergoing B-cell depleting therapy for autoimmune conditions will be prioritised, reflecting local concerns that these groups respond poorly to vaccination alone.
The Australian Department of Health and Aged Care has confirmed that it is monitoring the trial closely through the Therapeutic Goods Administration's provisional registration pathway. If Phase III results mirror the earlier signals, sponsors are likely to lodge an application for provisional approval within twelve months, a timeline consistent with the rolling reviews used for the original mRNA vaccines.
For the estimated 500,000 Australians living with some form of immunocompromise, broadly neutralising antibodies could fundamentally reshape preventive care. Many of these patients mount weak or undetectable antibody responses after vaccination and continue to mask, avoid crowds, and decline invitations to indoor gatherings long after the broader community returned to normal.
Clinicians also see potential in treating acute infection to reduce the likelihood of post-acute sequelae. While the evidence remains mixed, several observational studies have suggested that early administration of neutralising antibodies lowers the odds of developing persistent fatigue, breathlessness, and cognitive fog. The investigators behind VYD-911 have embedded quality-of-life questionnaires into their trial protocols in an attempt to settle that question.
For Aboriginal and Torres Strait Islander communities in remote parts of the Northern Territory and Western Australia, where access to hospital-based care can require long flights, a long-acting injectable product could reduce the need for repeated travel to infusion centres. Community-controlled health organisations have long advocated for therapies that can be delivered locally, and the team running the Australian arm of the trial is in early discussions about decentralised delivery through Aboriginal Medical Services.
Australia's Therapeutic Goods Administration evaluates monoclonal antibodies through the same framework used for vaccines and antivirals, weighing quality, safety, and efficacy data before granting either provisional or full registration. Once registered, a product typically requires a separate recommendation from the Pharmaceutical Benefits Advisory Committee before it can be subsidised through the Pharmaceutical Benefits Scheme and made affordable for patients.
Cost will be a major consideration. Earlier monoclonals such as sotrovimab and tixagevimab were listed on the PBS during the Omicron wave, but the listing lapsed when demand fell and global supply contracts expired. The sponsors of VYD-911 have signalled an interest in a longer-term arrangement, potentially modelled on the standing orders used for seasonal influenza antibodies that protect high-risk residents of aged care facilities.
State governments are also weighing how to incorporate the therapy into existing respiratory clinics. New South Wales has hinted at pilot programs in western Sydney, where vaccination uptake lagged behind the inner-city eastern suburbs throughout the booster campaigns. Victoria, Queensland, and Western Australia are expected to watch closely before committing their own funding. Online health platforms now host candid assessments of treatments across many disciplines, from monoclonal antibody infusions evaluated in major hospitals to allied services such as parent-child interaction therapy offered to families seeking speech and language support, illustrating how patient reviews increasingly shape clinical decision-making.
The arrival of broad-spectrum antibodies does not displace vaccines, which remain the most cost-effective tool for population-level protection. Vaccines train the immune system to recognise and remember the virus, while antibodies provide immediate but temporary protection.
Antivirals such as nirmatrelvir-ritonavir remain valuable for early outpatient treatment but require timely diagnosis and may interact with common cardiac and psychiatric medications. They also depend on patients initiating therapy within five days of symptom onset, a window that some Australians miss because of limited access to rapid testing in regional areas.
| Therapy | Mechanism | Typical dosing | Variant coverage | Main use |
|---|---|---|---|---|
| mRNA vaccines | Train host immunity | Two-dose primary plus boosters | Updated periodically | Population prevention |
| VYD-911 antibody | Passive neutralisation | Single subcutaneous or intramuscular dose | All known variants to date | Post-exposure prophylaxis, immunocompromised support |
| Nirmatrelvir-ritonavir | Protease inhibition | Twice daily for five days | Strong against most variants | Early outpatient treatment |
| Sotrovimab (legacy) | Monoclonal neutralisation | Single intravenous infusion | Reduced efficacy against recent Omicron lineages | Largely discontinued in Australia |
| Convalescent plasma | Donor antibodies | Single or repeated transfusion | Variable by donor | Reserved for specific cases |
The table highlights the niche that broad-spectrum antibodies are best positioned to occupy: rapid, durable protection for people who cannot mount a reliable vaccine response, or as a bridge after high-risk exposure when antiviral stocks are limited. For everyday Australians who are healthy and up to date with their boosters, vaccines will continue to be the first line of defence, supported by antivirals when breakthrough infections occur.
Practical guidance for Australians following the news
Readers who want to make sense of the evolving antibody landscape can take several concrete steps: