
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
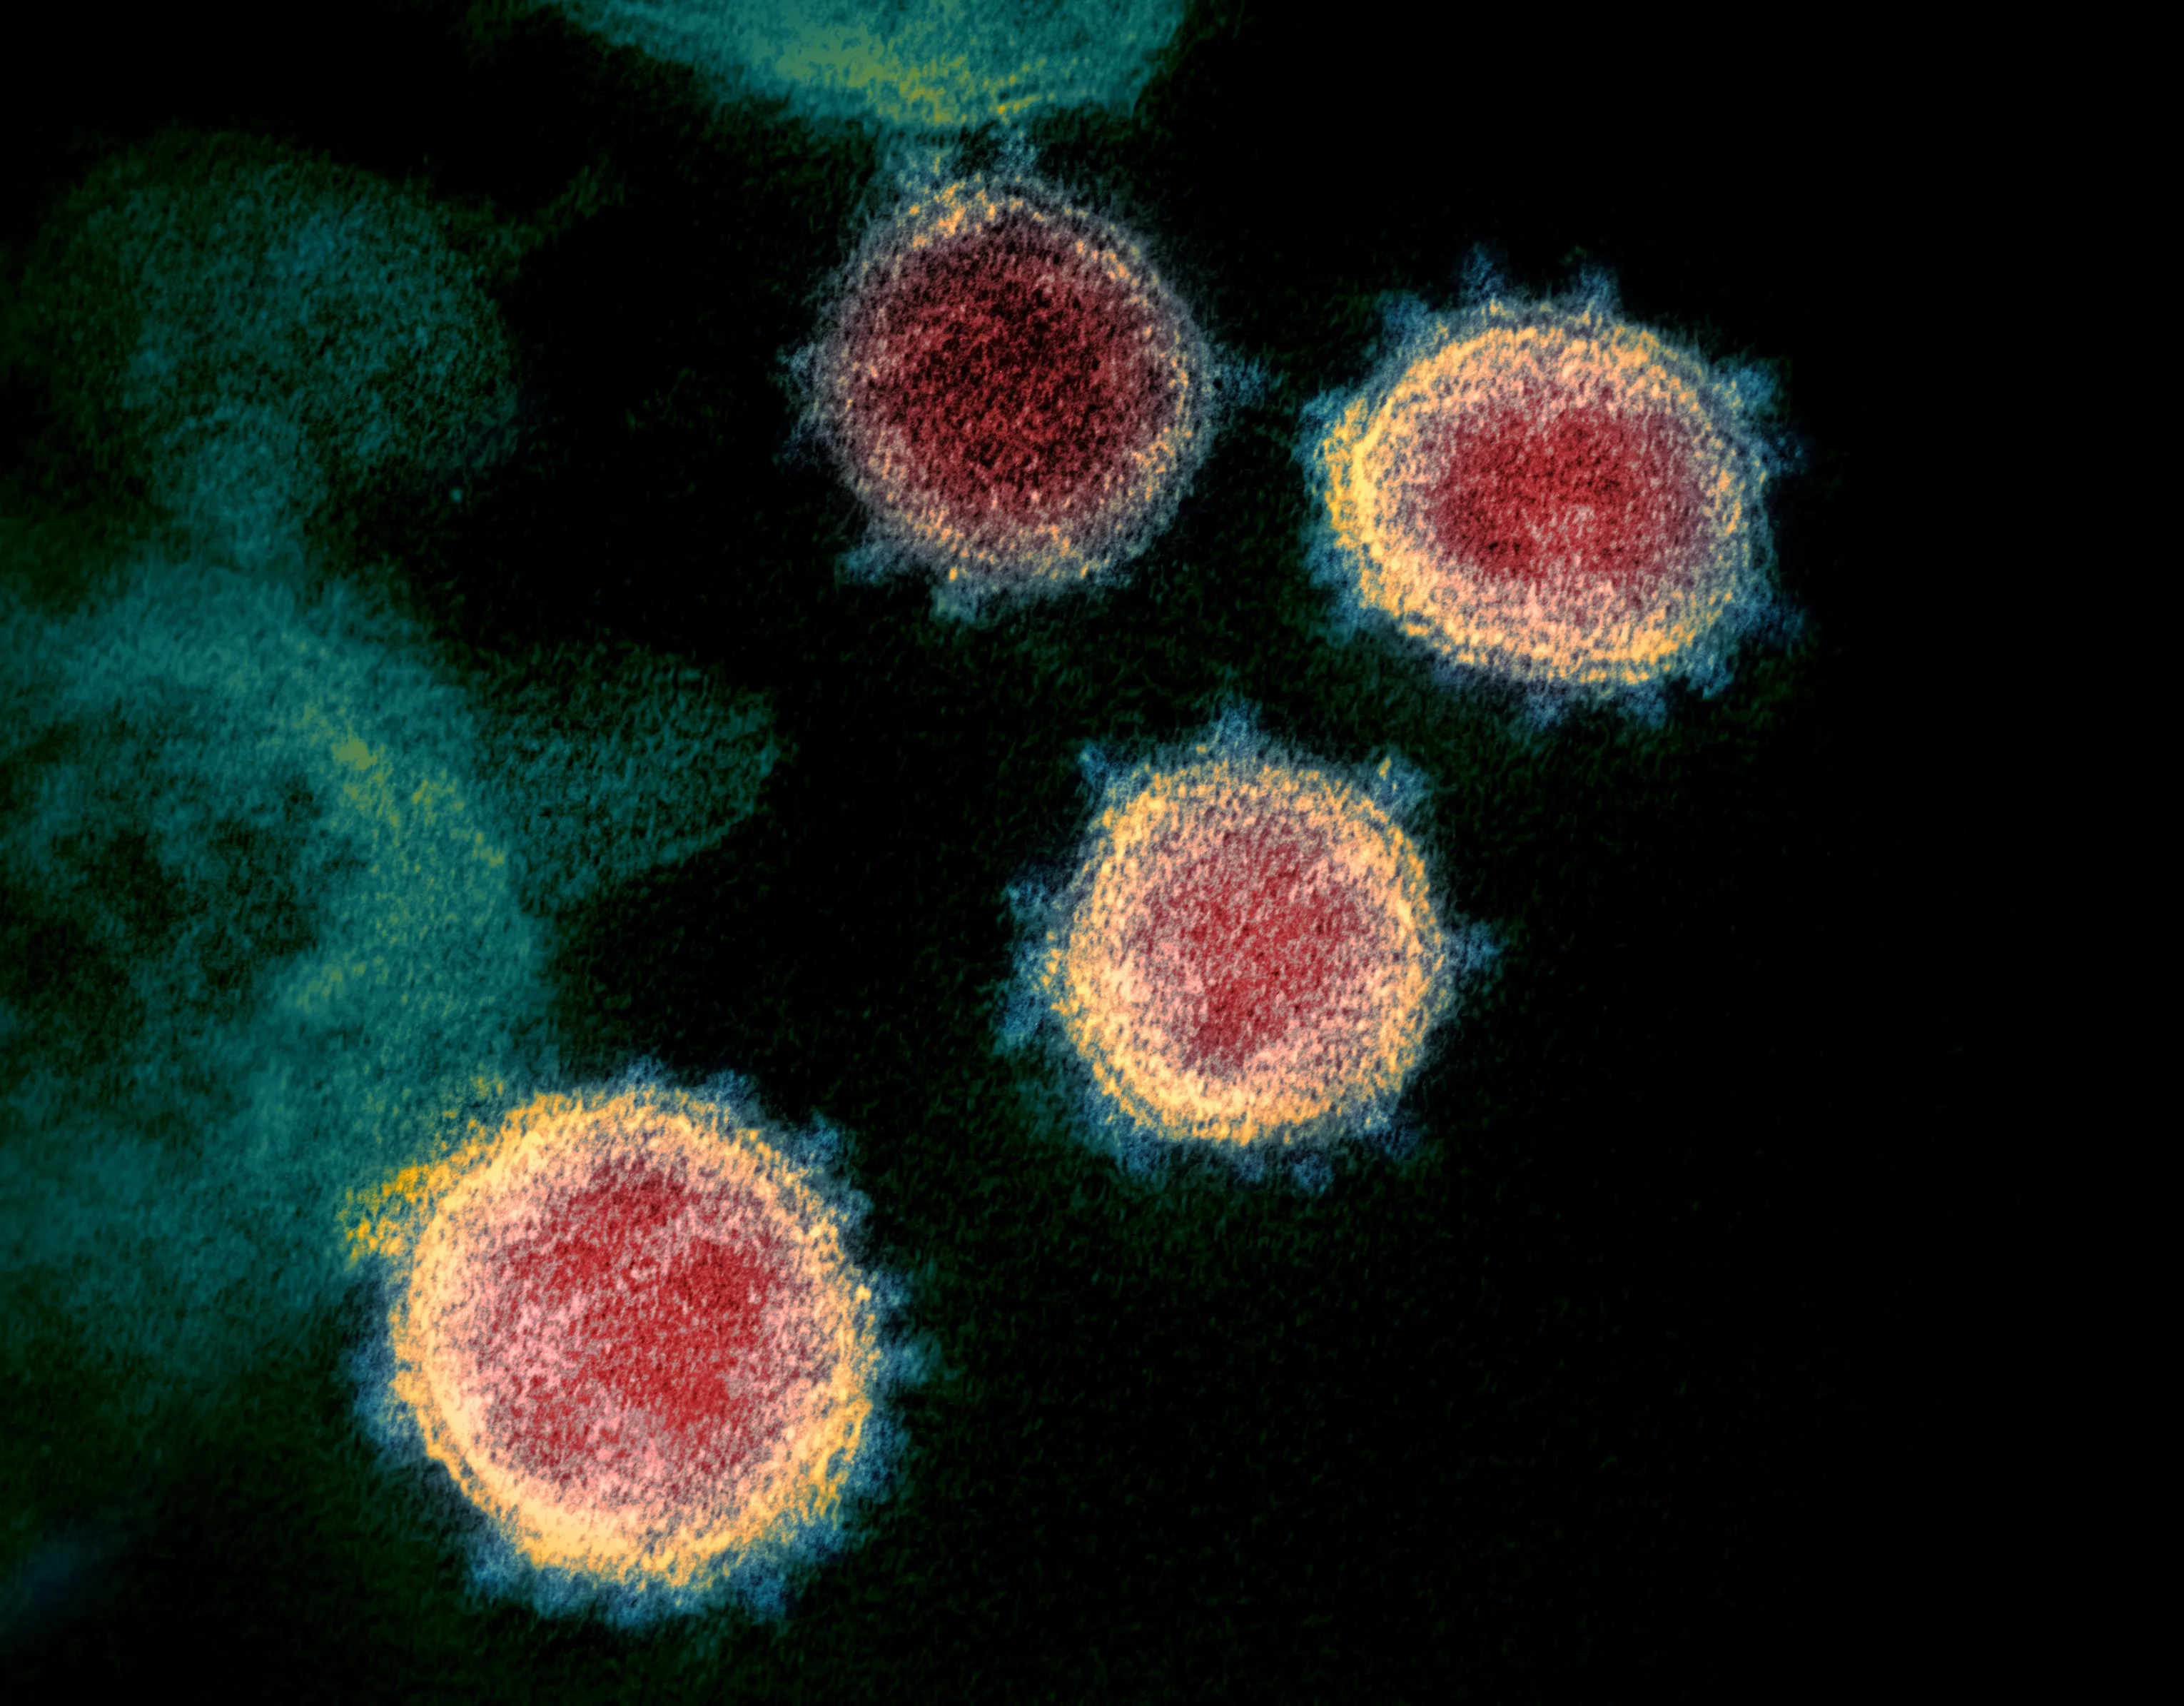

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreA new specialty clinic has opened in Manhattan this month, offering coordinated care for adults still wrestling with the lingering effects of SARS-CoV-2 infection. The facility brings together cardiologists, neurologists, pulmonologists and physiotherapists under one roof, run by a coalition of academic physicians and post-infectious illness specialists. Patients either self-refer or are sent by their GP through a dedicated portal, undergo a full multidisciplinary assessment, and are then routed into tailored treatment tracks. The launch arrives as clinicians across the United States report sustained demand for post-viral care, and as global health bodies continue refining how to define, diagnose and resource the condition.
Long COVID, sometimes called post-acute sequelae of COVID-19, refers to a wide constellation of symptoms that persist for weeks, months or even years after the initial infection has cleared. Fatigue, brain fog, breathlessness, palpitations, sleep disturbance and post-exertional malaise are among the most common complaints, and many patients meet diagnostic criteria for conditions such as dysautonomia and myalgic encephalomyelitis. Researchers at the World Health Organization estimate that roughly one in ten people infected with the virus go on to experience symptoms serious enough to interfere with daily life, a figure that has translated into millions of cases worldwide and shaped a growing international research agenda.
Australia has its own substantial cohort of long-haul patients, with surveys run through the Australian Bureau of Statistics and several university hospitals suggesting that several hundred thousand adults are dealing with disabling after-effects. Post-COVID clinics in Melbourne, Sydney and Brisbane have been running at capacity for months, and patient advocacy groups in suburbs such as Newtown and Fitzroy have called for sustained federal funding. The new Manhattan centre is being watched closely by clinicians at the Royal Australian College of Physicians, who see it as a potential blueprint for the kind of integrated, multi-specialty care that local services have struggled to deliver.
The clinic occupies two floors of a converted midtown medical building and is expected to handle upwards of 4,000 patient visits in its first year. Referred individuals begin with a 90-minute intake covering cardiopulmonary exercise testing, cognitive screening, autonomic function assessment and a detailed symptom diary review. A coordinating nurse then builds a care plan that may draw in rheumatology, sleep medicine, occupational therapy and mental health, depending on the dominant complaints. The model mirrors the comprehensive approach championed by the Bateman Horne Center in Utah and similar academic programmes that have argued for treating long COVID as a multi-system condition rather than a single disease.
Funding comes from a mix of state health grants, private philanthropy and federal research dollars earmarked for post-pandemic recovery. Patients insured through Medicare-equivalent programmes are largely covered for the initial intake, though follow-up visits with certain specialists may carry co-pays. The centre has struck partnerships with three New York-area universities to embed research clinics alongside clinical care, allowing blood, saliva and imaging data to be collected in a standardised way. The medical director has framed the goal as treating individuals while building a longitudinal dataset to inform future therapeutic trials.
Access is uneven across the city. New York's public hospital system, NYC Health + Hospitals, runs its own post-COVID recovery programmes in the outer boroughs, but wait lists have stretched past six months in some neighbourhoods. The new clinic sits near Grand Central, favouring commuters from Westchester and Long Island over residents of the South Bronx or eastern Queens. Community health workers have flagged the risk of a two-tiered system, where privately insured patients access multidisciplinary care while uninsured or underinsured New Yorkers rely on a thinner safety net.
The clinic's intake form tracks more than 40 symptoms, ranging from well-documented cough and chest tightness to less obvious complaints such as loss of taste, tinnitus and temperature dysregulation. Treatment pathways are clustered into five overlapping tracks: cardiopulmonary, neurocognitive, autonomic, musculoskeletal and mental health. A patient whose primary issue is breathlessness may enter the cardiopulmonary track with weekly pulmonary function tests and a supervised exercise programme paced to avoid post-exertional crashes. Those dealing with cognitive slowing are routed into neurocognitive rehabilitation, a discipline Australian researchers at the University of Melbourne have helped pioneer.
Medication management is handled conservatively. Low-dose beta blockers are prescribed for some patients with inappropriate sinus tachycardia, while antihistamines and low-dose naltrexone are offered to a smaller subset under specialist supervision. More commonly, the prescription is for non-drug interventions: graded exercise, sleep hygiene coaching, dietary review and mental health support. Many clinicians describe their work as rebuilding trust in a body that no longer feels predictable, a sentiment echoed in patient forums from Perth to Pittsburgh.
For the small minority of patients whose symptoms suggest an autoimmune trigger, the clinic has begun trialling short courses of intravenous immunoglobulin on a case-by-case basis, with results fed into a national registry. Pharmacists embedded in the team review every prescription for potential interactions, especially in older patients managing diabetes, hypertension or kidney disease. The clinic also runs monthly webinars for primary care doctors, partly because many New Yorkers still rely on their local GP for the bulk of their care.
| Service | Location | Lead Specialist | Referral Pathway | Wait Time |
|---|---|---|---|---|
| Royal Melbourne Hospital Long COVID Clinic | Parkville, VIC | Respiratory physician | GP referral via hospital intake | 3-4 months |
| St Vincent's Post-COVID Clinic | Darlinghurst, NSW | Infectious diseases | GP or specialist referral | 2-3 months |
| Royal Brisbane and Women's Post-COVID Service | Herston, QLD | Multidisciplinary team | GP referral with positive PCR or serology | 4-5 months |
| Austin Health Post-COVID Clinic | Heidelberg, VIC | Neurology lead | GP referral, prioritised by severity | 3 months |
| Liverpool Hospital Post-COVID Clinic | Liverpool, NSW | Cardiology lead | GP referral, triage by nurse | 2 months |
A study published earlier this year in a major international journal followed more than 8,000 adults across three continents and found that neurocognitive symptoms, including brain fog and word-finding difficulty, were the most likely to persist beyond twelve months. Recent reviews of long COVID's worldwide toll have helped shape the Manhattan clinic's research priorities, alongside cohort work in Geelong and Adelaide that follows Australian long-haul patients to see whether symptom trajectories differ between hemispheres.
Cardiac findings have proven striking. Roughly a quarter of clinic patients show some degree of exertional intolerance on cardiopulmonary exercise testing, even when their resting echocardiogram appears normal. Autonomic testing reveals postural orthostatic tachycardia syndrome in a notable subset, mirroring findings from Australian paediatric long COVID studies published through the Murdoch Children's Research Institute. These patterns suggest long COVID is a family of overlapping post-infectious syndromes that may respond to different therapies rather than one uniform illness.
The evidence base for many widely used treatments remains thin. A 2025 Cochrane review concluded that graded exercise therapy carries risks for patients with prominent post-exertional malaise and should be individually prescribed rather than blanket-recommended. The new clinic has taken that warning on board, training physiotherapists in pacing strategies before any aerobic work is introduced. Clinicians say they would rather move slowly than push patients into predictable crashes.
The opening of the clinic coincides with a shifting political landscape around pandemic-era public health measures. The recent federal mask mandate ruling for air travel has been welcomed by infectious disease physicians who argue that layered protections remain important for clinically vulnerable passengers. Critics have framed the decision as yet another sign that institutional pandemic fatigue has hardened into policy. Long COVID advocates fall on both sides of that debate, but most agree that any reduction in transmission has direct implications for the future incidence of post-viral illness.
Public health budgets in the United States remain under pressure, with several states having already wound down dedicated pandemic funding streams. New York's decision to back the Manhattan clinic reflects a bet that post-COVID care will remain a meaningful clinical burden for at least another decade. Australian policy makers face similar choices, with state-run long COVID clinics funded through to 2026 before a planned review. Patient groups have lobbied hard for those clinics to continue, arguing it is time the federal government gave the long COVID file a fair go.
Insurance reimbursement remains a thorny issue in both countries. In Australia, the Medicare Benefits Schedule covers certain long COVID consultations, but rebates for the longer multidisciplinary reviews are patchy and vary by state. In the United States, the new clinic accepts most major private plans and Medicare, but uninsured patients are placed on a sliding-scale fee schedule that still runs into hundreds of dollars for a full intake. Advocates argue that until reimbursement models catch up with the reality of multi-specialty care, access will remain uneven and inequitable.
Conversations with clinic patients reveal a common theme: the relief of being believed. Many describe years of being told their symptoms were anxiety, perimenopause or the effects of ageing before finally receiving a coherent diagnosis. A 42-year-old teacher from the Upper West Side recounted how she had been unable to read a novel for eighteen months. A retired firefighter from Staten Island described how post-exertional crashes left him unable to climb the stairs to his apartment for weeks.
Australian patients describe parallel experiences. A Melbourne-based nurse interviewed on ABC Radio Melbourne explained how she gave up her job at the Royal Children's after eighteen months of crushing fatigue and joint pain. A Brisbane physiotherapist told the Brisbane Times she had travelled across town to access a rheumatology review unavailable at her local public hospital. These accounts echo what clinicians at the Manhattan facility hear daily, reinforcing the case for sustained investment in post-viral care.
Daily management for many patients involves careful rationing of energy, often described using the spoon theory framework. Some find that compression garments and paced daily walks help stabilise symptoms. Others rely on cognitive aids, voice-to-text software and flexible workplace arrangements. Occupational therapists coach patients on these practical strategies, recognising that small adjustments often yield larger gains than any single medication.
The Manhattan clinic is expected to publish its first twelve-month outcomes report in late 2026, covering symptom trajectories, healthcare utilisation and return-to-work rates. Australian collaborators at the University of Sydney and Monash University are likely to contribute comparative data, building on the kind of cross-jurisdictional research that has shaped previous pandemic responses. If early signals hold, the integrated care model may inform how health systems in both countries design their next generation of post-infectious illness services.
For now, the clinic's leaders are focused on the basics: seeing patients, refining protocols and training the next cohort of clinicians. The work is unglamorous and often slow, paced to match the recovery arc of the people walking through its doors. That pace, clinicians say, is itself a form of medicine, restoring a sense of agency to patients whose lives have been quietly upended by a virus the world is still learning to live with.