
Venezuela using coronavirus as cover to crack down on dissent, report claims
A report from Human Rights Watch was featured among the site’s world news headlines.
Read MoreLive world news related to the coronavirus (COVID-19) pandemic, updated by the minute. Follow global developments, statistics, and selected cryptocurrency news.
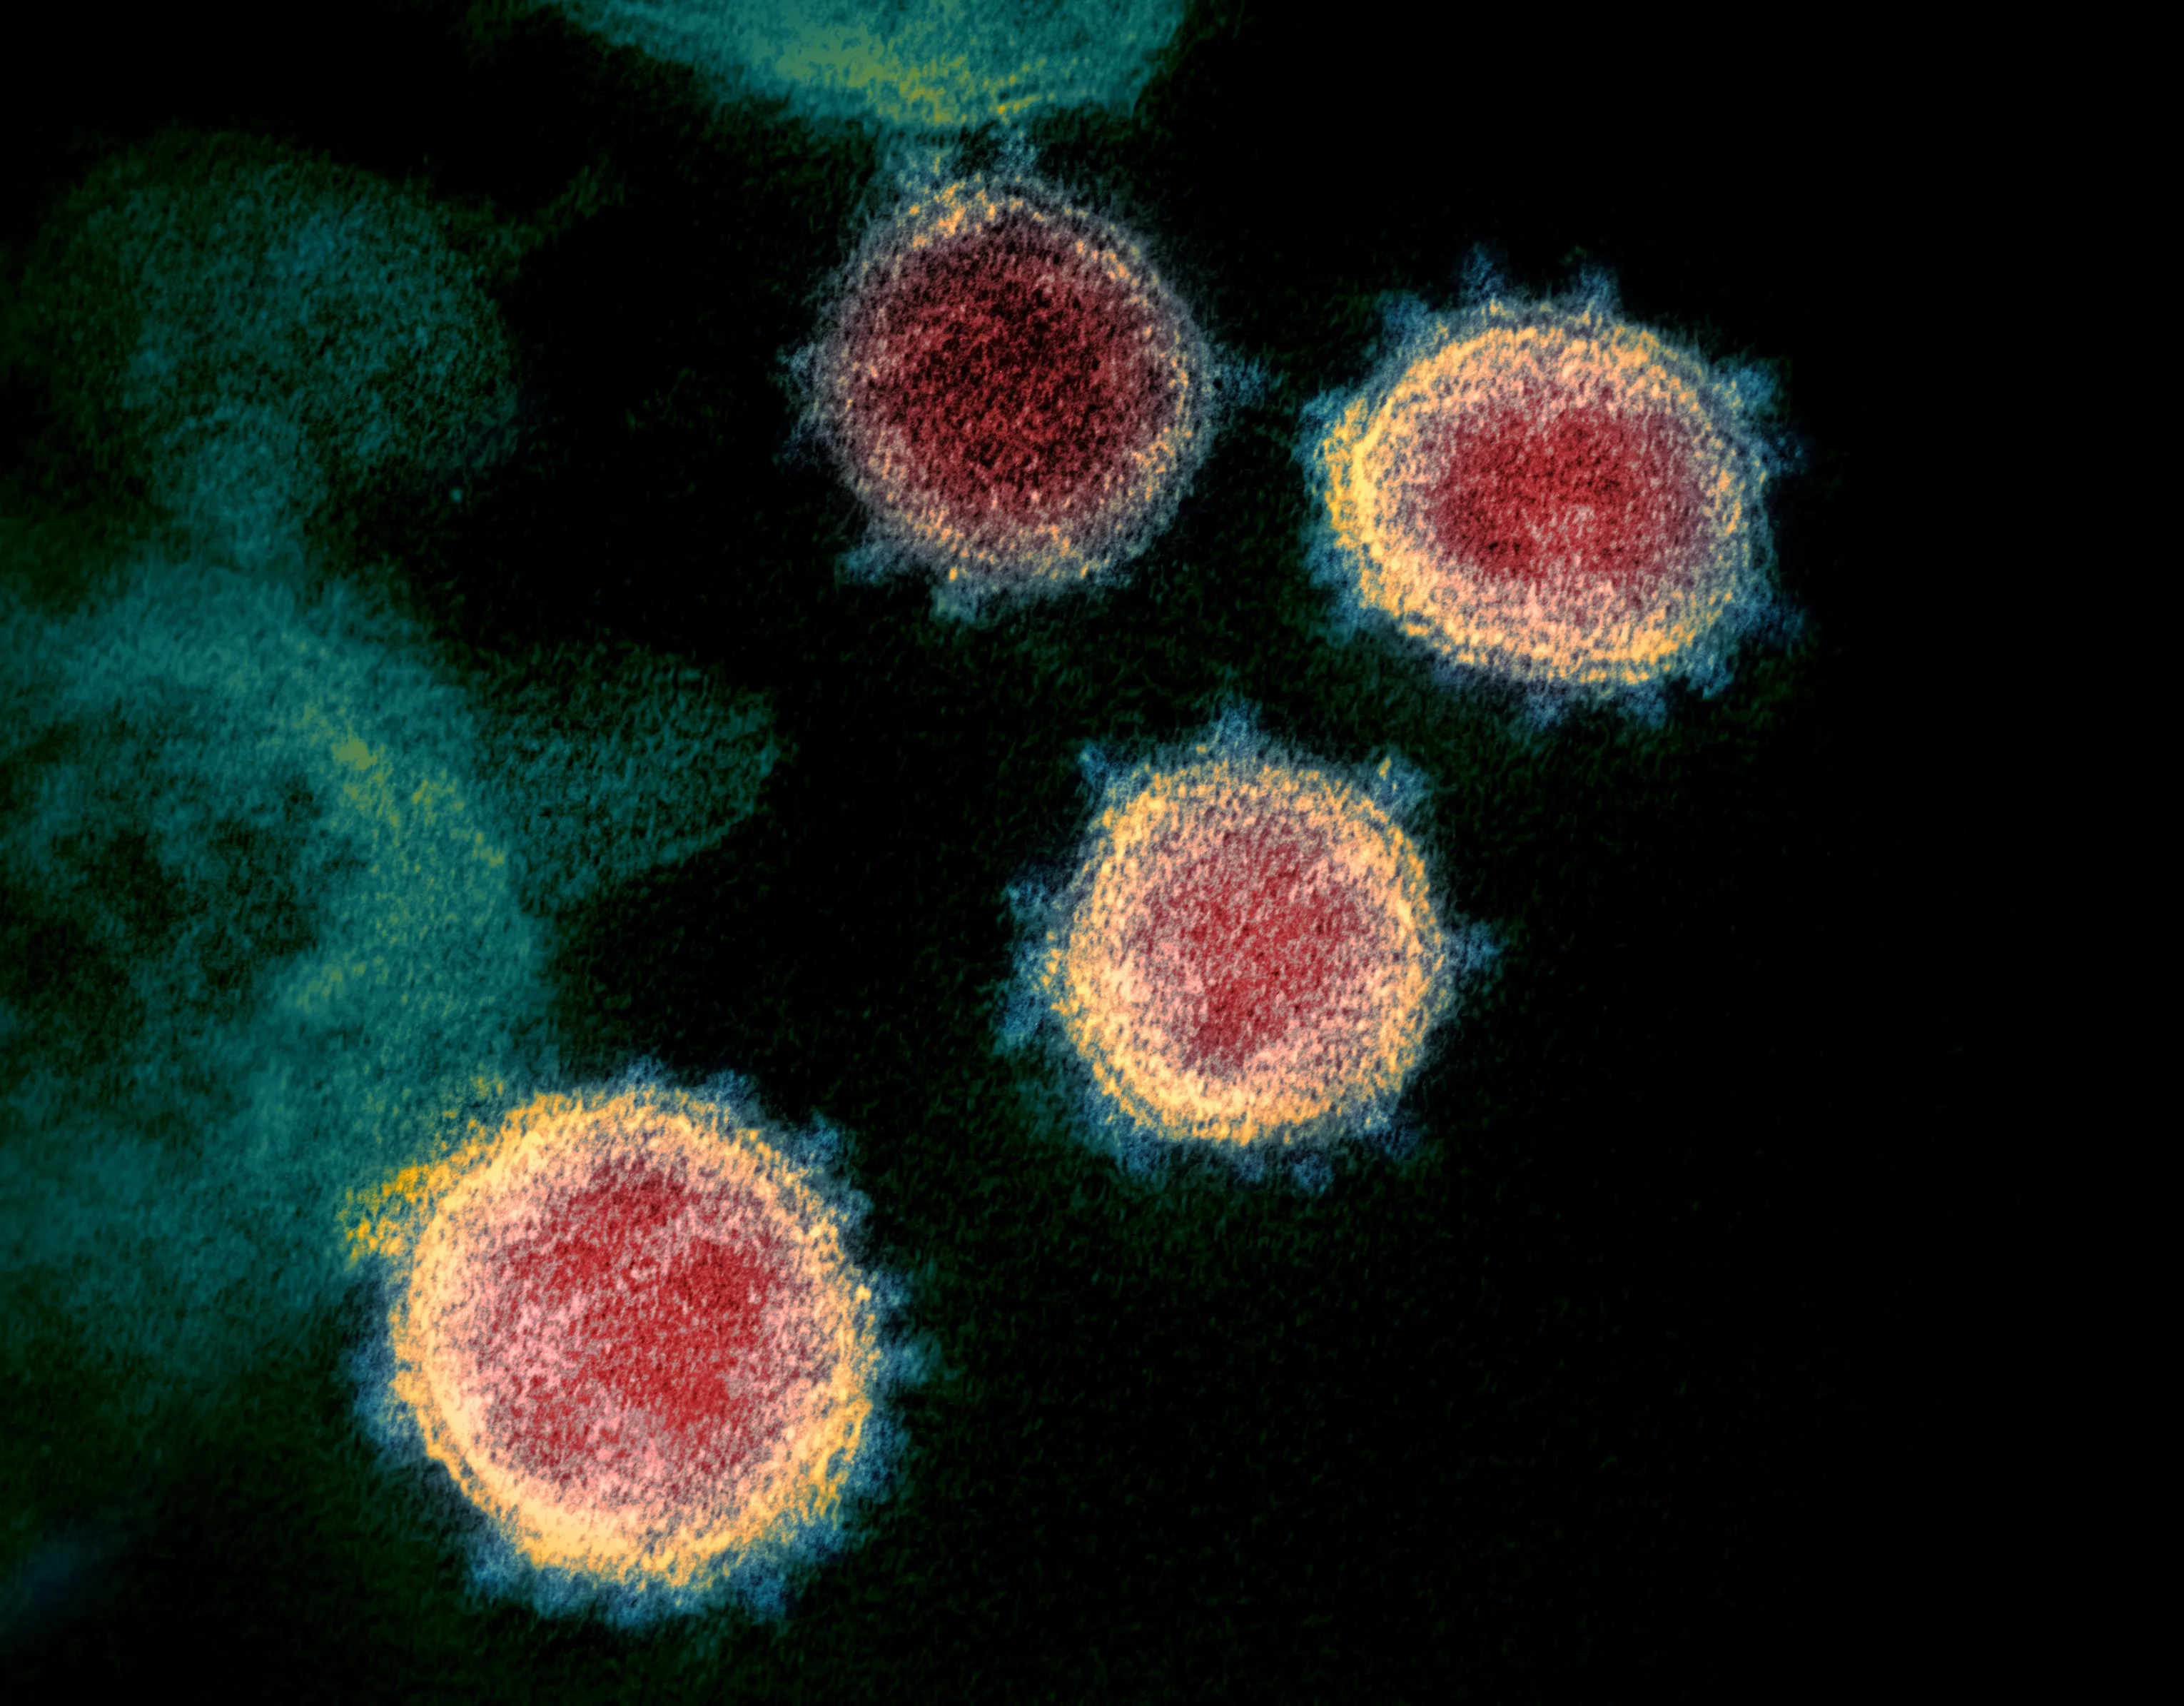

Read international coverage of the coronavirus pandemic and related global events.
Explore News
Visit the statistics section for data related to the coronavirus pandemic.
View Stats

Stay oriented with the site’s described live update format.
Read updates
A report from Human Rights Watch was featured among the site’s world news headlines.
Read More
The site featured this headline in its world news coverage.
Read More
The article covered the beginning of arguments by phone during the pandemic.
Read More
The site reported on the WHO chief’s self-quarantine after contact with a person who tested positive.
Read More
The site published an article discussing possible smartphone data sharing.
Read More
The site published an article on the initiative described in the headline.
Read More
The site discussed the subject of hoax martial law emails in a coronavirus article.
Read MoreChina reports first COVID-19 outbreak since reopening borders, marking a significant change in the country’s pandemic landscape after years of strict controls. The development comes after Beijing dismantled much of its zero-COVID system, ended mass testing in many areas and allowed international travellers to enter with far fewer restrictions.
The word “outbreak” can describe several different situations, from a cluster in one city to a broader wave of community transmission. The scale, variant involved, hospital pressure and death rate matter more than the label itself. Early reports can therefore shift as Chinese health authorities collect more samples and update surveillance data.
For Australians, the news is relevant because China remains a major trading partner, a leading destination for international travel and an important source of students, tourists and manufactured goods. Conditions in Chinese cities such as Beijing, Shanghai and Guangzhou can affect flights, supply chains, tourism and market sentiment well beyond mainland China.
| Issue | What the Chinese development may indicate | Relevance for Australia |
|---|---|---|
| Border policy | Virus circulation is being monitored in a more open travel environment | Flight demand and travel advice may change |
| Public health | A cluster could be local or part of a wider national wave | Australian hospitals and aged-care services watch international signals |
| Economic activity | Illness and isolation may reduce workplace attendance and consumption | Exporters, retailers and the ASX may respond to weaker Chinese demand |
| Data quality | Official figures may not immediately show the full picture | Comparisons with Australian surveillance require caution |
China’s reopening was a major departure from the controls that had shaped daily life for much of the pandemic. After the country abandoned its most restrictive measures in late 2022, international border rules were eased and quarantine requirements for incoming travellers were removed in January 2023. That transition allowed the virus to circulate more freely through a population with uneven levels of recent infection and immunity.
A first outbreak after reopening does not necessarily mean that COVID-19 has returned to a situation resembling the early years of the pandemic. Many people may now have some protection from vaccination or previous infection, while doctors have greater experience treating severe disease. At the same time, immunity can weaken, new variants can emerge and older people or those with chronic illness remain at higher risk.
The wording also requires careful attention. A “first outbreak” may refer to the first officially detected cluster after borders reopened, the first confirmed outbreak linked to a particular variant or the first episode to attract national attention. Chinese reporting can differ between central agencies, provincial authorities and state media, making location, case numbers and timing important details to verify.
Borders do not create a virus wave by themselves. They increase the movement of people, which gives an existing pathogen more opportunities to reach communities with different levels of immunity. A traveller can also carry an infection without symptoms, so temperature screening or a single negative test will never identify every case.
China’s large population and highly connected urban centres make local transmission difficult to assess from a small number of headlines. An outbreak in a transport hub may spread quickly between provinces, while a cluster in a workplace, school or hospital may remain relatively contained. The public health response depends on testing capacity, contact tracing, hospital admissions and the ability of officials to share information promptly.
The timing of an outbreak also matters. COVID-19 waves in the Northern Hemisphere have often overlapped with seasonal influenza and other respiratory infections. In Australia, winter increases pressure on emergency departments and general practices, particularly in Sydney, Melbourne and other densely populated cities. Chinese hospitals face a different seasonal calendar, yet the same problem applies when several respiratory viruses circulate together.
Case totals are less useful when testing is limited or when many people manage mild symptoms at home. Hospital admissions, intensive-care occupancy and excess deaths usually provide stronger indicators of severity, although these measures are reported more slowly. Wastewater surveillance, genomic sequencing and sentinel clinics can help identify changes before official case figures become clear.
The variant profile is another central question. A familiar Omicron subvariant may produce a rise in infections without causing a comparable increase in severe disease. A materially different strain would attract greater international attention, particularly if it showed evidence of escaping existing immunity or causing more serious illness. That assessment requires laboratory work rather than speculation based on social media posts.
Public health authorities increasingly use digital systems to follow transmission, but data collection raises questions about consent and privacy. During the earlier pandemic, proposals involving technology companies and location information prompted debate over how information could be used; reporting on how smartphone data could be shared illustrates the tension between rapid outbreak response and individual rights.
China’s central government has previously faced criticism over delays, changing definitions and limited access to some health information. A reliable assessment therefore needs more than a single daily bulletin. Independent researchers compare official releases with hospital activity, airline movements, laboratory findings and reports from local medical professionals, while recognising that each source has limitations.
Australia is unlikely to mirror China’s outbreak pattern exactly. The two countries have different vaccination histories, public health systems, population age profiles and levels of prior exposure. Australia also has a more decentralised health structure: the Commonwealth manages many national policies, while states and territories oversee hospitals and public health responses.
Travel is the most visible connection. Chinese students, tourists and business travellers are important to universities, hotels, restaurants and retailers in Australia. Airports in Sydney, Melbourne, Brisbane and Perth can see changes in passenger numbers when health advice or public concern affects bookings. Airlines may also adjust services if demand falls or if travellers face new entry rules.
Western Australia provides a useful local reminder of how quickly border policy can affect daily life. During the pandemic, Perth and other parts of the state maintained some of Australia’s strictest travel controls, while residents elsewhere dealt with changing domestic restrictions. That experience means Australian audiences tend to pay close attention to quarantine announcements, airline requirements and the practical difference between a health advisory and a binding rule.
Trade is another channel. China is a major buyer of Australian iron ore, coal, agricultural products and education services. If illness reduces construction, factory output or household spending, Chinese demand could weaken and affect the Australian dollar, commodity prices and companies listed on the ASX. The effect would depend on the outbreak’s duration and whether factories, ports and transport networks continued operating normally.
The end of zero-COVID did not remove the need for surveillance; it changed the purpose of surveillance. Under strict controls, officials focused on finding infections quickly and preventing almost all community spread. In an open system, the priority is more likely to be identifying severe disease, protecting hospitals and reducing harm among vulnerable groups while keeping schools, workplaces and travel operating.
That shift can be difficult for the public to interpret. A rise in reported cases may reflect more testing rather than a sudden deterioration. Conversely, a low official number can conceal substantial transmission if people no longer test or report mild infections. Clear communication about what is being measured is essential, especially when the public has grown tired of changing warnings.
Australians have seen similar communication challenges. During flu season, a crowded GP clinic or a shortage of rapid antigen tests can reveal pressure before national statistics catch up. People in Melbourne may follow state health updates, while a resident in regional Queensland may rely more heavily on local hospital advice and pharmacy availability. These differences make broad claims about national risk less useful than practical, specific guidance.
Vaccination remains relevant, especially for older adults and people with medical conditions. Protection against infection can decline, but vaccination generally remains part of the strategy for reducing severe outcomes. Mask use in crowded indoor settings, staying home when unwell, improving ventilation and seeking medical advice early can still reduce transmission without recreating blanket lockdowns.
The next reliable signals will involve the outbreak’s geographical spread, the number of patients requiring hospital care, the age and health profile of severe cases, and any evidence of a new variant. Reports of crowded clinics or cancelled events may indicate disruption, but they do not by themselves establish the national scale of transmission.
Readers should also distinguish between an imported case, a local cluster and sustained community transmission. An infection detected at an airport is different from a chain of cases across multiple cities. Likewise, a temporary travel precaution does not necessarily mean that a country is facing an emergency comparable to the first global waves.
For Australian travellers, checking Smartraveller, airline notices and advice from state or territory health authorities is more dependable than relying on viral posts. Travellers should also consider access to medicines, travel insurance conditions and the rules that apply when returning to Australia. Requirements can change faster than printed itineraries, particularly during periods of uncertainty.
The broader lesson is that reopening restores movement but does not end the pandemic’s ability to produce new waves. China’s experience will be watched by governments, hospitals, businesses and communities across the region. The most meaningful measure will be whether public health systems can detect transmission early, protect high-risk people and keep essential services functioning as borders remain open.